
Bulbous & Boxy Tip Correction in Mumbai: A Refined, Natural Nasal Tip That Still Belongs to Your Face

Indian Board Certified Plastic Surgeon
M.CH, MS, ISAPS Mentor
16000+ Cosmetic Surgeries
1500+ Rhinoplasty Surgeries
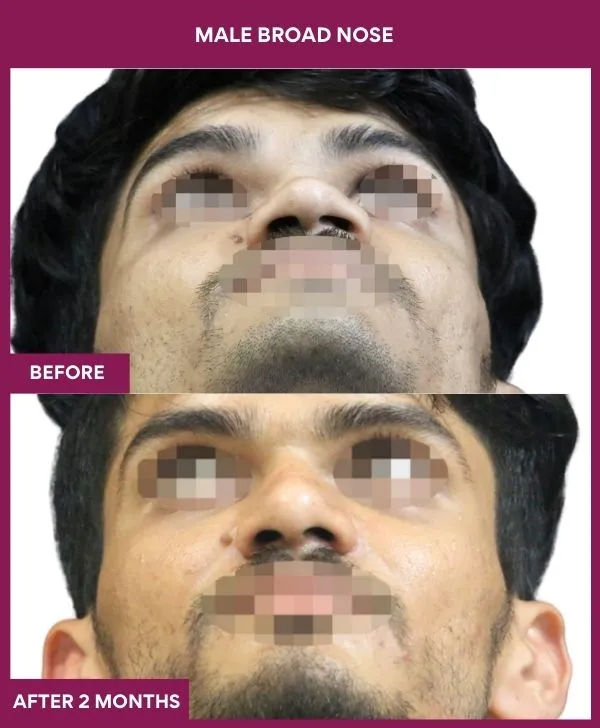
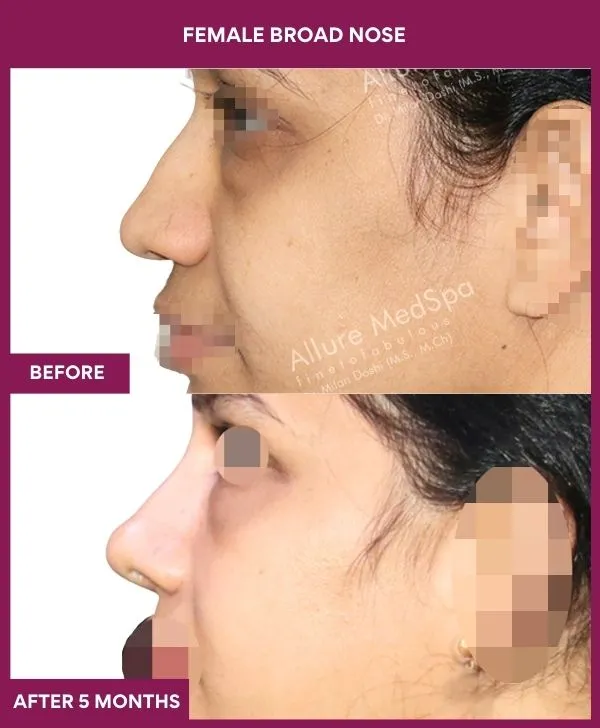
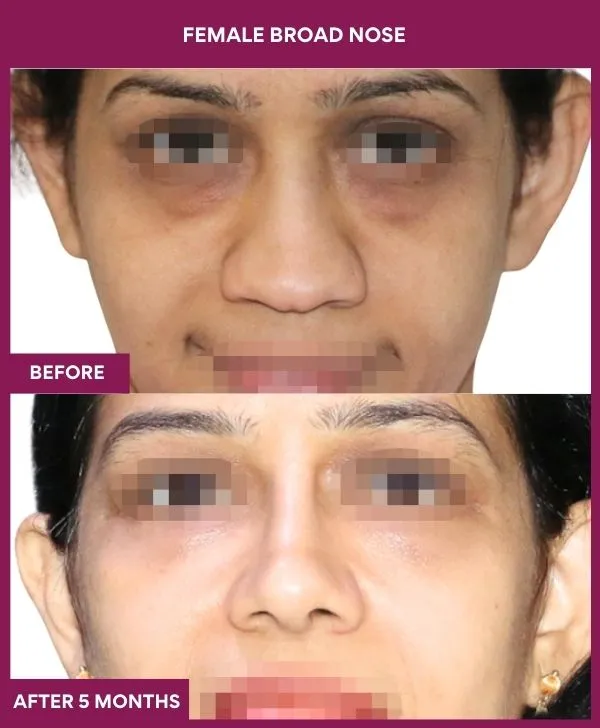
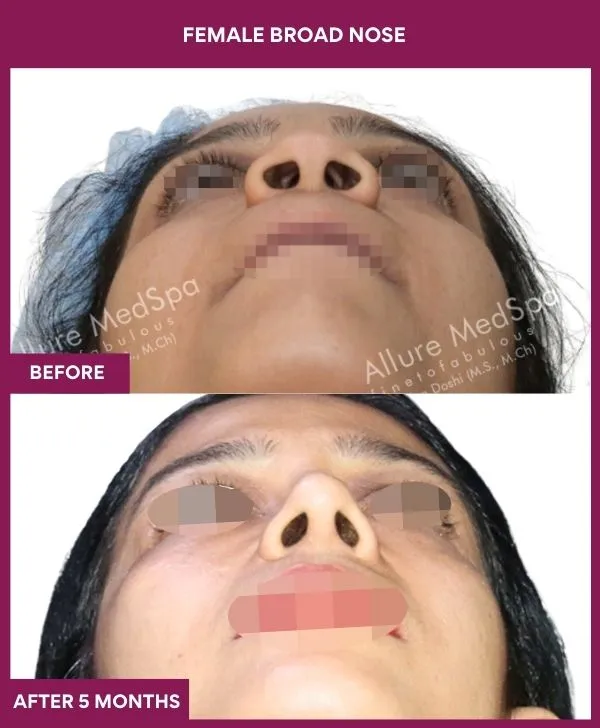
Bulbous and boxy tip correction refines a nasal tip that looks round, heavy, square or undefined by reshaping and supporting the tip cartilages — with sutures and grafts first, cutting last. At Allure Medspa Mumbai, Dr. Milan Doshi plans each tip around skin thickness and support rather than a “sharp nose” template, so the tip looks cleaner and more elegant, still recognisably yours, never pinched.
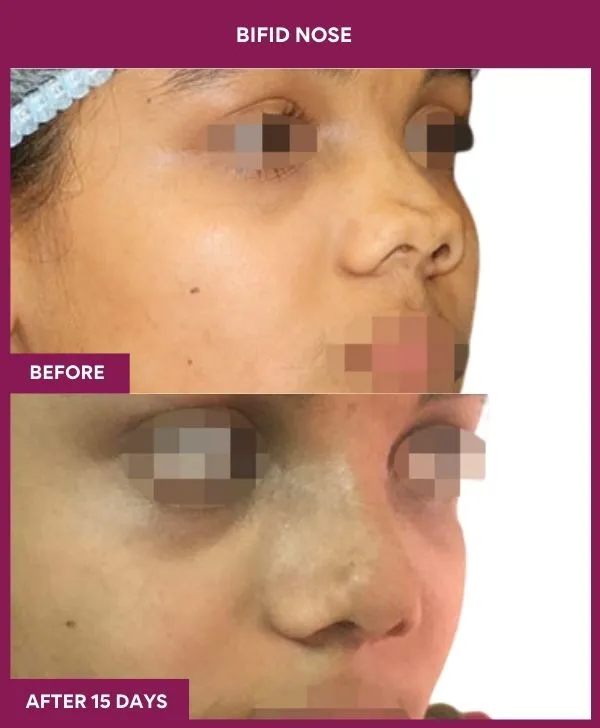
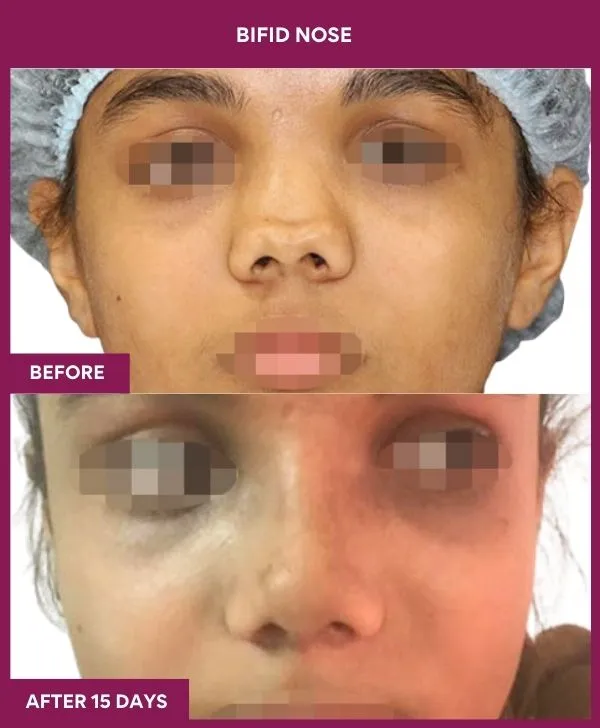
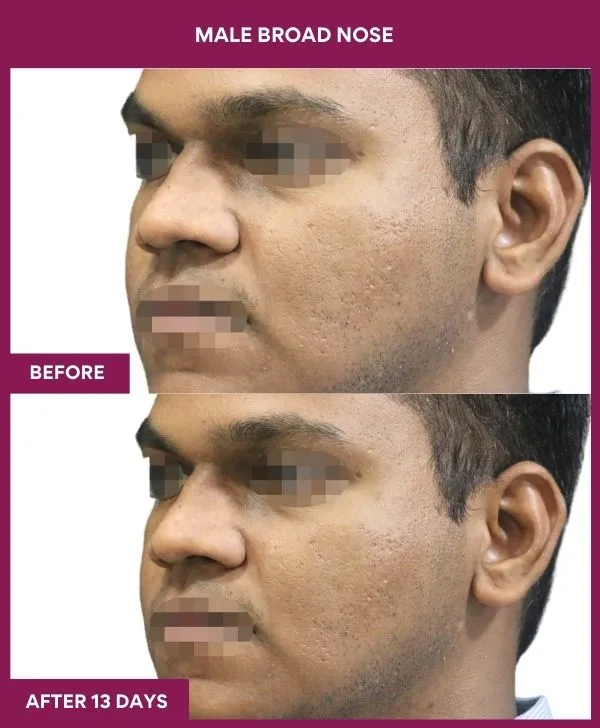
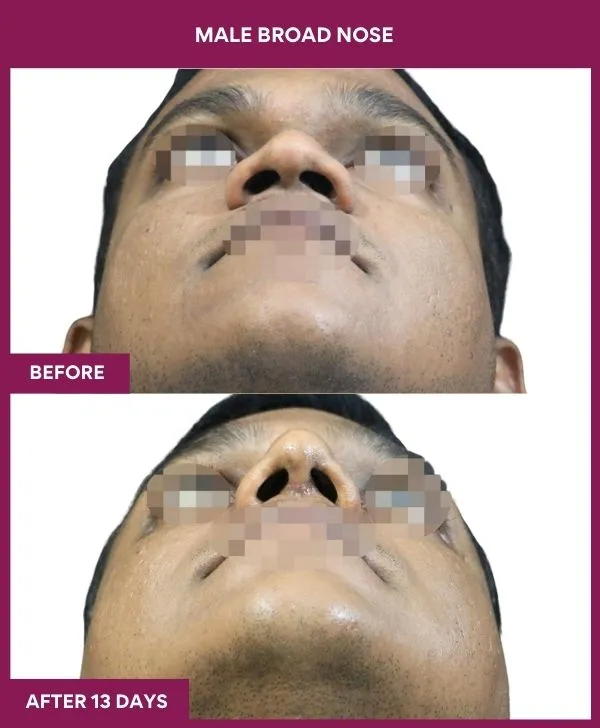
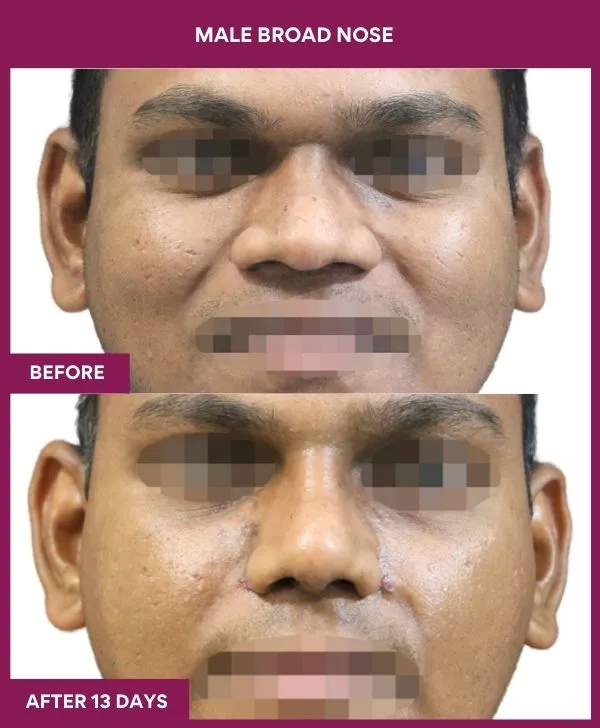
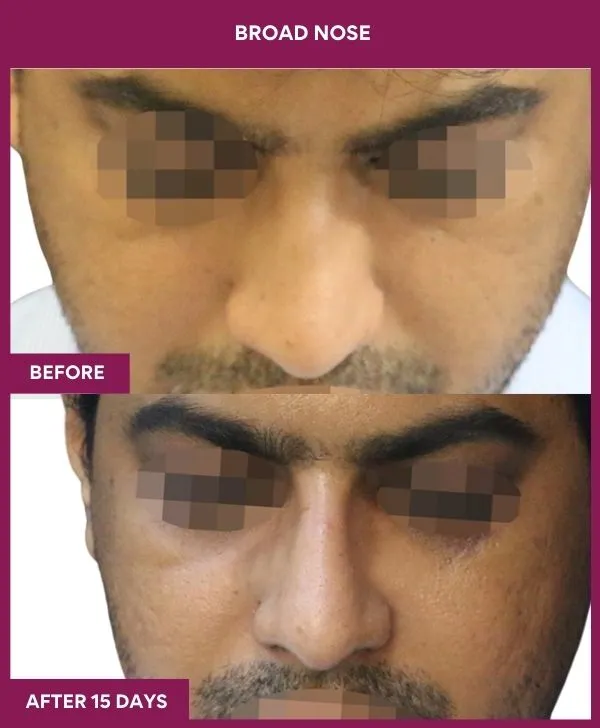
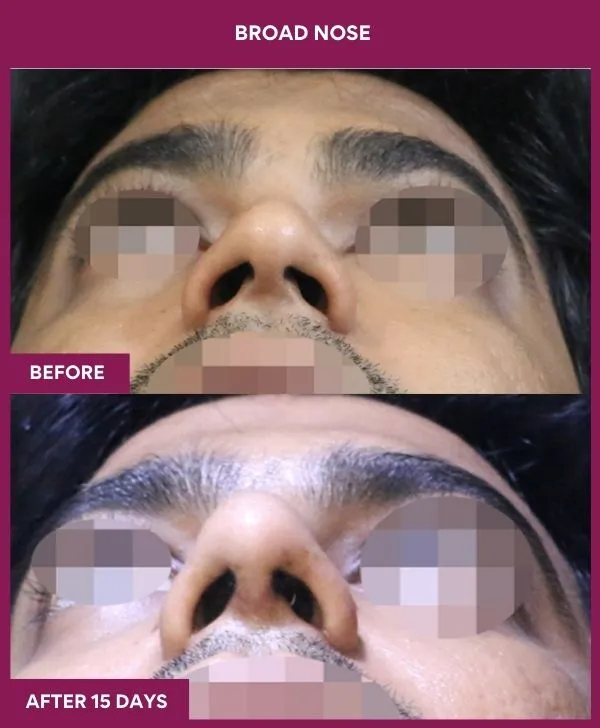
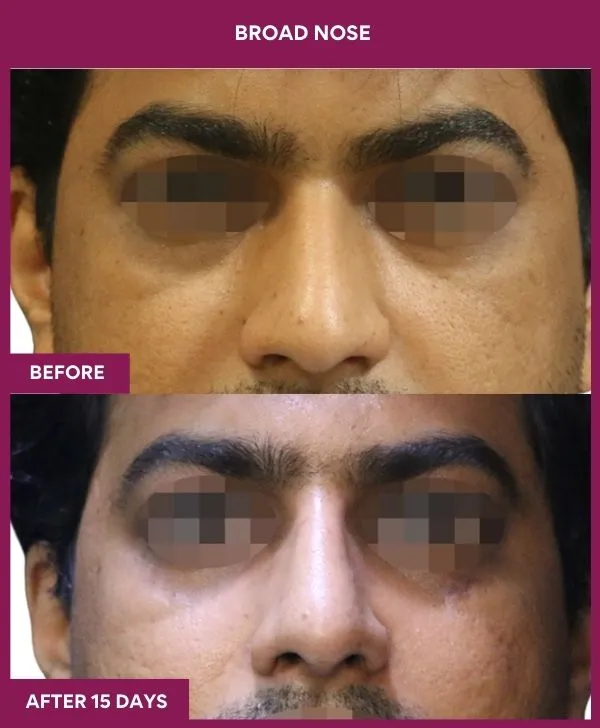
Bulbous & Boxy Tip Correction Before And After Images
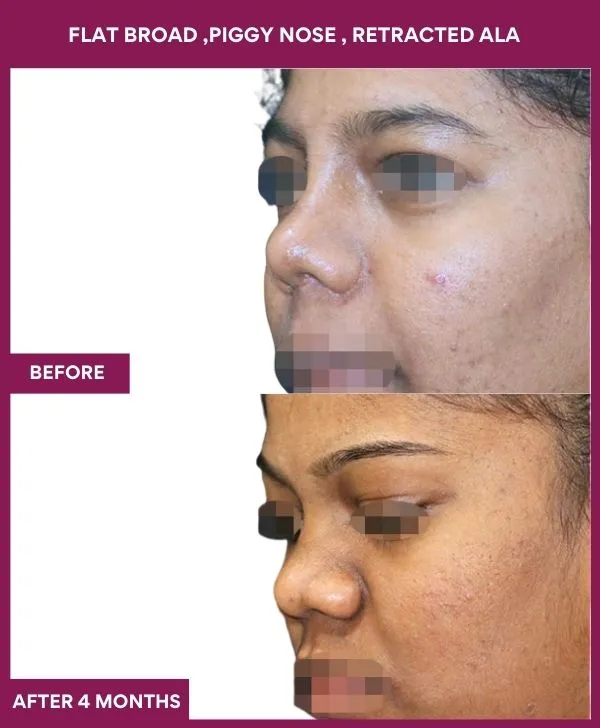
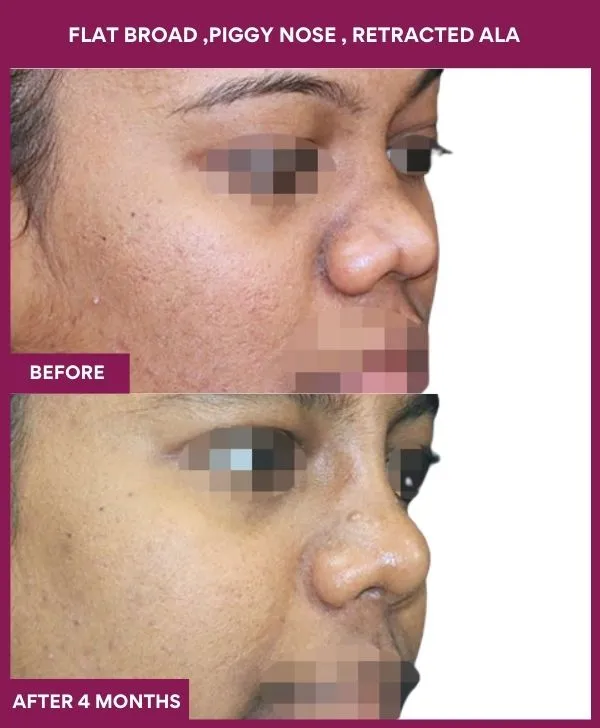
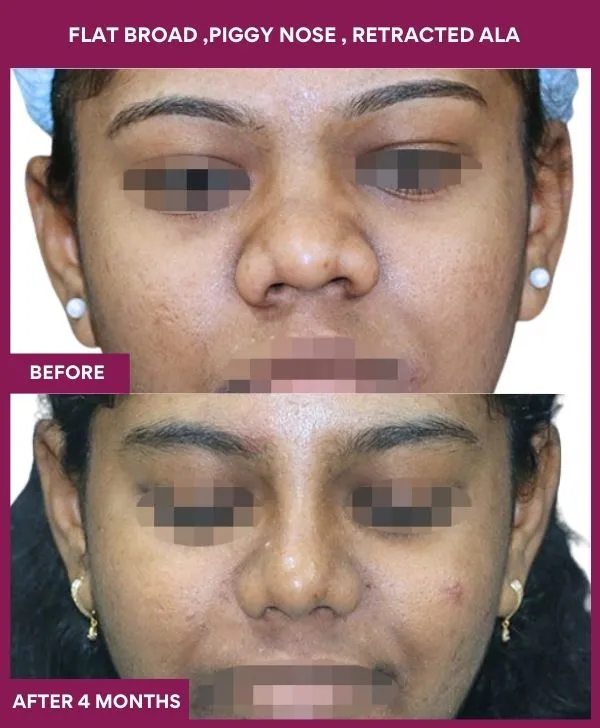
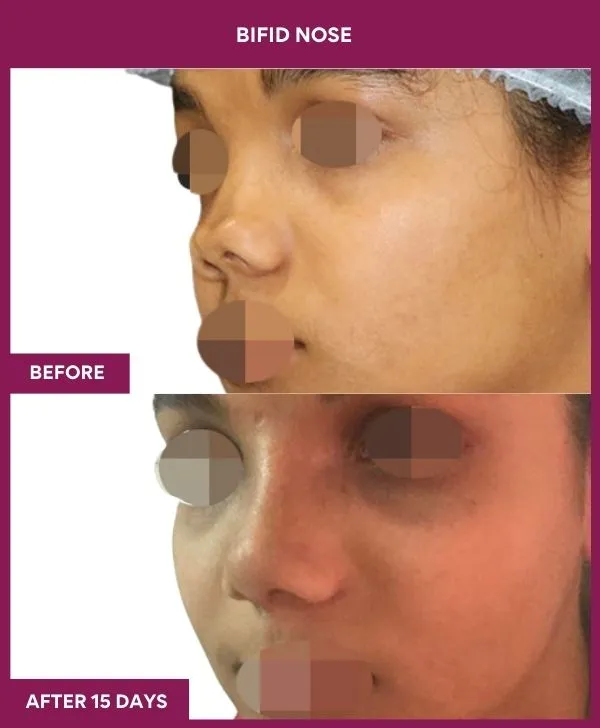
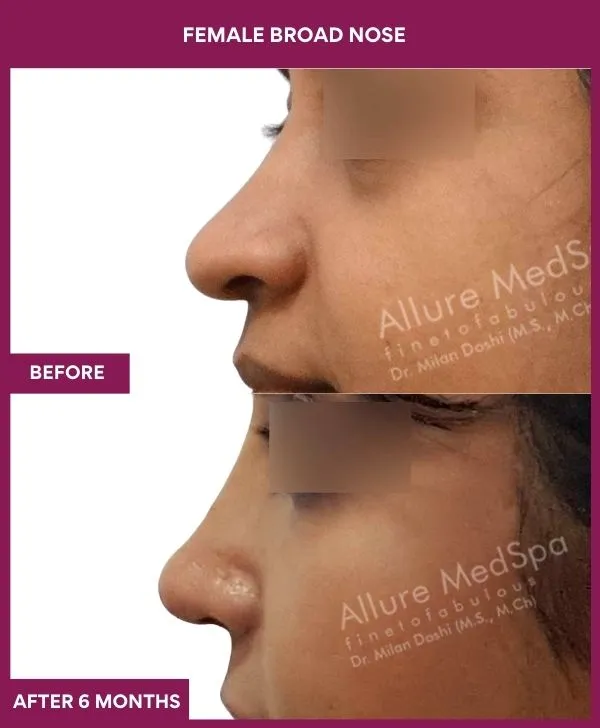

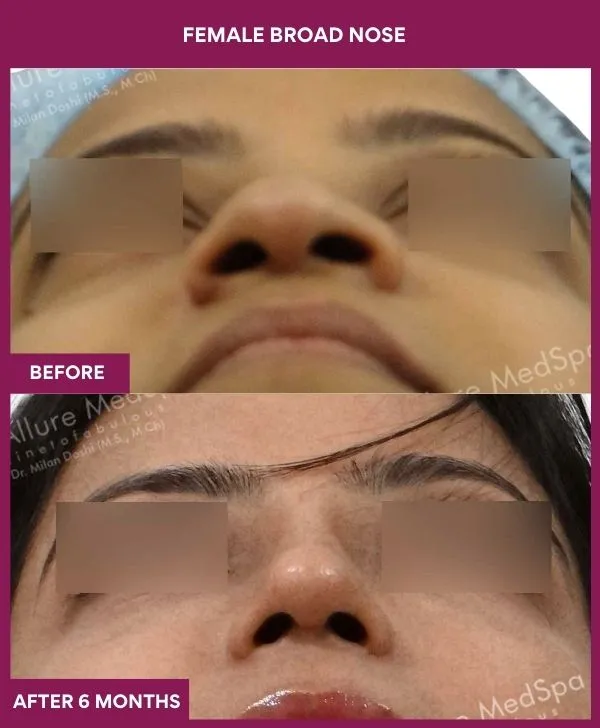
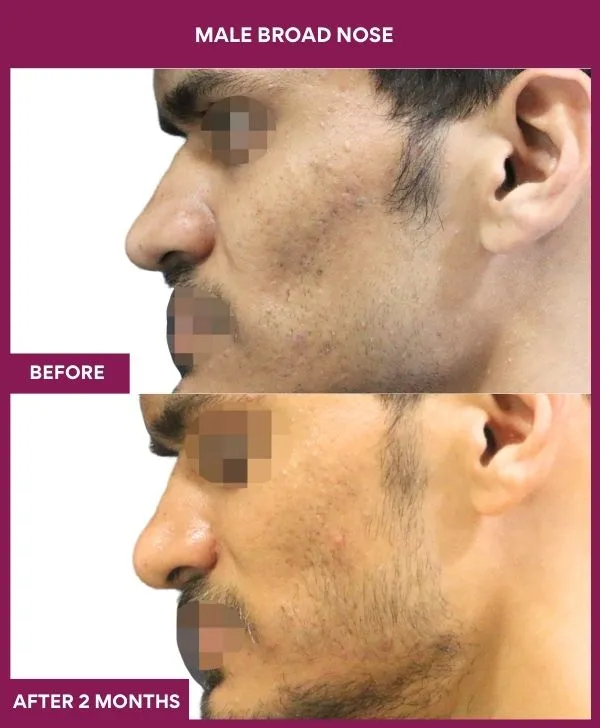
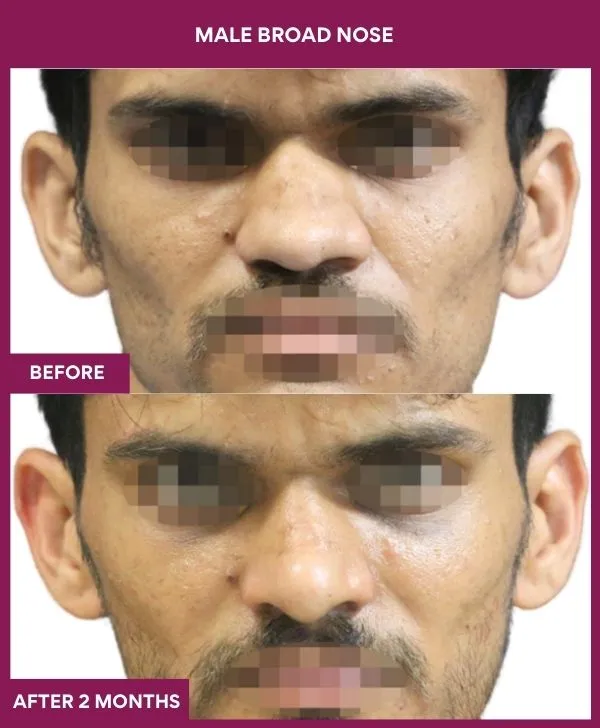
Rhinoplasty Surgery Testimonials: Celebrities Patient

Awarded by Google.com
Rating: 4.7
Reviews: 485+

Awarded by WhatClinic.com
Rating: 4.8
Reviews: 119+

Awarded by Realself
Rating: 4.9
Reviews:453+

Awarded by Facebook
Rating: 4.6
Reviews:105+
Dr Milan Doshi and his staff are very professional and committed as the centre is highly equipped with advanced technology. I had closed rhinoplasty 4 months back and I’m seeing the results as to how it becomes successful.
Deepika Shetty
The doctor explained everything clearly and the surgery was smooth. Recovery was faster than I expected and the team was very supportive.
Rahul Mehta
Very natural results and excellent staff. From consultation to follow-up, the experience was outstanding and boosted my confidence.
Sneha Kapoor
Video: Best Rhinoplasty Surgeon explain nose reshape procedure
Dr Milan Doshi is describing the Rhinoplasty Surgery in detail with benefits, techniques, recovery, result, risk and complecations
Am I a Candidate?
(4 quick questions)
Quick Facts About Bulbous & Boxy Tip Correction
TIME REQUIRED
2–4 hours
ANESTHESIA
General
HOSPITAL STAY
Day-care or 1 night
PAIN LEVEL
Mild–moderate
BACK TO WORK
7–10 days
RESULTS LAST
Permanent
SUCCESS RATE
97–98%
COMPLICATIONS
Under 2-3%
How Much Does Bulbous & Boxy Tip Correction Cost in Mumbai?
Bulbous and boxy tip correction in Mumbai starts from ₹70,000 to ₹1,80,000 and varies with cartilage shape, skin thickness, whether the tip can be refined closed or needs an open approach, whether grafts are required and from where, anaesthesia, and whether the tip is being done alone or as part of full rhinoplasty. Revision cases are quoted separately after examination. A final quotation follows examination and a written surgical plan — it cannot be given accurately by phone or from photographs.
| Tip correction scope | Indicative price range |
|---|---|
| Closed tip refinement — suture techniques only (dome sutures, conservative trim) | ₹70,000 – ₹1,00,000 |
| Open tip refinement — sutures + cephalic trim | ₹90,000 – ₹1,30,000 |
| Open tip refinement with tip / shield / strut grafts (septal cartilage) | ₹1,10,000 – ₹1,50,000 |
| Thick-skin tip correction with structural support + soft-tissue management | ₹1,20,000 – ₹1,70,000 |
| Boxy tip with alar base (wide nostril) correction | ₹1,20,000 – ₹1,80,000 |
| Tip correction with ear (conchal) cartilage graft | ₹1,30,000 – ₹1,80,000 |
| Tip correction as part of full rhinoplasty / septorhinoplasty | Included in rhinoplasty plan — see rhinoplasty cost guide (₹1,00,000–₹3,50,000) |
| Revision tip correction | Quoted after examination |
Get your exact quote & surgery plan
Share your details — our team responds within working hours with cost, EMI options and next steps.
Most Common Question People Ask
Q1. Are bulbous and boxy tips the same?
Ans. No. A bulbous tip usually looks round, full and under-defined, while a boxy tip looks square, broad or angular. Both affect the nasal tip, but the underlying cartilage shape, dome spacing, skin thickness and correction plan may differ.
Q2. How much does bulbous tip correction cost in Mumbai?
Ans. The guide range is ₹70,000–₹1,80,000 plus 5% GST. Final cost is confirmed only after consultation. Revision, grafting or full rhinoplasty may change the estimate.
Q3. Will bulbous tip correction make my tip very sharp?
Ans. The goal is natural definition, not an over-sharp or artificial tip. In many Indian and South-Asian noses, a balanced refined tip looks better than extreme sharpness. Over-narrowing can weaken support and affect breathing.
Q4. Can thick skin be corrected in bulbous tip surgery?
Ans. Thick skin can be managed surgically, but it limits how sharply the final tip can show refinement. Surgery can improve cartilage support and definition, but the skin envelope settles slowly and may not reveal a razor-sharp contour.
Q5. Is this always full rhinoplasty?
Ans. No. Bulbous or boxy tip correction may be done as focused tip surgery in selected patients. If the bridge, nasal bones, septum or nostril base also need correction, full rhinoplasty, septorhinoplasty or another procedure may be recommended.
Q6. How long does swelling last after tip correction?
Ans. Tip swelling lasts longer than bridge swelling. Most patients see gradual improvement over weeks to months, but thick skin or open surgery can delay visible definition — often 12 months, sometimes 18 in very thick skin. Early swelling should not be judged as the final result.
Q7. Will it look natural?
Ans. A natural result depends on reshaping and supporting the cartilage rather than cutting it away, respecting your skin thickness, and sizing the tip to your face. The aim is your nose with better definition, not someone else’s nose on your face. Results vary between individuals and cannot be guaranteed.

Why Choose Dr. Milan Doshi?
Dr. Milan Doshi, MCh, MS — Indian board-certified plastic surgeon with 27+ years in aesthetic surgery and 1,500+ rhinoplasties, with a structure-first approach to the nasal tip developed on thick-skinned Indian noses. ISAPS mentor, trusted by patients from 70+ countries. Consults at Andheri West; surgeries at the NABH-accredited surgical centre, Goregaon West.
🩺 Dr Doshi Note: “For bulbous or boxy tip correction, patients should not look only for a ‘sharp nose.’ They should look for a surgeon who understands natural refinement. In Indian noses, thick skin, cartilage width, tip support, and facial balance must be judged carefully. My aim is to create a tip that looks more defined and elegant, but still belongs to your face. The best rhinoplasty result is when everyone notices improvement, but no one knows exactly what was done. ‘Everyone notices, no one knows’ — that’s the aim.”
The Complete Guide About Bulbous & Boxy Tip Correction
What Is Bulbous & Boxy Tip Correction?
Bulbous and boxy tip correction is a form of tip rhinoplasty that refines the lower third of the nose. Bulbous tip and boxy tip are lower-nose shape concerns, not whole-nose diagnoses. A bulbous tip usually looks round, full and under-defined, while a boxy tip looks broader, squarer or more angular because of lower lateral cartilage shape, skin thickness and tip-support anatomy.
A bulbous or boxy nasal tip can make the nose look heavier than the rest of the face. Some patients describe it as “too round,” “not defined,” “wide at the end,” or “not elegant in photos.” The key is to identify the true cause before planning correction.
This distinction matters. Bulbous and boxy tips can overlap. A patient may have thick skin plus broad lower lateral cartilages, or a square cartilage framework hidden under a soft-tissue envelope. Treatment should be planned according to the patient’s skin, cartilage, support, nostril shape and facial balance — not copied from a standard “sharp nose” template.
Bulbous vs boxy tip
| Feature | Bulbous tip | Boxy tip |
|---|---|---|
| Main appearance | Round, full, soft, under-defined | Square, broad, angular |
| Main area | Lower third of nose | Lower third of nose |
| Common cause | Broad lower lateral cartilages, thick skin, soft-tissue fullness | Wide domal / interdomal configuration, widened cartilage geometry |
| Light reflection | Diffuse, rounded highlight | Flatter, broader, more angular highlight |
| Skin role | Often important, especially in thick skin | Can blunt definition; cartilage geometry usually key |
| Treatment goal | Better definition without over-sharpening | Softer, narrower, more natural dome shape |
| Main caution | Avoid artificial sharpness | Avoid pinching or support loss |
Is tip correction cosmetic or reconstructive?
| Type | Main purpose | Common example |
|---|---|---|
| Cosmetic (aesthetic) | Improve definition and proportion of a healthy tip | Primary bulbous or boxy tip refinement |
| Functional / reconstructive | Restore tip support and the external nasal valve after injury or a previous over-resected tip | Revision with structural grafts for a pinched, collapsing tip |
Most tip corrections in private practice are cosmetic. Cosmetic tip rhinoplasty should not be assumed to be covered by health insurance; coverage, where it exists, applies only to documented functional indications and requires prior verification with your insurer.
Synonyms for bulbous & boxy tip correction
Patient terms: round nose tip surgery, bulbous nose surgery, boxy nose tip surgery, nose tip reduction, tip refinement, fat nose tip surgery, thick nose tip surgery
Medical terms: tip rhinoplasty, tip plasty, dome-binding (transdomal) sutures, interdomal sutures, cephalic trim, tip grafting, lower lateral cartilage reshaping, soft-tissue envelope debulking
Sources: NCBI – Nasal Tip Surgery (StatPearls) · PubMed 34936611
Does Your Nose Tip Look Heavier Than the Rest of Your Face?
Many people describe the same experience: the bridge is fine, the profile is fine, but in front-facing photographs the end of the nose looks like a soft ball — it catches the light as one round blob instead of two clean points, and no amount of contouring makes it look defined. That gap is real, and it is usually the tip cartilages and the skin over them, not the whole nose.
Three questions patients actually ask at consultation:
- “My skin is thick and oily — is there any point, or will the tip just look the same?”
- “Can you make it sharp like the noses I see online?”
- “Do I need a full nose job, or can you just fix the tip?”
These concerns do not automatically mean surgery is needed. A mildly soft tip on a face with balanced features may be best left alone. Thick skin does not rule out surgery but changes what is achievable. A tip that is round because the whole nose is wide needs a broader plan. The useful question is not “how sharp can it get?” but “what is making it look round — cartilage, skin or support — and what will the skin allow?”
Global and Indian trends
Tip refinement is the single most requested element of rhinoplasty worldwide, and in India the bulbous, thick-skinned tip is the most common tip presentation seen in consultation. The approach in ethnic rhinoplasty has moved decisively from cartilage removal towards suture reshaping and structural support — the method Allure Medspa uses — because it preserves breathing and avoids the pinched look that follows aggressive trimming in thick skin.
What Are the Benefits of Bulbous & Boxy Tip Correction?
The main benefits of tip correction are a more defined tip with two clean tip-defining points instead of one round highlight, a narrower, softer dome shape in boxy tips, better balance between the tip and the bridge, and — because the method is support-first — a tip that breathes as well as or better than before. Because cartilage is reshaped and reinforced rather than removed, the result is stable and long-lasting.
Cosmetic benefits
- Defined tip-defining points — the domes are brought together and shaped so light reflects off two points, which is what the eye reads as “refined”.
- Narrower, softer dome in boxy tips — the square corners are rounded into a natural triangle without pinching.
- Better tip-to-bridge proportion — the lower third stops looking heavier than the upper two-thirds.
- Improved projection and rotation where needed — a tip that also droops or sits flat can be supported forward and slightly up.
- Cleaner supratip break — the subtle step between bridge and tip returns, which is a key marker of an elegant nose.
- Preserved identity — the aim is your tip, refined; everyone notices better definition, no one knows it was surgery.
Functional benefits
- Reinforcing the lower lateral cartilages strengthens the external nasal valve instead of weakening it.
- A columellar strut or septal extension graft gives a stable tip that does not droop with age or smiling.
- Nostril rims are kept supported, avoiding the retraction that follows over-resection.
Which Problems Can Bulbous & Boxy Tip Correction Correct?
| Concern | Relevance to this page | Possible approach | Learn more |
|---|---|---|---|
| Round, full, under-defined tip (bulbous) | Core target | Dome sutures, conservative trim, support grafts | This page |
| Square, broad, angular tip (boxy) | Core target | Interdomal + transdomal sutures, dome reshaping | This page |
| Thick-skin tip with soft-tissue fullness | Core target (with limits) | Structural support + conservative soft-tissue management | This page |
| Weak or unstable tip support | Core target | Columellar strut / septal extension graft | Nasal Tip Plasty |
| Bifid (split) tip | Addressed | Interdomal sutures ± tip graft | This page |
| Drooping tip | Addressed when combined | Tip rotation and support | Drooping Tip Correction |
| Whole nose wide | Different diagnosis | Broad nose correction | Broad Nose Correction |
| Wide nostrils / alar flare | Different diagnosis | Alar base reduction | Wide Nostril Correction |
| Hump or crooked bridge with a round tip | Combined when present | Full rhinoplasty | Rhinoplasty Surgery |
| Pinched or collapsed tip after earlier surgery | Revision case | Structural grafts (ear / rib cartilage) | Revision Rhinoplasty |
The anatomy of the nasal tip — the structures this surgery works on
Understanding a few terms makes consultation far easier.- Lower lateral cartilages (alar cartilages) — the pair of curved cartilages that form the tip. Their width, convexity and how far apart they sit decide whether the tip is round, square or defined.
- Domes — the highest bend of each lower lateral cartilage. Two domes close together and well-shaped create the two tip-defining points; wide, flat domes create a boxy tip.
- Interdomal distance — the gap between the two domes. Wide spacing is the signature of a boxy tip; a very wide gap with a groove between is a bifid tip.
- Tip support (tripod) — the tip rests on the two lateral crura and the medial crura together, like a tripod; weaken any leg and the tip drops or pinches.
- Supratip — the area just above the tip. Thick soft tissue here creates a rounded “polly-beak” and hides the tip break.
- External nasal valve — the nostril opening, held open by the lateral crura. Over-trimming these cartilages collapses it.
- Skin–soft-tissue envelope — thick, sebaceous tip skin with a fibrofatty layer beneath. It drapes softly over the framework and is the main limiter of definition in Indian noses.
What Are the Limitations of Bulbous & Boxy Tip Correction?
Tip correction cannot change skin thickness, cannot make a thick-skinned tip as crisp as a thin-skinned one, cannot narrow the bridge or nostrils, cannot guarantee symmetry, and cannot produce a specific other person’s nose. It reshapes and supports the cartilage beneath your skin. Being clear about these boundaries before surgery is one of the strongest predictors of satisfaction afterwards.
Skin is the ceiling. In thick skin, the soft-tissue envelope can hide fine cartilage refinement. Thick skin does not mean surgery cannot help, but it may limit sharpness, slow the visible shrink-wrap effect and delay final tip definition. This is important in many Indian and South-Asian noses, where the tip skin may be thicker and more sebaceous. The surgeon can refine the structure underneath, but the skin must settle over time and may not show the same crisp contour seen in thin-skinned noses. Removing more cartilage does not make the skin shrink better — it only weakens the support beneath.
A refined tip on a nose with a wide bridge or flared nostrils can look out of place, because the surrounding parts have not changed. Some patients need complementary planning — bone narrowing, alar base reduction or bridge augmentation — to get the balance they are picturing. Results vary by individual anatomy and healing.
Why “smaller” is not always better
- Pinching: tip may look squeezed or operated.
- Alar retraction: nostril rim may pull upward.
- Valve collapse: breathing may worsen.
- Asymmetry: weak cartilage can heal unevenly.
- Irregularity: edges may become visible, especially in thin skin.
- Revision risk: structural repair may be needed later.
- Unnatural result: the tip may not match the face.
Sources: PMC3901916 · PubMed 20442073 · NCBI – Rhinoplasty (StatPearls)
Why Consult Before Bulbous & Boxy Tip Correction?
A tip consultation is a diagnostic appointment, not a sales appointment. Its purpose is to work out what is making the tip look round or square — cartilage width, dome spacing, weak support, thick skin, or a mix — whether the rest of the nose needs to change with it, and how much definition your skin will actually show.
What happens during a tip consultation?
Assessment typically covers the tip from the front, three-quarter, basal and profile views; how light reflects off the tip (one blob or two points); palpation of the lower lateral cartilages for width, strength and spacing; a pinch test of tip skin thickness and sebaceous quality; tip support (does the tip spring back when pressed?); projection and rotation in relation to the bridge; nostril shape and rim position; the external nasal valve and breathing; the bridge and nostril base, to decide whether focused tip surgery is enough; documented asymmetry; full medical history including medicines, supplements, isotretinoin and nicotine use; previous nasal surgery or fillers; and your goals in your own words. You should leave understanding your diagnosis, whether focused tip surgery or full rhinoplasty is recommended, the alternatives including no treatment, the realistic degree of definition for your skin, the risks and the recovery required.
What should I prepare before consultation?
- Your main concern — round, square, heavy, or the whole nose.
- Front and three-quarter photographs in even light without makeup — the tip’s light reflex shows best here.
- Your skin history — oiliness, pore size, acne, how scars have healed.
- All medicines and supplements, including isotretinoin, blood thinners and herbal products.
- Medical and surgical history, including anaesthetic problems and breathing issues.
- Previous nasal treatments — fillers (and when), threads, prior rhinoplasty — with approximate dates.
- Reference photographs, useful for discussing goals — not as a target to replicate; filtered or edited images are not a realistic reference.
Is an online tip consultation possible?
If you are outside Mumbai, you can request a preliminary WhatsApp photo pre-check with front, three-quarter, basal and side photographs in even, natural lighting, without makeup or filters. This is preliminary guidance only. Photographs cannot assess skin thickness, cartilage strength, tip support, valve function or medical fitness, and no definitive diagnosis, technique recommendation or final quotation can be given from them.
Consultation fee: ₹1,500
Link: How to prepare
Which Techniques Are Used in Bulbous & Boxy Tip Correction?
“Technique” in tip correction refers to how the lower lateral cartilages are reshaped and supported — sutures that narrow the domes, conservative trimming of excess cartilage width, grafts that add definition or strength, and selective management of thick soft tissue — and whether the tip is reached through an open or closed approach. These are surgical decisions made from your anatomy, not a menu.
The philosophy is shape and support, not removal. A good tip should look softer, cleaner and more balanced, while still breathing well.
| Technique | Purpose | Used for | Key caution |
|---|---|---|---|
| Transdomal (dome-binding) sutures | Refine dome shape | Bulbous or broad domes | Avoid over-narrowing |
| Interdomal sutures | Adjust distance between domes | Boxy or widely spaced domes; bifid tip | Maintain natural contour |
| Conservative cephalic trim | Reduce excess cartilage width | Selected broad tips | Over-resection can destabilise |
| Lateral crural strut / turn-in flap | Strengthen and flatten convex lateral crura | Bulbous tips with weak or bowed cartilage | Technique-specific |
| Columellar strut / septal extension graft | Stabilise tip position | Weak support, thick skin, projection needs | Must suit anatomy |
| Tip graft | Improve definition / support | Weak or under-defined tips | Can show in thin skin |
| Shield graft | Improve definition / projection | Selected cases | Must avoid artificial projection |
| Soft-tissue management (supratip debulking) | Thin the fibrofatty envelope | Selected thick-skin cases | Must preserve vascularity |
| Open approach | Better exposure | Complex, thick-skin or grafted cases | Small columellar scar |
| Closed approach | Internal incisions | Selected limited refinements | Less exposure |
Suture reshaping: Fine permanent sutures placed across each dome narrow a broad, convex cartilage into a defined point; a second suture between the domes brings them together. This is the workhorse of modern tip surgery — it creates definition without removing the cartilage that holds the nostril open.
Conservative trim: Where the lower lateral cartilage is truly too wide, a strip is removed from its upper edge — but always leaving a generous rim of cartilage (classically at least 6–7 mm) so the sidewall does not collapse or retract.
Support and definition grafts: A strut between the medial crura, or an extension graft off the septum, gives the tip a fixed anchor so it holds projection and rotation. In thick skin, a tip graft on top of the domes pushes definition through the envelope.
Soft-tissue management: In selected thick-skin noses, the fibrofatty layer over the tip and supratip is conservatively thinned so the refined cartilage can show. This must be done sparingly to protect blood supply to the skin.
Is open rhinoplasty always better than closed for a bulbous tip?
No. Neither approach is universally superior — and “open” or “closed” describes access, not what is done to the cartilage.
- Anatomy matters most. Precise suture work, grafting and soft-tissue thinning in a thick-skinned or boxy tip are far more controllable under direct vision; a mildly bulbous tip with thin skin can often be refined closed.
- Surgeon experience matters. A technique performed well within a surgeon’s established expertise generally serves a patient better than an unfamiliar one chosen for its label.
- Symmetry matters. Comparing both domes side by side — possible only open — is the best safeguard against an asymmetric tip.
- Scar is minor either way. The open columellar scar is a few millimetres and usually fades to near-invisible; it should not be the deciding factor.
The right question at consultation is not “do you do closed?” but “which approach does my tip need, and why?”
Links: Open technique · Closed technique · Tip plasty techniques
Sources: PubMed 34936611 · PMC3901916
What Are the Types of Bulbous & Boxy Tip Correction?
Where technique describes how the cartilage is handled, type describes the scope — whether the tip is treated alone or with the rest of the nose, and which tip problem dominates.
- Focused bulbous tip refinement — for a round tip on an otherwise balanced nose. Dome sutures with or without conservative trim and a strut. Often closed in thin skin, open in thick skin. The most limited option.
- Boxy tip correction — for a square tip from widely spaced domes. Interdomal and transdomal sutures bring the domes together and round the corners; a small tip graft may soften the shape.
- Thick-skin tip correction — for the classic Indian bulbous tip. Structural support (strut / extension graft) plus a tip graft and conservative soft-tissue thinning, so definition pushes through the envelope. Expectations are set realistically. → Ethnic Rhinoplasty
- Bifid tip correction — for a visible groove between two separated domes. Interdomal sutures, sometimes with a graft to fill the cleft.
- Tip correction with alar base reduction — when a boxy tip comes with flared nostrils; the base is sized to the new tip. → Wide Nostril Correction
- Tip correction with full rhinoplasty — when the bridge also needs narrowing, a hump reduced or the nose straightened. The tip is refined as part of a whole-nose plan. → Rhinoplasty Surgery
- Revision tip correction — for a pinched, asymmetric, retracted or collapsed tip after earlier over-resection. Missing cartilage is rebuilt with ear or rib grafts; technically more demanding. → Revision Rhinoplasty
Combined planning: add bridge, base or chin work only when it solves a separate anatomical concern; a refined tip under a wide bridge can look mismatched, so the whole nose is assessed even when only the tip is treated.
Non-surgical options: filler usually cannot reduce a bulbous tip, because it does not remove soft tissue or reshape cartilage. It may camouflage selected minor contour concerns — for instance a small amount above the tip to create a tip break — but nasal filler carries vascular risk and should not be treated as a casual shortcut. → Non-Surgical Rhinoplasty
How is a bulbous or boxy tip different from a broad nose or wide nostrils?
| Concern | Main area | Typical appearance | Owned by |
|---|---|---|---|
| Bulbous tip | Nasal tip | Round, full, under-defined tip | This page |
| Boxy tip | Nasal tip | Square, broad, angular tip | This page |
| Broad nose | Bridge, sidewalls, base or overall width | Nose looks wide overall | Broad nose correction |
| Wide nostrils | Alar / nostril base | Wide nostril opening or wide base | Wide nostril correction |
| Drooping tip | Nasal tip position | Tip hangs down, worse when smiling | Drooping tip correction |
This distinction prevents the wrong surgery. A patient may have a narrow bridge with a bulbous tip; another may have a broad bridge but a non-bulbous tip; another may have wide nostrils but a reasonably defined tip. Tip refinement alone does not correct a wide bony vault, and nostril-base narrowing does not automatically refine a bulbous tip.
Sources: NCBI – Nasal Tip Surgery (StatPearls) · PubMed 20442073 · NBK558970
How Is Bulbous & Boxy Tip Correction Performed Step-by-Step?
Tip correction supports the tip first, then shapes it, then — only where needed — trims it, so definition never comes at the cost of strength. Incisions sit inside the nostrils (closed) or inside the nostrils plus a small cut across the columella (open).
| Step | What happens |
|---|---|
| 1. Consultation and planning | Cause of roundness identified (cartilage, spacing, support, skin); focused tip vs full rhinoplasty decided; open or closed approach and graft source chosen; alternatives, risks and recovery discussed |
| 2. Preoperative preparation | Medical assessment, investigations, anaesthetic review, medication and supplement adjustment (isotretinoin stopped well in advance), confirmed nicotine cessation, standard photographs |
| 3. Surgical markings | Tip-defining points, dome positions, planned suture sites, supratip break and existing asymmetry marked with the patient upright |
| 4. Anaesthesia | General anaesthesia (local with sedation for selected closed cases); local anaesthetic with adrenaline to limit bleeding. Monitoring is continuous |
| 5. Incision and exposure | Closed or open approach; skin and soft tissue lifted off the tip cartilages in the correct plane to protect blood supply |
| 6. Cartilage assessment | Both lower lateral cartilages exposed and compared for width, convexity, spacing and strength; plan confirmed or adjusted |
| 7. Graft harvest (if planned) | Septal cartilage taken for strut, extension or tip grafts (ear cartilage in revision or cartilage-poor noses) |
| 8. Support | Columellar strut or septal extension graft placed and fixed so the tip has a stable anchor |
| 9. Conservative trim (if needed) | Excess upper edge of the lateral crura removed, leaving a generous rim to protect the valve and nostril position |
| 10. Suture reshaping | Transdomal sutures narrow each dome; interdomal sutures bring the domes together; symmetry checked side by side |
| 11. Definition and soft tissue | Tip or shield graft placed if definition needs help; conservative supratip soft-tissue thinning in selected thick-skin cases |
| 12. Closure, taping and observation | Incisions closed with fine sutures; tip taped (and splinted if bone work was combined); monitored recovery, day-care or overnight |
Surgical elements and devices
| Element / device | Possible role | Important consideration |
|---|---|---|
| Permanent fine sutures (5-0 / 6-0 PDS or nylon) | Dome shaping, interdomal narrowing, graft fixation | Placement and tension decide the shape; must not cut through cartilage |
| Septal cartilage | Strut, extension and tip grafts | Preferred graft; may be scarce in revision |
| Ear (conchal) cartilage | Tip / shield grafts when septum unavailable | Additional donor site; naturally curved |
| Rib (costal) cartilage | Structural grafts in major revision | Warping risk; rarely needed for primary tip work |
| Crushed / morselised cartilage | Soften graft edges in thin skin | Prevents visible graft outline |
| Absorbable sutures | Soft-tissue and skin closure | Columellar skin sutures removed at about a week |
| Tapes and (if combined) external splint | Compress supratip swelling, hold tip position | Night taping may continue for weeks in thick skin |
| Steroid injection (post-op, selected) | Reduce stubborn supratip swelling in thick skin | Used sparingly; timing and dose surgeon-controlled |
Sources: PubMed 34936611 · PMC3901916 · NCBI – Nasal Tip Surgery (StatPearls)
When Will I See Final Bulbous & Boxy Tip Correction Results?
The tip is the slowest part of the nose to reveal its result. A narrower shape is visible when tapes come off at about a week, but the tip and supratip stay swollen and rounded for months, particularly in thick skin. A clearer sense of definition emerges at 2–3 months, contours refine through 6–9 months, and final tip definition may take 12 months — or up to 18 in very thick-skinned or revision noses.
| Time | What you may notice |
|---|---|
| First few days | Tip swollen, numb and firm; tapes on. The tip may look rounder than before surgery — this is swelling, not the result |
| 1 week | Tapes and columellar sutures removed. Shape narrower but tip still full; supratip puffy |
| 2–4 weeks | Bruising gone; nose presentable in public. Tip still noticeably swollen, especially in thick skin |
| 2–3 months | Definition begins to show; tip-defining points become visible in thin and medium skin |
| 6 months | Most of the intended shape visible; supratip fullness settling. Thick skin still catching up |
| 9–12 months | Final definition in most patients; tip feels softer and more natural |
| 12–18 months | Final result in very thick-skinned, grafted and revision tips. Revision, if ever considered, waits until here |
What can affect the final result?
Skin thickness and sebaceous quality above all; cartilage strength and how much reshaping was possible; graft take and stability; whether soft-tissue thinning was done; previous nasal surgery or fillers; smoking and nicotine exposure; individual scar and swelling response; adherence to taping and follow-up; and weight change or sun exposure during the first year.
Sources: NCBI – Rhinoplasty (StatPearls) · PubMed 20442073
What Is the Aftercare After Bulbous & Boxy Tip Correction?
Aftercare after tip surgery centres on protecting the reshaped cartilage and controlling tip swelling — head elevation, taping as instructed, no pressure or rubbing on the tip, no nicotine, and patience with a slow-settling tip. These are general principles — your written personal instructions always take priority.
What care is usually advised?
- Keep your head elevated on two pillows for the first week or as instructed; tip swelling is gravity-sensitive.
- Protect the tapes — keep them dry; do not press, adjust or remove them. Night taping may continue for several weeks in thick skin.
- Do not touch, squeeze or “check” the tip — sutured cartilage needs weeks to hold its new shape.
- Do not blow your nose for the period advised; sneeze with the mouth open.
- Use saline spray and ointment inside the nostrils as shown.
- Take medicines exactly as prescribed and do not restart blood-thinning medicines or supplements without approval.
- Walk gently — short walks support circulation; bending, straining and exercise wait until cleared.
- Attend all follow-up appointments — tape and suture removal, swelling review, and in thick skin the occasional supratip steroid injection if advised.
What should patients avoid after tip correction?
| Avoid | Why |
|---|---|
| Smoking, vaping, nicotine in any form | Reduces blood supply to the tip skin — the most vulnerable area after soft-tissue thinning; increases healing problems |
| Glasses resting on the nose (4–6 weeks, or as advised) | Pressure deforms healing tip and supratip; tape glasses to the forehead or use contact lenses |
| Rubbing, wiping or pinching the tip | Can shift sutures and grafts before they scar in |
| Sleeping on your side or face | Pressure on one side can push the tip asymmetric |
| Strenuous exercise and heavy lifting (2–4 weeks) | Raises blood pressure and swelling |
| Swimming, steam, sauna, hot yoga | Heat and moisture increase tip swelling |
| Direct sun on the nose | Worsens swelling and can darken the columellar scar |
| Facials, extractions, harsh skincare on the tip (6 weeks) | Traction and inflammation over healing soft tissue |
| Nasal filler near the tip (12 months) | Interferes with healing; vascular risk |
| Judging your result in the first months | Tip swelling makes early shape unrepresentative — especially in thick skin |
Full aftercare detail: Rhinoplasty recovery timeline
What Are the Risks and Complications of Bulbous & Boxy Tip Correction?
Tip correction is generally safe for an appropriately selected patient operated on by a trained plastic surgeon in an equipped facility, but it is cartilage surgery on the most visible part of the nose, with recognised risks. Expected postoperative effects must be separated from true complications — and no surgeon can eliminate risk.
Common / expected early effects (normal healing, not complications): tip swelling and firmness lasting months; numbness of the tip; a blocked feeling; mild aching; temporary asymmetry during the swelling phase; a rounded supratip that settles slowly.
Uncommon complications: bleeding; infection; asymmetry of the domes after healing; under-correction (tip remains too full or boxy); over-correction (tip looks too narrow or artificial); supratip / polly-beak fullness; prolonged swelling, more likely in thick skin; visible graft edge or irregularity, more noticeable in thin skin; suture visibility or extrusion; prolonged numbness; dissatisfaction leading to a revision request.
Rare but important: pinched tip with external valve narrowing; alar retraction (nostril rim pulled up); loss of tip support with drooping; skin compromise after aggressive soft-tissue thinning, most strongly associated with nicotine; anaesthesia-related complications. After nasal filler (not surgery): vascular occlusion with skin blanching or vision symptoms — an emergency.
How risk is minimised
| Risk area | How we work to minimise it |
|---|---|
| Wrong diagnosis (tip vs bridge vs base) | Whole-nose assessment at consultation; tip treated alone only when the rest is balanced |
| Over-resection / pinching / retraction | Suture-first reshaping; cephalic trim kept conservative with a generous cartilage rim; lateral crura reinforced where weak |
| Loss of support | Strut or extension graft placed before shaping in weak or thick-skin tips |
| Asymmetry | Open approach for complex tips so both domes are compared side by side; upright marking |
| Visible grafts in thin skin | Graft edges bevelled or morselised; grafts avoided where not needed |
| Prolonged thick-skin swelling / polly-beak | Conservative soft-tissue management, taping protocol, selective supratip steroid injection at follow-up |
| Undetected medical risk | Preoperative medical evaluation, investigations and anaesthetic review before scheduling |
| Nicotine-related healing failure | A clear, enforced nicotine cessation requirement before and after surgery |
| Bleeding | Medication and supplement review, blood-pressure control, meticulous haemostasis |
| Infection | Sterile technique, theatre sterilisation protocols, perioperative antibiotics, wound-care instruction |
| Facility and equipment risk | Surgery at an NABH-accredited surgical centre with appropriate equipment |
| Delayed recognition of a problem | Structured postoperative observation, written warning signs, accessible follow-up |
⚠️ When to seek urgent medical attention
Seek urgent advice or immediate emergency care for: heavy bleeding · fever · worsening pain or redness · rapidly increasing swelling · worsening nasal obstruction after initial improvement · pale, dusky or painful skin at the tip · after any nasal filler: blanching, colour change, severe pain, eye pain or any vision symptom · chest pain or breathlessness.
In an emergency, go to the nearest emergency department or call emergency services. Do not wait for a WhatsApp or email reply.
Full risk guide: Rhinoplasty Risks & Safety
Sources: PMC3901916 · NCBI – Rhinoplasty (StatPearls) · PMC6624005 · PMC4859242
What Is the Bulbous & Boxy Tip Correction Recovery Timeline?
Recovery after tip correction is short in terms of downtime and long in terms of settling. Bruising is minimal when no bone work is done; tapes and columellar sutures come off at about a week; most patients return to desk work within 7–10 days. The tip, however, keeps refining for 12 months or longer — the nasal tip heals more slowly than the bridge because it has thicker soft tissue over reshaped cartilage, especially in thick-skin or open-approach cases. This is a summary — for detailed day-by-day guidance, see the rhinoplasty recovery timeline.
| Timepoint | What typically happens |
|---|---|
| First 24–48 hours | Tapes on the tip and supratip; swelling, numbness, blocked nose and mild aching expected. Little bruising if no osteotomies. Rest head-elevated; day-care discharge or overnight observation |
| Days 3–7 | Swelling starts reducing. Saline spray and ointment routine. Tapes and columellar sutures removed at the first follow-up around day 7 |
| Weeks 2–3 | Presentable in public; many patients return to desk work. Tip still full and firm; night taping may continue in thick skin |
| Weeks 4–6 | Exercise, glasses and travel usually cleared at review. Supratip fullness begins to soften |
| 3–6 months | Definition emerges; tip-defining points visible in thin and medium skin. Selective supratip steroid injection if swelling is stubborn |
| 9–12 months | Final shape in most patients; tip feels soft and natural |
| 12–18 months | Final result in very thick-skinned, grafted and revision tips. Revision assessment waits until here |
Key recovery points: downtime is about a week; settling is about a year · the tip will look rounder than expected for the first months — this is swelling over a reshaped framework, not a failed result · night taping in thick skin genuinely speeds settling · glasses stay off the nose for 4–6 weeks · flying requires written clearance at follow-up — do not book non-refundable travel around an assumed date · outstation patients usually stay in Mumbai until tapes and sutures are removed.
Do not use another patient’s timeline as permission for glasses, exercise, travel or restarting medication.
Links: Recovery timeline day 1 to final result · Outstation patients
Medical Codes for Bulbous & Boxy Tip Correction
Codes below are for administrative and documentation reference. All codes must be verified against the current CPT and ICD-10 code sets before publication and before any use in documentation.
| CPT Code | CPT Description | ICD-10 |
|---|---|---|
| 30400 | Rhinoplasty, primary; lateral and alar cartilages and/or elevation of nasal tip (focused tip surgery) | Z41.1 (cosmetic) · M95.0 (acquired deformity of nose) |
| 30410 | Rhinoplasty, primary; complete, external parts including bony pyramid, lateral and alar cartilages, and/or elevation of nasal tip (tip with full rhinoplasty) | Z41.1 · M95.0 |
| 30420 | Rhinoplasty, primary; including major septal repair (when combined with septoplasty) | J34.2 · M95.0 |
| 30430 | Rhinoplasty, secondary; minor revision (small amount of nasal tip work) | Z41.1 · Z98.890 |
| 30450 | Rhinoplasty, secondary; major revision (nasal tip work and osteotomies) | M95.0 · Z98.890 |
| 21235 | Graft; ear cartilage, autogenous, to nose or ear | — |
| 20912 | Cartilage graft; nasal septum (septal cartilage harvest for tip grafts) | — |
(FAQs) Frequently Asked Questions About Bulbous & Boxy Tip Correction
Q1. Can tip correction fail or need revision?
Ans. Yes. Under-correction (tip still full), over-correction (pinched), asymmetry, visible graft edges or stubborn supratip fullness can occur. Under-correction and fullness are often manageable; over-resection is much harder and needs cartilage grafts to rebuild. Revision is assessed only after 12 months of settling — longer in thick skin.
Q2. Is tip correction safe in India?
Ans. It is generally safe for an appropriately selected patient when performed by a qualified plastic surgeon in an accredited facility with proper anaesthetic support. Recognised risks remain — asymmetry, pinching, prolonged swelling. Judge the surgeon’s qualification, rhinoplasty volume and experience with thick-skinned noses, not the country.
Q3. How long does tip correction surgery take?
Ans. Focused tip surgery usually takes 1.5–2.5 hours; with full rhinoplasty, 2–3 hours or more. Grafting and revision take longer. The planned duration is confirmed only after examination and surgical planning.
Q4. What techniques are used for bulbous tip correction?
Ans. Techniques may include transdomal and interdomal sutures, conservative cephalic trim, lateral crural support, columellar strut or septal extension grafts, tip and shield grafts, and selective soft-tissue management. The method depends on skin thickness, cartilage shape, support and desired refinement.
Q5. Why is over-resection risky?
Ans. Over-resection can create a pinched tip, alar retraction, visible irregularity, asymmetry or external valve collapse. The tip cartilage supports both shape and airflow, so correction should reshape and support rather than simply remove tissue.
Q6. Can closed surgery correct a bulbous or boxy tip?
Ans. Closed surgery may suit selected limited refinements in thinner skin, while open surgery gives better exposure for complex cartilage reshaping, thick-skin cases, grafting or asymmetry. The correct approach depends on anatomy and surgeon assessment.
Q7. Can filler correct a bulbous tip?
Ans. Filler usually cannot reduce a bulbous tip, because it does not remove soft tissue or reshape cartilage. It may camouflage selected minor contour concerns, but nasal filler carries vascular risk — blanching, severe pain, eye pain or any vision change after filler is an emergency — and should not be treated as a casual shortcut.
Q8. Can bulbous tip correction affect breathing?
Ans. Yes, if the tip is over-narrowed or lower lateral cartilage support is weakened. The external nasal valve depends partly on tip support, so the surgical goal must include stable airflow as well as improved shape. Support-first techniques usually protect or improve breathing.
Q9. Will my thick skin ever show the result?
Ans. Yes, but slowly and with limits. Structural support and a tip graft push definition through the envelope, night taping and occasional supratip steroid injections speed settling, and the result typically appears between months six and twelve. It will be a defined, elegant tip — not a thin-skinned, razor-sharp one.
Q10. When can I fly after tip correction?
Ans. Only after written clearance at a follow-up review, usually once tapes and sutures are off and there is no bleeding concern. Outstation patients typically stay in Mumbai for about a week. Do not book non-refundable travel around an assumed date.
Q11. Does insurance cover bulbous tip correction?
Ans. Cosmetic tip rhinoplasty should not be assumed to be covered by health insurance. Coverage, where it exists at all, applies only to documented functional indications — for example external valve collapse — and must be confirmed directly with your insurer before surgery.
Related Links
- Rhinoplasty Surgery (hub)
- Rhinoplasty Cost
- Rhinoplasty Before & After Gallery
- Nasal Tip Plasty
- Drooping Tip Correction
- Broad Nose Correction
- Wide Nostril Correction
- Crooked Nose Correction
- Ethnic Rhinoplasty
- Open Rhinoplasty Technique
- Closed Rhinoplasty Technique
- Nasal Deformities Treated by Rhinoplasty
- Revision Rhinoplasty
- Rhinoplasty Recovery Timeline
- How to Prepare for Rhinoplasty
- Rhinoplasty Risks & Safety

