
Drooping Tip Correction in Mumbai: A Naturally Lifted, Balanced Nasal Tip That Stays Put

Indian Board Certified Plastic Surgeon
M.CH, MS, ISAPS Mentor
16000+ Cosmetic Surgeries
1500+ Rhinoplasty Surgeries
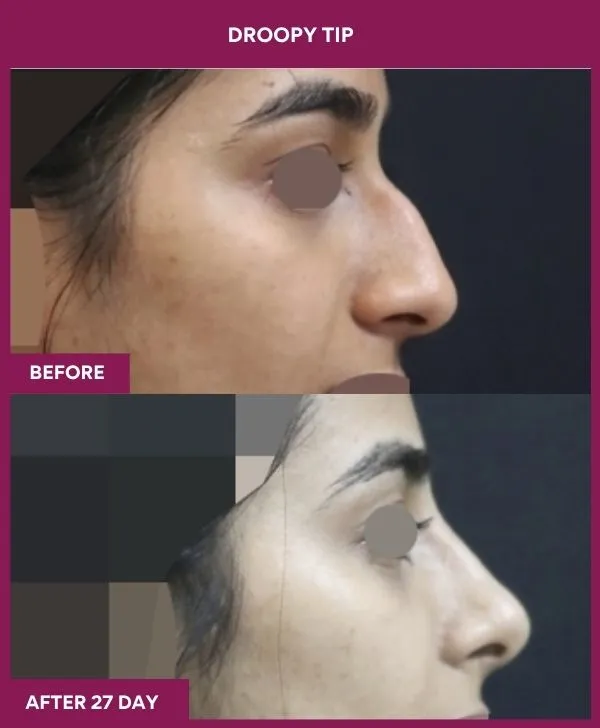
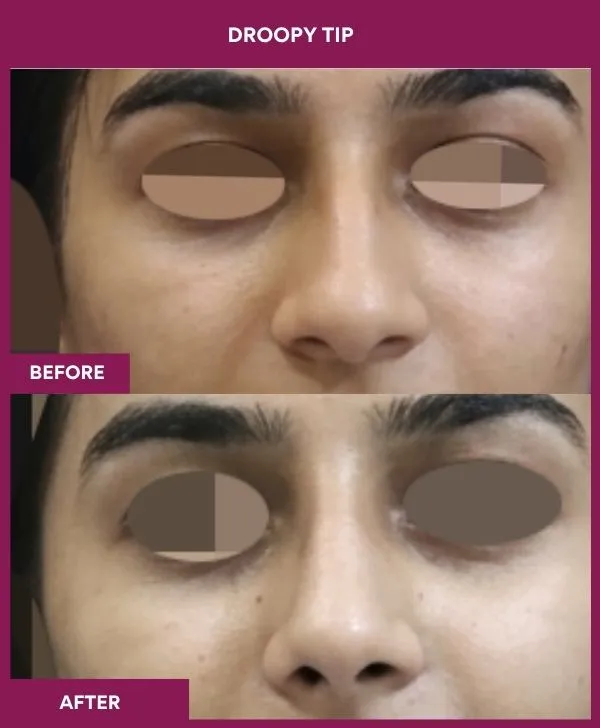
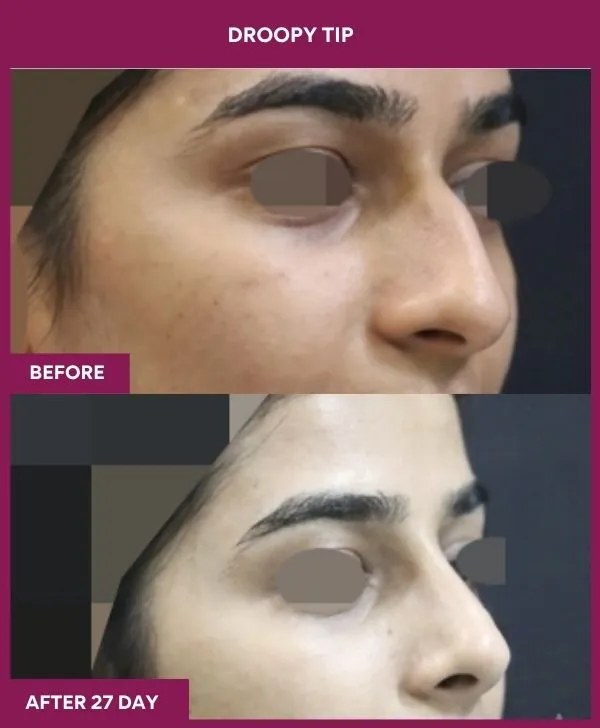
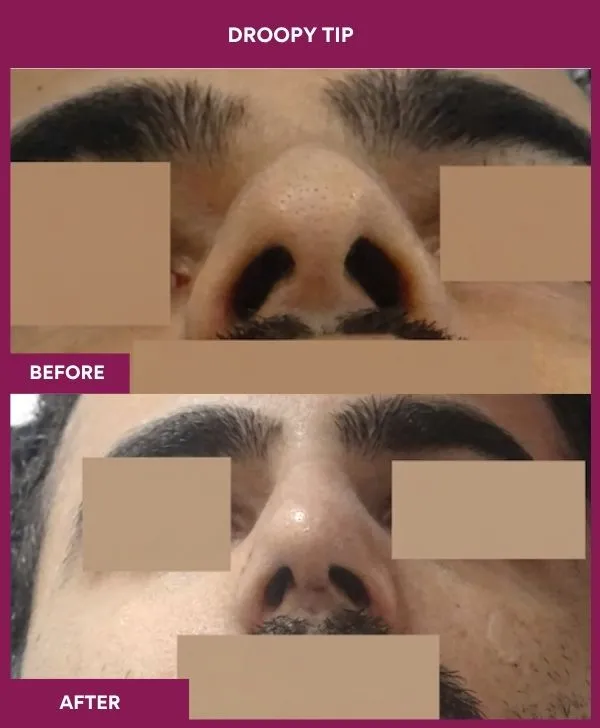
Drooping tip correction lifts and supports a nasal tip that sits too low — making the nose look long, heavy or “hanging” from the side, or dropping further every time you smile — by rotating the tip a controlled few degrees and anchoring it so it stays there. At Allure Medspa Mumbai, Dr. Milan Doshi first finds what is pulling the tip down — weak support, a long septum, heavy skin or the smile muscle — so the lift looks light and natural, never upturned.
Augmentation Rhinoplasty Before And After Images
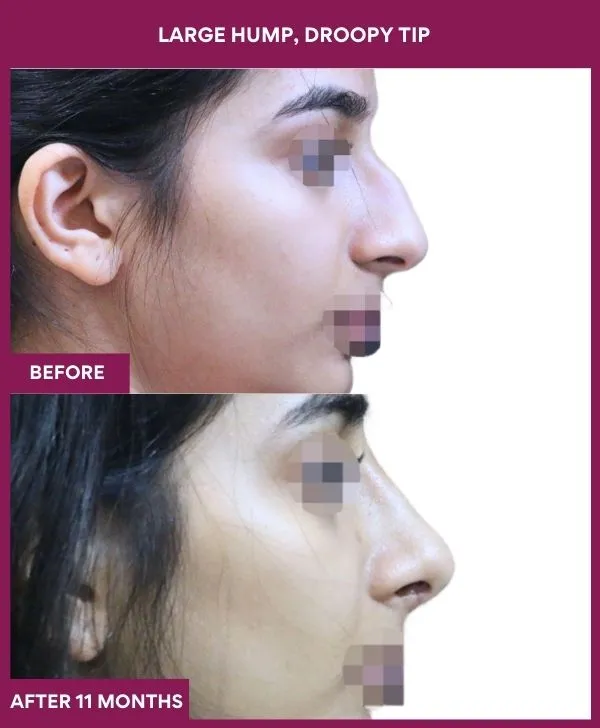

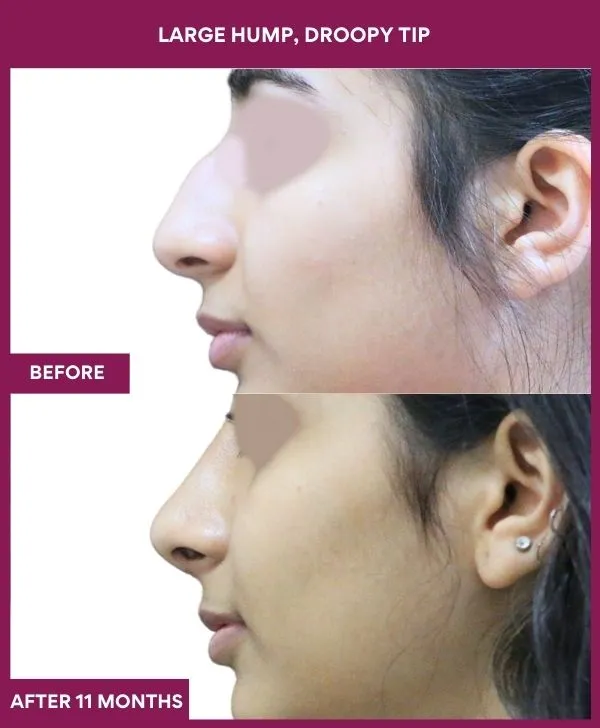
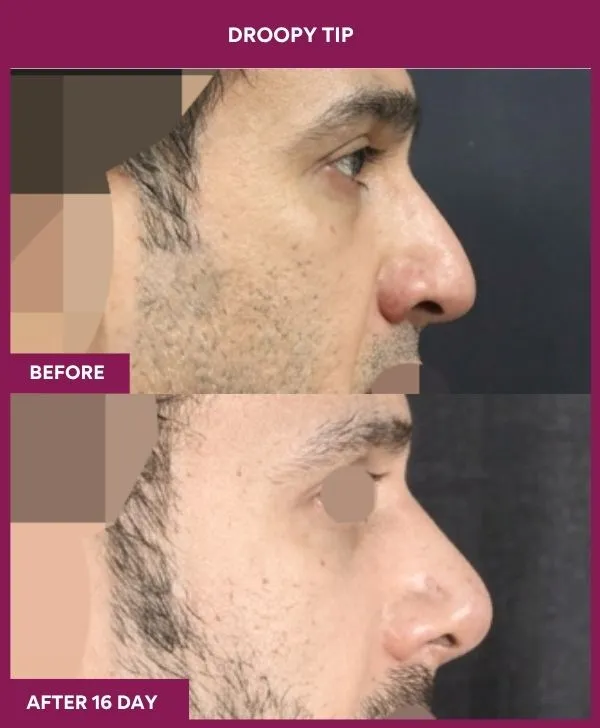
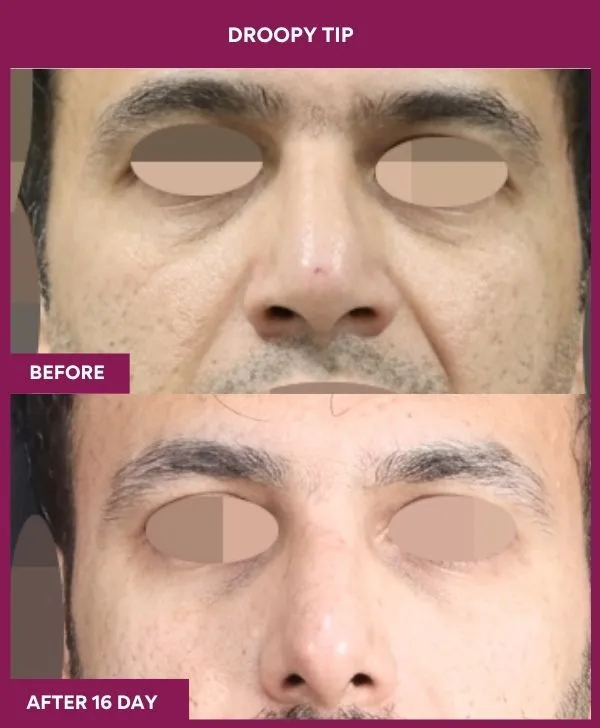
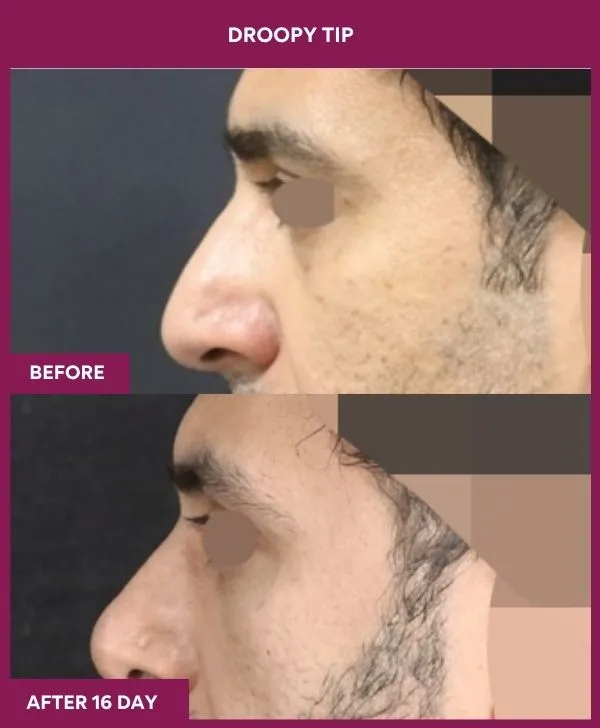
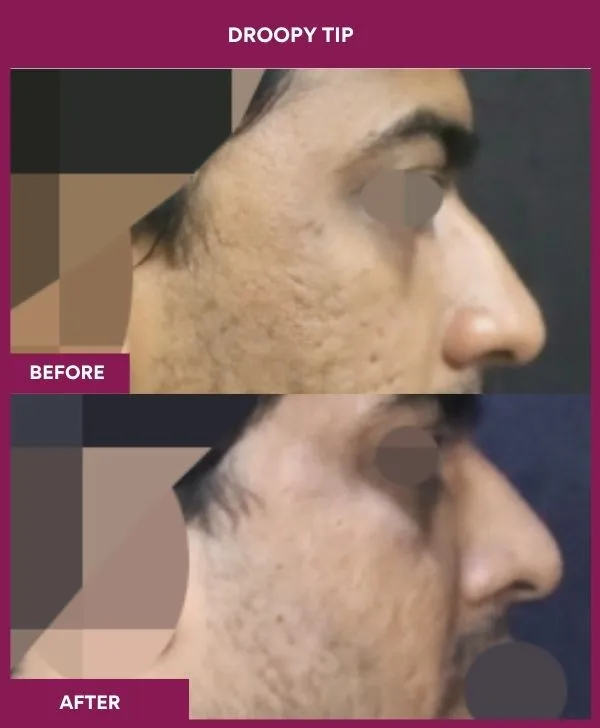
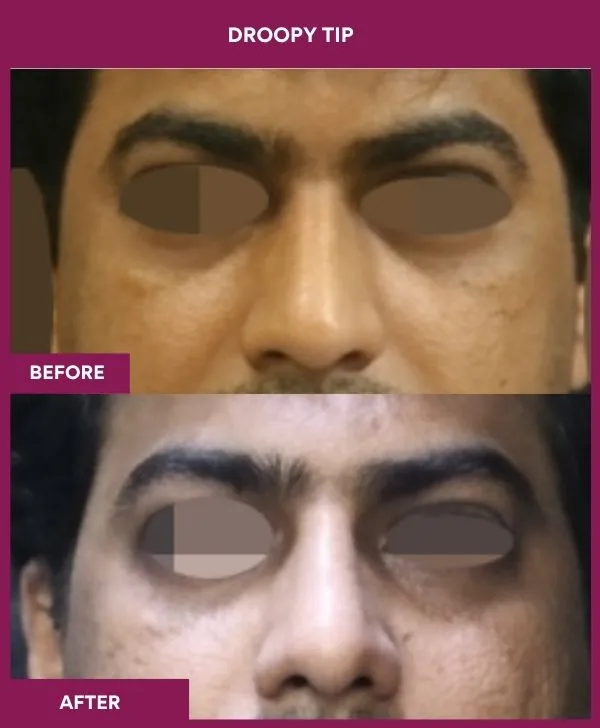
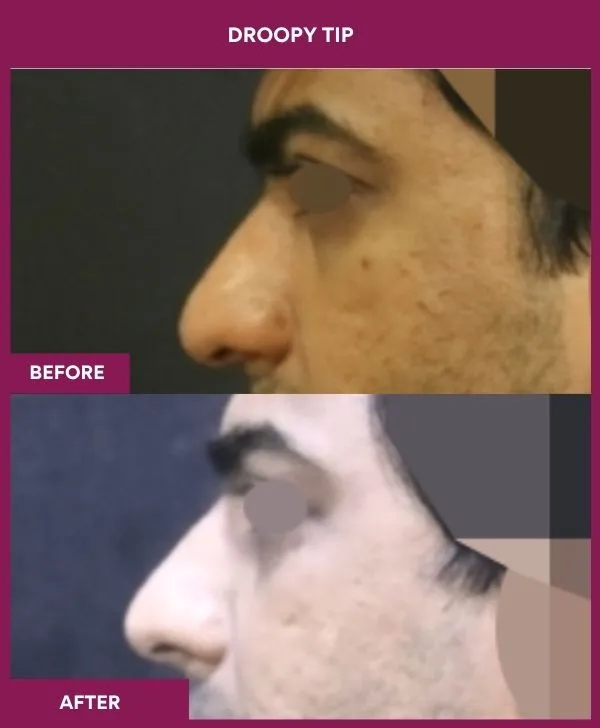
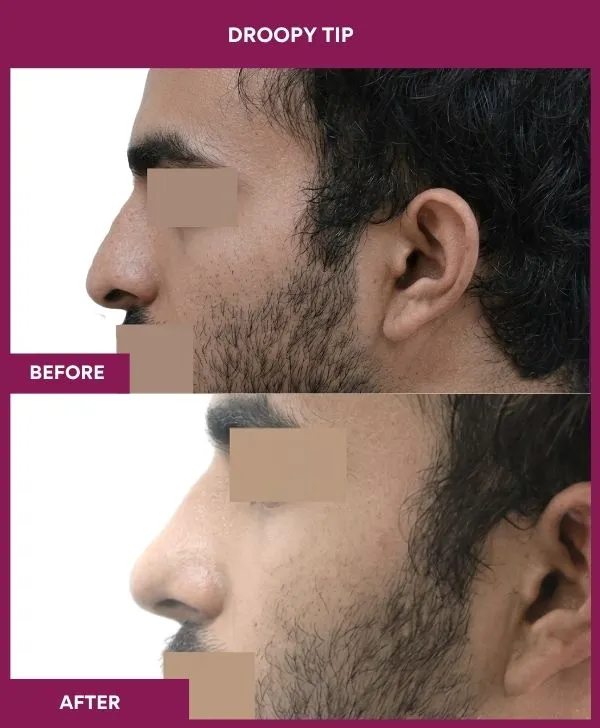
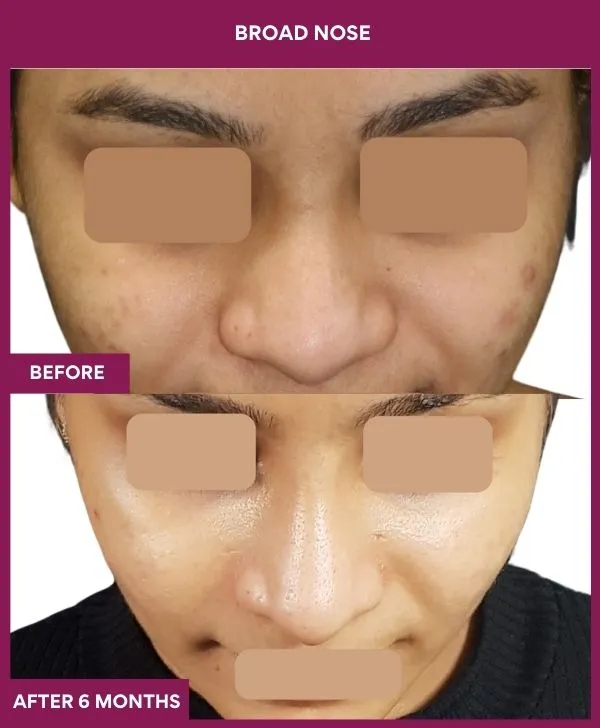
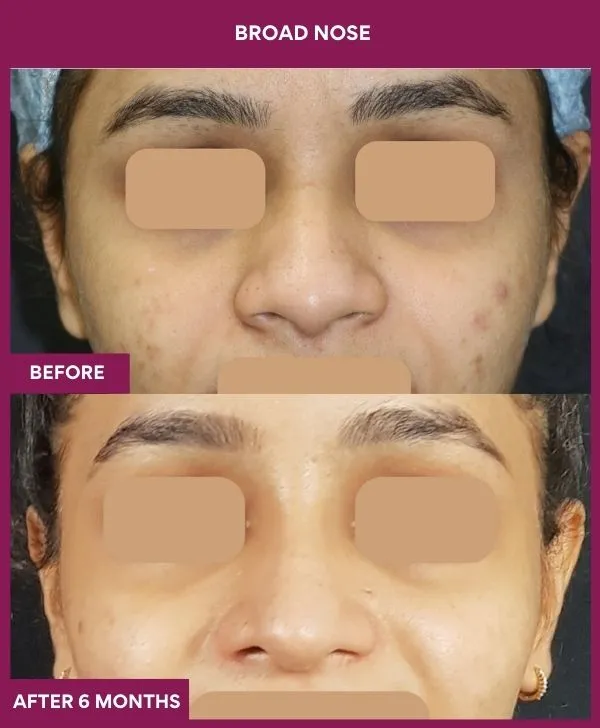
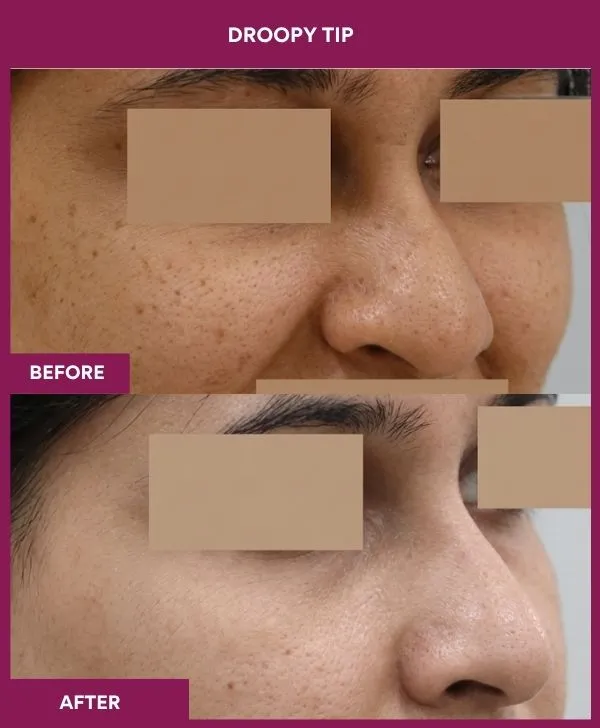
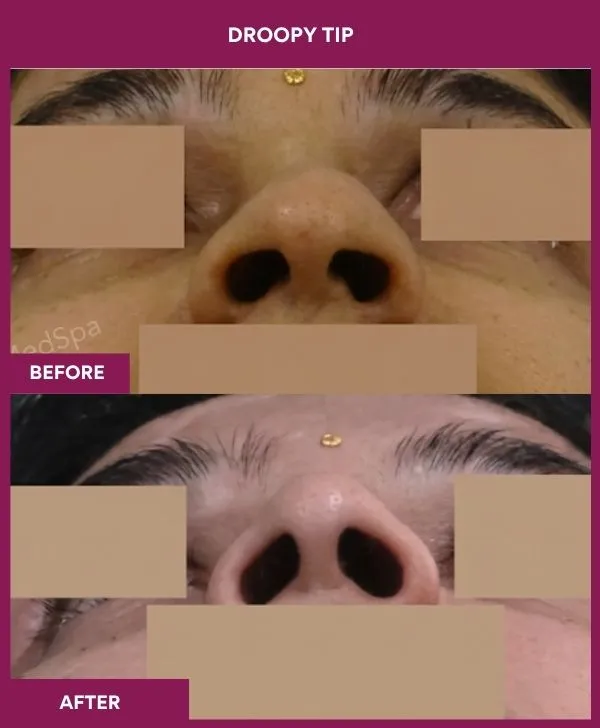
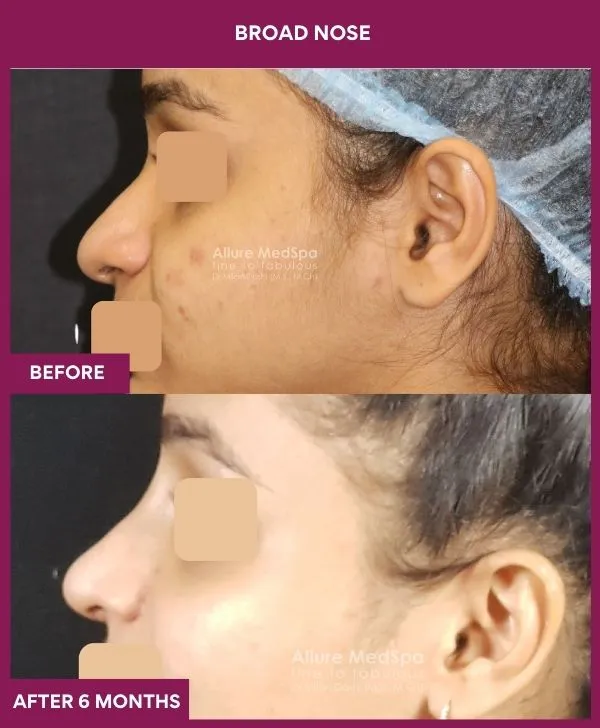
Rhinoplasty Surgery Testimonials: Celebrities Patient

Awarded by Google.com
Rating: 4.7
Reviews: 485+

Awarded by WhatClinic.com
Rating: 4.8
Reviews: 119+

Awarded by Realself
Rating: 4.9
Reviews:453+

Awarded by Facebook
Rating: 4.6
Reviews:105+
Dr Milan Doshi and his staff are very professional and committed as the centre is highly equipped with advanced technology. I had closed rhinoplasty 4 months back and I’m seeing the results as to how it becomes successful.
Deepika Shetty
The doctor explained everything clearly and the surgery was smooth. Recovery was faster than I expected and the team was very supportive.
Rahul Mehta
Very natural results and excellent staff. From consultation to follow-up, the experience was outstanding and boosted my confidence.
Sneha Kapoor
Video: Best Rhinoplasty Surgeon explain nose reshape procedure
Dr Milan Doshi is describing the Rhinoplasty Surgery in detail with benefits, techniques, recovery, result, risk and complecations
Am I a Candidate?
(4 quick questions)
Quick Facts About Drooping Tip Correction
TIME REQUIRED
2–3 hours
ANESTHESIA
General
HOSPITAL STAY
Day-care or 1 night
PAIN LEVEL
Mild–moderate
BACK TO WORK
7–10 days
RESULTS LAST
Long-lasting
SUCCESS RATE
97–98%
COMPLICATIONS
Under 2-3%
How Much Does Drooping Tip Correction Cost in Mumbai?
Drooping tip correction in Mumbai starts from ₹70,000 to ₹1,80,000 as a focused tip procedure and varies with whether the droop is dynamic, static or mixed, the support technique required (strut, septal extension, tongue-in-groove), whether the caudal septum needs shortening, whether grafts are needed and from where, anaesthesia, and whether the tip is being done alone or as part of full rhinoplasty. Revision cases are quoted after examination. A final quotation follows examination and a written surgical plan — it cannot be given accurately by phone or from photographs.
| Drooping tip correction scope | Indicative price range |
|---|---|
| Dynamic droop only — depressor septi release (surgical) | ₹70,000 – ₹90,000 |
| Mild static droop — columellar strut + tip sutures | ₹90,000 – ₹1,20,000 |
| Moderate droop — septal extension graft / tongue-in-groove | ₹1,10,000 – ₹1,50,000 |
| Droop with long caudal septum — septal shortening + support | ₹1,20,000 – ₹1,60,000 |
| Mixed droop — structural support + depressor septi release | ₹1,20,000 – ₹1,70,000 |
| Droopy AND bulbous tip — rotation support + tip refinement | ₹1,30,000 – ₹1,80,000 |
| Tip lift as part of full rhinoplasty / septorhinoplasty | Included in rhinoplasty plan — see rhinoplasty cost guide (₹1,00,000–₹3,50,000) |
| Revision droopy tip (previous rhinoplasty, ear / rib graft) | Quoted after examination |
| Botulinum toxin for dynamic droop (non-surgical, temporary) | Quoted per session at consultation |
Get your exact quote & surgery plan
Share your details — our team responds within working hours with cost, EMI options and next steps.
Most Common Question People Ask
Q1. Why does my nose tip droop when I smile?
Ans. This is often dynamic droop caused by depressor septi nasi muscle activity — the muscle pulls the tip downward during smiling or speaking. Some patients need treatment of that muscle, but structural support is also needed if the tip is droopy at rest.
Q2. How much does drooping tip correction cost in Mumbai?
Ans. As a focused tip procedure, the guide range is ₹70,000–₹1,80,000 plus 5% GST. If it is part of full rhinoplasty, pricing changes. The final quote is given after consultation.
Q3. Will my nose look too lifted after surgery?
Ans. It should not if planning is conservative. Over-rotation is a real mistake, because it can create an upturned, artificial, short-nose look. The aim is controlled support and natural rotation, not a visibly operated tip.
Q4. Can a drooping tip be corrected without surgery?
Ans. If the problem is purely dynamic, botulinum toxin may temporarily reduce downward pull from the depressor septi nasi muscle. It does not correct structural droop from cartilage, septum or weak support. Results are temporary and case-dependent.
Q5. Is drooping tip correction the same as rhinoplasty?
Ans. Drooping tip correction is one part of rhinoplasty focused on tip position, rotation and support. If the bridge, nostrils, septum or overall length also need correction, it becomes part of a larger rhinoplasty plan.
Q6. How long does recovery take?
Ans. Most patients resume normal daily activity in about 1–2 weeks. Tip swelling takes months to settle, and final tip rotation is usually judged closer to 6–12 months, especially in thick skin. Early on, the tip may look slightly higher than the final result.
Q7. Will it look natural?
Ans. A natural result depends on lifting the tip only as much as the face needs, anchoring it so it does not drift, and keeping it in balance with the bridge, nostrils and upper lip. The aim is your nose, lighter and better supported — not an upturned one. Results vary between individuals and cannot be guaranteed.

Why Choose Dr. Milan Doshi?
Dr. Milan Doshi, MCh, MS — Indian board-certified plastic surgeon with 27+ years in aesthetic surgery and 1,500+ rhinoplasties, where a few millimetres of tip rotation change the whole expression of the nose. ISAPS mentor, trusted by patients from 70+ countries. Consults at Andheri West; surgeries at the NABH-accredited surgical centre, Goregaon West.
Read his full profile and credentials → About Dr Milan Doshi
🩺 Dr Doshi Note: “Drooping tip correction is a matter of millimetres and judgement. The tip should be lifted only as much as the face needs, and it must be supported properly so the result looks stable and natural. My focus is a lighter, elegant tip that improves facial balance without looking pulled-up or operated.”
The Complete Guide About Drooping Tip Correction
What Is Drooping Tip Correction?
Drooping tip correction is a form of tip rhinoplasty that rotates a low-sitting nasal tip upward by a controlled amount and supports it so it stays there. A drooping tip (nasal tip ptosis) means the nasal tip sits lower than ideal, making the nose look long, heavy or “hanging” from the side. It can be static — visible all the time, a cartilage-support problem — or dynamic — dropping mainly when smiling, pulled by the depressor septi muscle — and each is treated differently.
This distinction matters. Pushing a tip up without addressing what is pulling it down gives a result that drifts back within months. Releasing a smile muscle that was never the problem changes the upper lip for nothing. Diagnosis of the droop type is the single most important step.
What causes a drooping tip?
Most droopy tips come from weak tip cartilage support, a long caudal septum, heavy or thick skin, ageing, previous rhinoplasty, or downward smile-muscle pull. Often two or three causes combine — which is why correct diagnosis comes before any lifting.
| Cause | What it means |
|---|---|
| Weak tip support | Lower lateral cartilages do not hold the tip strongly |
| Long caudal septum | Septal length pushes the tip downward |
| Heavy or thick skin | Soft-tissue weight makes the tip look lower |
| Ageing | Tip support weakens over time |
| Previous rhinoplasty | Prior cartilage disruption may cause de-rotation |
| Long lower lateral cartilages | Long or heavy tip cartilages make the nose look droopy or under-rotated |
| Dynamic muscle pull | Depressor septi nasi pulls the tip down while smiling |
| Weak base support | Insufficient maxillary / anterior nasal spine support |
Static, dynamic or mixed droop
| Type | When it appears | Likely reason | Treatment direction |
|---|---|---|---|
| Static droop | Visible at rest | Weak support, long septum, low rotation | Structural tip support |
| Dynamic droop | Worse while smiling | Depressor septi nasi activity | DSN treatment + support if needed |
| Mixed droop | At rest and worse smiling | Structure + muscle pull | Combined correction |
Is drooping tip correction cosmetic or reconstructive?
| Type | Main purpose | Common example |
|---|---|---|
| Cosmetic (aesthetic) | Lift and support a low tip for a lighter, balanced profile | Primary tip rotation for a hanging tip |
| Functional / reconstructive | Restore tip support and the external valve after ageing collapse, injury or a previous rhinoplasty that lost support | Revision with septal extension graft for a de-rotated, collapsing tip |
Most drooping tip corrections in private practice are cosmetic. Cosmetic tip rhinoplasty should not be assumed to be covered by health insurance; coverage, where it exists, applies only to documented functional indications and requires prior verification with your insurer.
Synonyms for drooping tip correction
Patient terms: droopy nose surgery, hanging nose tip surgery, nose tip lift, nose tip droops when smiling, long nose tip surgery, downward nose tip correction
Medical terms: nasal tip ptosis correction, tip rotation rhinoplasty, cephalic rotation, columellar strut, septal extension graft, tongue-in-groove, caudal septal resection, depressor septi nasi release
Sources: PubMed 19608069 · PMC7700863 · PMC5584101
Does Your Nose Look Longer in Photos Than It Feels?
Many people describe the same experience: from the front the nose is fine, but every side-profile photo shows a tip that seems to hang below the nostrils, making the whole nose look long and the upper lip short — and in smiling photos it gets worse. That gap between the front view and the profile is real, and it is usually tip position, not nose length.
Three questions patients actually ask at consultation:
- “My nose looks fine until I smile — then the tip drops and my lip disappears. Is that fixable?”
- “Will lifting the tip make my nose look short or piggy?”
- “Is my nose long, or is the tip just hanging?”
These concerns do not automatically mean surgery is needed. A mild static droop on a balanced profile may be best left alone; a purely dynamic droop may be trialled with a temporary muscle-relaxing injection before any surgery. A tip that hangs because the whole nose is long needs a broader plan. The useful question is not “how far up can it go?” but “what is pulling it down — and how many degrees does my face actually need?”
Global and Indian trends
Tip rotation is one of the most common goals in rhinoplasty worldwide, and the low, under-rotated tip is a frequent presentation in Indian and South-Asian noses, where heavier tip skin and a long caudal septum often combine. The trend has moved firmly away from the over-rotated, upturned look towards conservative rotation with strong structural support — the approach Allure Medspa uses — because it preserves ethnic profile and does not date.
What Are the Benefits of Drooping Tip Correction?
The main benefits of drooping tip correction are a lighter, shorter-looking profile without changing nose length, a tip that stays in place when you smile and talk, a more visible upper lip, and a supported tip that resists the downward drift of ageing. Because the tip is anchored to structural grafts rather than simply pulled, the correction is stable and long-lasting.
Cosmetic benefits
- A lighter profile — a few degrees of rotation make the nose look shorter and less heavy without removing length.
- A tip that holds its position when smiling — releasing an overactive depressor septi stops the tip dropping and the lip shortening in animation.
- Longer-looking upper lip — as the tip lifts and the septum is shortened, the lip is no longer hidden.
- Cleaner nasolabial angle — the angle between columella and lip opens to a natural range, which is what the eye reads as “elegant” in profile.
- Better tip–bridge relationship — a supported tip restores the subtle supratip break.
- Preserved identity — the aim is your nose, held up; everyone notices better balance, no one knows it was surgery.
Functional benefits
- Structural support (strut or septal extension) strengthens the external nasal valve rather than weakening it.
- A tip that no longer collapses inward on breathing in.
- Support that resists further de-rotation with age.
Which Problems Can Drooping Tip Correction Correct?
Drooping tip correction mainly treats a low or under-rotated tip from weak support, a long caudal septum, heavy skin, ageing or previous surgery, and a tip that drops on smiling from depressor septi pull. It does not reliably correct: a round or bulbous tip (that is a shape problem), a nose that is too long (that is a length problem), a hump or crooked bridge, wide nostrils, or skin thickness itself.
| Concern | Relevance to this page | Possible approach | Learn more |
|---|---|---|---|
| Tip sits low at rest (static droop) | Core target | Columellar strut / septal extension, tongue-in-groove | This page |
| Tip drops when smiling (dynamic droop) | Core target | Depressor septi release ± support | This page |
| Mixed droop | Core target | Structural support + muscle release | This page |
| Long caudal septum pushing tip down | Core target | Caudal septal shortening + support | This page |
| Age-related tip descent | Core target | Structural support | This page |
| Droop after previous rhinoplasty | Revision case | Septal extension graft (ear / rib cartilage) | Revision Rhinoplasty |
| Tip also round / heavy (bulbous) | Combined when present | Rotation support + tip refinement | Bulbous Tip Correction |
| Whole nose too long | Different diagnosis | Reduction rhinoplasty | Reduction Rhinoplasty |
| Hump with a drooping tip | Combined when present | Full rhinoplasty | Nasal Dorsum Deformities |
| Blocked breathing / valve collapse | Assessed first | Functional rhinoplasty | Functional Rhinoplasty |
The anatomy of tip position — the structures this surgery works on
Understanding a few terms makes consultation far easier.
- Tip rotation and the nasolabial angle — how far the tip points up or down, measured as the angle between the columella and the upper lip. Roughly 90–95° in men and 95–105° in women is the natural range; a drooping tip sits below it, an over-rotated one above it.
- Tip support (tripod) — the tip rests on the two lateral crura and the joined medial crura, like a tripod. Shorten or weaken the lateral legs, or lengthen the central one, and the tip rotates; lose all support and it drops.
- Caudal septum — the front edge of the septum, just behind the columella. If it is long, it pushes the tip down and hides the upper lip.
- Medial crura and columella — the central pillar. A strut or extension graft here is what holds a lifted tip in place.
- Depressor septi nasi muscle — a small muscle from the upper lip to the base of the septum. When overactive it pulls the tip down and the lip up with every smile.
- Anterior nasal spine — the bony point at the base of the nose that the septum and tip rest on. A weak spine gives weak base support.
- Skin–soft-tissue envelope — heavy, thick tip skin weighs the tip down and hides fine rotation changes.
What Are the Limitations of Drooping Tip Correction?
Drooping tip correction cannot shorten a nose that is truly long, cannot refine a round tip on its own, cannot make thick skin light, cannot guarantee that a lifted tip will never descend with age, and cannot produce a specific other person’s profile. It rotates and supports what is there. Being clear about these boundaries before surgery is one of the strongest predictors of satisfaction afterwards.
A few degrees is the whole operation. Over-rotation can make the nose look upturned, short, artificial or “piggy.” In drooping tip correction, too much lift is not refinement — it is a new deformity. This matters especially in Indian and South-Asian faces, where natural ethnic balance is important: a tip lifted too high can expose too much nostril, shorten the nose, disturb facial harmony and make rhinoplasty obvious. The safest aesthetic direction is controlled rotation with structural support, not aggressive lifting.
A lifted tip on a nose with a hump, or under heavy skin, can look mismatched or barely changed. Some patients need complementary planning — hump reduction, tip refinement or conservative soft-tissue management — to get the profile they are picturing. The result is better described as long-lasting than permanent: structural grafting gives durable support, but ageing, healing, scar contracture and tissue behaviour can still change the nose gradually. Results vary by individual anatomy and healing.
Possible problems from over-rotation
- Upturned appearance: nose looks operated.
- Excess nostril show: tip appears too high.
- Short-nose look: facial balance changes.
- Airflow concern: valve narrowing may occur.
- Stiff tip: over-built support can feel rigid on smiling.
- Revision complexity: scar and cartilage shortage make correction harder.
- Loss of identity: ethnic profile reduced.
Sources: Aesthetic Surgery Journal – Tip Rotation · PMC3321146 · Plastic and Aesthetic Research
Why Consult Before Drooping Tip Correction?
A drooping tip consultation is a diagnostic appointment, not a sales appointment. Its purpose is to decide whether the droop is static, dynamic or mixed; what is causing it — support, septum, skin, muscle, previous surgery; how many degrees of rotation the face needs; and whether the tip should be treated alone or with the rest of the nose.
What happens during a drooping tip consultation?
Assessment typically covers the profile at rest, then while smiling and speaking, to separate static from dynamic droop; measurement of the nasolabial angle; a tip-recoil test (pressing the tip and watching it spring back) to judge support; palpation of the caudal septum and anterior nasal spine; tip cartilage length and strength; skin thickness and weight; the upper lip — length, and whether it shortens on smiling; the bridge, to decide whether a hump or length also needs treatment; an internal examination of the septum and valves, with a breathing history; documented asymmetry; full medical history including medicines, supplements and nicotine use; previous nasal surgery, fillers or injectables; and your goals in your own words. You should leave understanding your droop type, the recommended technique and how many degrees of rotation are planned, the alternatives including no treatment or a temporary injection, the realistic profile change, the risks and the recovery required.
What should I prepare before consultation?
- Your main concern — the tip at rest, the tip when smiling, or the whole nose.
- Profile photographs at rest AND smiling in even light without makeup — the smiling one is what separates dynamic from static droop.
- Older photographs from 5–10 years ago if you feel the tip has dropped with age.
- All medicines and supplements, including blood thinners and herbal products.
- Medical and surgical history, including anaesthetic problems and breathing issues.
- Previous nasal treatments — rhinoplasty, fillers, threads, botulinum toxin — with approximate dates.
- Reference photographs, useful for discussing goals — not as a target to replicate; note that most “ideal” online profiles are over-rotated.
Is an online drooping tip consultation possible?
If you are outside Mumbai, you can request a preliminary WhatsApp photo pre-check with profile photographs at rest and smiling, plus front and basal views, in even, natural lighting, without makeup or filters. This is preliminary guidance only. Photographs cannot assess tip support, septal length, muscle activity, airway function or medical fitness, and no definitive diagnosis, technique recommendation or final quotation can be given from them.
Consultation fee: ₹1,500
Link: How to prepare
Which Techniques Are Used in Drooping Tip Correction?
“Technique” in drooping tip correction refers to how the tip is rotated and then held — grafts that support it, sutures that fix it to the septum, shortening of a long septum, adjustment of the tip cartilages, and release of the smile muscle in dynamic droop — and whether the tip is reached through an open or closed approach. These are surgical decisions made from your anatomy and droop type, not a menu.
| Technique | Purpose | Used for | Key caution |
|---|---|---|---|
| Columellar strut graft | Supports and stabilises the tip | Mild to moderate weak support | Must avoid excessive projection |
| Septal extension graft | Strong control of rotation / projection | More significant droop or weak tip | Avoid stiffness or over-rotation |
| Tongue-in-groove | Sets medial crura against caudal septum | Controlled tip rotation | Requires precise planning |
| Caudal septal shortening | Reduces downward septal push | Long caudal septum | Must protect support |
| Lateral crural work (cephalic trim, overlay, repositioning) | Refines lower lateral cartilage support and rotation | Tip malposition or heavy tip | Avoid over-resection |
| Depressor septi treatment (release / transposition) | Reduces smile-related downward pull | Dynamic droop | Must diagnose correctly |
| Botulinum toxin to depressor septi | Temporary reduction of dynamic pull | Purely dynamic droop; trial before surgery | Temporary; no effect on static droop |
| Open approach | Direct visualisation | Complex tip correction, grafting | Small columellar scar |
| Closed approach | Endonasal access | Selected cases | Limited exposure in complex cases |
Support first: A strut placed between the medial crura, or an extension graft fixed to the front of the septum, gives the tip a stable central pillar. The tip cartilages are then sutured to that pillar at the planned angle — so rotation is set once and held, rather than relying on tension that relaxes as healing progresses.
Shortening what pushes down: Where the caudal septum is long, a measured strip is removed from its front edge so it no longer pushes the tip down or hides the lip. In tongue-in-groove, the medial crura are then set into a pocket on the shortened septum — an elegant way to rotate and support in one move.
Adjusting the tip cartilages: Long lateral crura resist rotation; conservative trimming, overlapping or repositioning lets the tip turn up naturally. Over-resection is the classic cause of pinching and later drooping, so a generous rim of cartilage is always preserved.
Dealing with the smile muscle: In dynamic droop the depressor septi is released or repositioned through the same incisions, so smiling no longer drags the tip down. In purely dynamic cases a botulinum toxin injection can preview the effect for a few months before deciding on surgery.
Is open rhinoplasty always better than closed for a drooping tip?
No. Neither approach is universally superior — but drooping tips are more often open cases than most, because precise graft fixation and rotation setting are easier under direct vision.
- Anatomy matters most. Septal extension grafts, tongue-in-groove fixation and depressor septi work are best done open; a mild droop needing only a strut and a small septal trim can sometimes be done closed.
- Surgeon experience matters. A technique performed well within a surgeon’s established expertise generally serves a patient better than an unfamiliar one chosen for its label.
- Symmetry and angle matter. Setting rotation to a precise angle and checking both sides is most reliable open.
- Scar is minor either way. The open columellar scar is a few millimetres and usually fades to near-invisible; it should not be the deciding factor.
The right question at consultation is not “do you do closed?” but “which approach does my tip need, and why?”
Links: Open technique · Closed technique · Tip plasty techniques
Sources:
PubMed 38595160 · PMC8076873 · PubMed 26862961 · PMC5584101 · PubMed 23698211 · PubMed 33868871
“Drooping tip correction is not just tip lifting. The tip needs controlled rotation, proper support, and balance with the bridge, nostrils, upper lip, and face. My aim is a stable, lighter-looking nasal tip that appears natural — not over-lifted or operated.”
What Are the Types of Drooping Tip Correction?
Where technique describes how the tip is rotated and held, type describes the scope — which droop is being treated, and whether the tip is treated alone or with the rest of the nose.
- Static droop correction — for a tip that sits low at rest. Structural support (strut or septal extension) with the tip sutured at the planned angle; caudal septum shortened if long. The core operation.
- Dynamic (smile-related) droop correction — for a tip that drops only when smiling. Depressor septi release or transposition, alone or with light support. Botulinum toxin is the temporary non-surgical alternative.
- Mixed droop correction — for a tip that is low at rest and worse when smiling. Structural support plus muscle release in one operation. The most comprehensive stand-alone option.
- Age-related tip descent correction — for a tip that has dropped over the years as support weakened. Support-heavy planning, often with conservative lateral crural work.
- Droopy and bulbous tip correction — for a tip that is both low and round. Rotation support combined with dome refinement. → Bulbous tip correction
- Tip lift with full rhinoplasty — when a hump, length or bend also needs correction; the tip is rotated as part of a whole-nose plan. → Rhinoplasty Surgery · Reduction Rhinoplasty
- Revision drooping tip correction — for a tip that dropped or was never adequately supported after earlier surgery. Missing cartilage is rebuilt with ear or rib grafts; technically more demanding. → Revision Rhinoplasty
Combined planning: add hump reduction, tip refinement or nostril work only when it solves a separate anatomical concern — a lifted tip beneath an untouched hump can look mismatched, so the whole profile is assessed even when only the tip is treated.
Non-surgical options: botulinum toxin into the depressor septi can temporarily reduce a purely dynamic droop; filler at the base of the columella can visually open the nasolabial angle by a degree or two for 12–18 months. Neither corrects structural droop, and nasal filler carries vascular risk. → Non-Surgical Rhinoplasty
How is a drooping tip different from a bulbous tip or a long nose?
A drooping tip is a position and rotation problem, a bulbous tip is a shape and definition problem, and a long nose is a length problem. They can overlap, but they should not be treated as the same diagnosis.
| Concern | Main problem | Patient usually says | Owned by |
|---|---|---|---|
| Drooping tip / tip ptosis | Tip sits low or under-rotated | “My tip hangs down.” | This page |
| Smile-related droop | Tip drops during smiling | “My tip falls when I smile.” | This page |
| Bulbous tip | Tip is round, broad or boxy | “My tip is fat or wide.” | Bulbous tip correction |
| Long nose | Nose length is excessive | “My nose looks too long.” | Reduction rhinoplasty |
| Combined concern | Tip is long, droopy and bulky | “The whole lower nose looks heavy.” | Consultation-based plan |
Sources: Aesthetic Surgery Journal – Nasal Tip Ptosis · PMC3321146 · Plastic and Aesthetic Research
How Is Drooping Tip Correction Performed Step-by-Step?
Drooping tip correction builds the support first, sets the rotation second and holds it third — so the tip is never lifted without something to rest on. Incisions sit inside the nostrils (closed) or inside the nostrils plus a small cut across the columella (open).
| Step | What happens |
|---|---|
| 1. Consultation and planning | Droop type diagnosed (static / dynamic / mixed); cause identified; target rotation in degrees decided; support technique, graft source and approach chosen; alternatives, risks and recovery discussed |
| 2. Preoperative preparation | Medical assessment, investigations, anaesthetic review, medication and supplement adjustment, confirmed nicotine cessation, standard photographs at rest and smiling |
| 3. Surgical markings | Nasolabial angle, planned tip position, columellar incision and existing asymmetry marked with the patient upright |
| 4. Anaesthesia | General anaesthesia (local with sedation for selected limited cases); local anaesthetic with adrenaline to limit bleeding. Monitoring is continuous |
| 5. Incision and exposure | Closed or open approach; skin and soft tissue lifted off the tip cartilages and caudal septum in the correct plane |
| 6. Caudal septal adjustment | Long caudal septum shortened by a measured strip; septal cartilage harvested for grafts |
| 7. Depressor septi release (dynamic / mixed droop) | Muscle released or transposed at the base of the columella so smiling no longer pulls the tip down |
| 8. Support | Columellar strut placed between the medial crura, or septal extension graft fixed to the caudal septum, to create a stable central pillar |
| 9. Setting rotation | Tip cartilages sutured to the pillar at the planned angle (or set tongue-in-groove on the septum); angle checked against the plan from the side |
| 10. Lateral crural adjustment | Conservative trim, overlap or repositioning of the lateral crura so they follow the new rotation without resisting it |
| 11. Refinement | Dome sutures or a small tip graft if the tip is also round; symmetry checked side by side |
| 12. Closure, taping and observation | Incisions closed with fine sutures; tip taped (and splinted if bone work was combined); monitored recovery, day-care or overnight |
Surgical elements and devices
| Element / device | Possible role | Important consideration |
|---|---|---|
| Septal cartilage | Columellar strut, septal extension graft | Preferred graft; may be scarce in revision |
| Ear (conchal) cartilage | Strut or extension when septum unavailable | Additional donor site; naturally curved — often layered |
| Rib (costal) cartilage | Strong extension grafts in revision | Warping risk; rarely needed for primary droop |
| Permanent fine sutures (PDS / nylon) | Fix tip to pillar at set angle; dome shaping | Placement decides rotation; must not over-tighten |
| Absorbable sutures | Soft-tissue and skin closure; muscle repositioning | Columellar skin sutures removed at about a week |
| Tapes and (if combined) external splint | Hold tip position, control supratip swelling | Night taping may continue for weeks in thick skin |
| Botulinum toxin (pre-op trial or adjunct) | Temporary depressor septi relaxation | Optional; effect 3–4 months |
Sources: PubMed 38595160 · PMC8076873 · PMC5584101
When Will I See Final Drooping Tip Correction Results?
The new tip position is visible when tapes come off at about a week — and in the first weeks it usually looks slightly higher than the final result, because swelling lifts the tip and the tissues have not yet settled onto the new support. The tip settles down a degree or two over 3–6 months as swelling resolves, and final rotation is judged at 6–12 months, later in thick skin.
| Time | What you may notice |
|---|---|
| First few days | Tip swollen, numb and firm; tapes on. Tip looks higher than planned — this is swelling, not the result |
| 1 week | Tapes and columellar sutures removed. New position visible; tip still full and slightly over-rotated |
| 2–4 weeks | Presentable in public. Smiling feels tight if the depressor septi was released; upper lip may feel stiff — settles |
| 6–8 weeks | Tip begins to settle onto its support; smile returns to normal |
| 3–6 months | Rotation eases to near its final angle; tip softens; definition emerges |
| 6–12 months | Final tip position and refinement in most patients |
| 12–18 months | Final result in thick-skinned, grafted and revision tips. Revision, if ever considered, waits until here |
What can affect the final result?
Droop type and how completely its cause was addressed; strength and fixation of the support graft; skin thickness and weight; cartilage memory and healing contracture; whether the depressor septi was released; previous nasal surgery; smoking and nicotine exposure; individual healing; adherence to taping and follow-up; and continued ageing.
Sources: PubMed 17398339 · Cleveland Clinic – Rhinoplasty · SAGE Journals – Nasal Tip Rotation
What Is the Aftercare After Drooping Tip Correction?
Aftercare after a tip lift centres on protecting the newly set rotation — no pressure on the tip, no pulling on the upper lip, taping as instructed — plus head elevation, no nicotine and patience while the tip settles. These are general principles — your written personal instructions always take priority.
What care is usually advised?
- Keep your head elevated on two pillows for the first week or as instructed.
- Protect the tapes — keep them dry; do not press, adjust or remove them. Night taping may continue for several weeks.
- Do not push, lift or “test” the tip — the sutures holding rotation need weeks to be reinforced by scar.
- Avoid wide smiling, laughing and exaggerated lip movement for the first 1–2 weeks, especially after depressor septi release.
- Do not blow your nose for the period advised; sneeze with the mouth open.
- Use saline spray and ointment inside the nostrils as shown.
- Take medicines exactly as prescribed and do not restart blood-thinning medicines or supplements without approval.
- Attend all follow-up appointments — tape and suture removal, rotation check, and profile photographs at intervals.
What should patients avoid after drooping tip correction?
| Avoid | Why |
|---|---|
| Smoking, vaping, nicotine in any form | Reduces blood supply to the tip and grafts; increases healing problems and graft failure |
| Glasses resting on the nose (4–6 weeks, or as advised) | Pressure on the bridge and tip during settling |
| Pressing the tip down or pulling the upper lip (including lip-stretching skincare) | Direct strain on the sutures that set rotation |
| Sleeping on your face or side | Pressure can push the tip asymmetric or down |
| Strenuous exercise and heavy lifting (2–4 weeks) | Raises blood pressure and swelling |
| Wind instruments, shouting, forceful facial exercise (4 weeks) | Repeated pull on the lip and tip base |
| Swimming, steam, sauna | Heat and moisture increase tip swelling |
| Direct sun on the nose | Worsens swelling and can darken the columellar scar |
| Nasal filler or botulinum toxin near the tip (12 months, unless planned by your surgeon) | Interferes with settling; vascular risk |
| Judging your rotation in the first months | Early over-rotation from swelling is normal and settles |
Full aftercare detail: Rhinoplasty recovery timeline
What Are the Risks and Complications of Drooping Tip Correction?
Drooping tip correction is generally safe for an appropriately selected patient operated on by a trained plastic surgeon in an equipped facility, but it is cartilage and support surgery on the most expressive part of the nose, with recognised risks. Expected postoperative effects must be separated from true complications — and no surgeon can eliminate risk.
Common / expected early effects (normal healing, not complications): tip swelling and firmness lasting months; a tip that looks slightly over-rotated early; numbness of the tip and columella; stiffness of the upper lip on smiling after depressor septi release; a blocked feeling; mild aching; temporary asymmetry.
Uncommon complications: bleeding; infection; asymmetry after healing; under-correction (tip still low); over-correction (tip too lifted); altered projection (tip pushed too far forward by the graft); a stiff, unnatural-feeling tip; visible or palpable graft or strut; suture visibility or extrusion; prolonged swelling in thick skin; dissatisfaction leading to a revision request.
Rare but important: loss of support with recurrent droop; graft shift or warping; external valve narrowing with breathing change; columellar retraction or a hanging columella; persistent upper-lip stiffness or altered smile; septal perforation after septal work; skin compromise, most strongly associated with nicotine; anaesthesia-related complications.
How risk is minimised
| Risk area | How we work to minimise it |
|---|---|
| Wrong droop type treated | Static vs dynamic vs mixed diagnosed at consultation from rest and smiling views; muscle released only when it is the cause |
| Over-rotation / “piggy” look | Rotation planned in degrees for the face and ethnicity; set conservatively, knowing early swelling exaggerates lift |
| Recurrent droop | Structural support (strut / extension graft) always placed; tip fixed to support rather than held by tension |
| Stiff or over-projected tip | Graft sized to the nose; extension grafts trimmed so the tip moves naturally on smiling |
| Asymmetry | Open approach for complex cases; angle and both sides checked before closure |
| Valve narrowing | Lateral crura preserved; support grafts protect the external valve |
| Undetected medical or airway risk | Preoperative medical evaluation, airway examination and anaesthetic review before scheduling |
| Nicotine-related healing failure | A clear, enforced nicotine cessation requirement before and after surgery |
| Bleeding | Medication and supplement review, blood-pressure control, meticulous haemostasis |
| Infection | Sterile technique, theatre sterilisation protocols, perioperative antibiotics, wound-care instruction |
| Facility and equipment risk | Surgery at an NABH-accredited surgical centre with appropriate equipment |
| Delayed recognition of a problem | Structured postoperative observation, written warning signs, accessible follow-up |
⚠️ When to seek urgent medical attention
Seek urgent advice or immediate emergency care for: rapidly increasing swelling · severe pain · fever · pus-like discharge · wound opening · spreading redness · new or worsening nasal obstruction · dusky or pale skin at the tip or columella · chest pain or breathlessness.
In an emergency, go to the nearest emergency department or call emergency services. Do not wait for a WhatsApp or email reply.
Full risk guide: Rhinoplasty Risks & Safety
Sources: Cleveland Clinic – Rhinoplasty · PubMed 17398339
What Is the Drooping Tip Correction Recovery Timeline?
Recovery after drooping tip correction is short in downtime and gradual in settling. Bruising is minimal when no bone work is done; tapes and columellar sutures come off at about a week; most patients return to desk work within 7–10 days. The tip then settles onto its new support over months — early tip position may look slightly high or swollen, while the final rotation is judged at 6–12 months, later in thick skin. This is a summary — for detailed day-by-day guidance, see the rhinoplasty recovery timeline.
| Timepoint | What typically happens |
|---|---|
| First 24–48 hours | Tapes on the tip; swelling, numbness, blocked nose, mild aching and upper-lip tightness expected. Little bruising if no osteotomies. Rest head-elevated; day-care discharge or overnight observation |
| Days 3–7 | Swelling starts reducing. Saline spray and ointment routine. Tapes and columellar sutures removed at the first follow-up around day 7 |
| Weeks 2–3 | Presentable in public; many patients return to desk work. Tip looks slightly higher than planned; smile still a little stiff after muscle release |
| Weeks 4–6 | Exercise, glasses and travel usually cleared at review. Smile normalises; tip begins to settle |
| 3–6 months | Rotation eases to near-final; tip softens and definition emerges |
| 6–12 months | Final position in most patients; profile stable |
| 12–18 months | Final result in thick-skinned, grafted and revision tips. Revision assessment waits until here |
Key recovery points: downtime is about a week; settling is months · the tip will look slightly over-lifted at first — this is planned for and settles · upper-lip stiffness after depressor septi release is temporary · glasses stay off the nose for 4–6 weeks · flying requires written clearance at follow-up — do not book non-refundable travel around an assumed date · outstation patients usually stay in Mumbai until tapes and sutures are removed.
Do not use another patient’s timeline as permission for glasses, exercise, travel or restarting medication.
“In the first two weeks after a tip lift, almost every patient sends me a photograph asking if the tip is too high. It is not — it is swollen upward. I set the rotation knowing the tip will settle a degree or two as the swelling leaves. By month three the profile is where we planned it, and by month six they have forgotten the worry.”
Links: Recovery timeline day 1 to final result ·
Outstation patients
Medical Codes for Drooping Tip Correction
Codes below are for administrative and documentation reference. All codes must be verified against the current CPT and ICD-10 code sets before publication and before any use in documentation.
| CPT Code | CPT Description | ICD-10 |
|---|---|---|
| 30400 | Rhinoplasty, primary; lateral and alar cartilages and/or elevation of nasal tip (focused tip lift) | Z41.1 (cosmetic) · M95.0 (acquired deformity of nose) |
| 30410 | Rhinoplasty, primary; complete, external parts including bony pyramid, lateral and alar cartilages, and/or elevation of nasal tip (tip lift with full rhinoplasty) | Z41.1 · M95.0 |
| 30420 | Rhinoplasty, primary; including major septal repair (with caudal septal reconstruction / septoplasty) | J34.2 · M95.0 |
| 30430 / 30450 | Rhinoplasty, secondary; minor / major revision (nasal tip work) | Z41.1 · Z98.890 |
| 30465 | Repair of nasal vestibular stenosis (when valve support is the indication) | J34.89 |
| 21235 | Graft; ear cartilage, autogenous, to nose or ear | — |
| 20912 | Cartilage graft; nasal septum (harvest for strut / extension graft) | — |
| 64612 (if applicable) | Chemodenervation of muscle(s) innervated by facial nerve (botulinum toxin to depressor septi — cosmetic use typically self-pay) | Z41.1 |
(FAQs) Frequently Asked Questions About Drooping Tip Correction
Q1. Can drooping tip correction fail or need revision?
Ans. Yes. Under-correction (tip still low), recurrent droop from inadequate support, over-rotation, asymmetry or a stiff tip can occur. Under-correction is easier to revise than over-rotation, which needs cartilage grafts to lengthen the nose again. Revision is assessed only after 12 months of settling.
Q2. Is drooping tip correction safe in India?
Ans. It is generally safe for an appropriately selected patient when performed by a qualified plastic surgeon in an accredited facility with proper anaesthetic support. Recognised risks remain — asymmetry, over- or under-rotation, breathing change. Judge the surgeon’s qualification, rhinoplasty volume and structural-grafting experience, not the country.
Q3. How long does drooping tip correction surgery take?
Ans. Focused tip surgery usually takes 1.5–2.5 hours; with full rhinoplasty, 2–3 hours or more. Grafting and revision take longer. The planned duration is confirmed only after examination and surgical planning.
Q4. Which surgery is used for a droopy nose tip?
Ans. Common techniques include a columellar strut graft, septal extension graft, tongue-in-groove fixation, caudal septal adjustment, lateral crural work, and depressor septi treatment for dynamic droop. The method depends on anatomy and smile movement.
Q5. Is a drooping tip the same as a long nose?
Ans. No. A drooping tip means the tip is under-rotated or hanging; a long nose means the whole nose length is excessive. They can occur together, but the surgical priorities are different — rotation versus reduction.
Q6. Is a drooping tip the same as a bulbous tip?
Ans. No. A drooping tip is a position problem; a bulbous tip is a shape and definition problem. If the tip is both droopy and broad, the plan may combine rotation support with tip refinement.
Q7. Can drooping tip correction affect breathing?
Ans. Proper support should protect breathing, but excessive manipulation or over-rotation can affect valve function in selected cases. This is why functional assessment is important before tip correction, and why support grafts are preferred over cartilage removal.
Q8. Does thick skin affect the result?
Ans. Yes. Thick skin can make the tip look heavier, delay swelling resolution and mask fine rotation changes. Many Indian noses need stronger support and realistic counselling rather than aggressive cartilage removal.
Q9. Is the result permanent?
Ans. It is better described as long-lasting than permanent. Structural grafting provides durable support, but ageing, healing, scar contracture and tissue behaviour can still change the nose gradually over time. A well-supported tip ages far better than an unsupported one.
Q10. When can I fly after drooping tip correction?
Ans. Only after written clearance at a follow-up review, usually once tapes and sutures are off and there is no bleeding concern. Outstation patients typically stay in Mumbai for about a week. Do not book non-refundable travel around an assumed date.
Q11. Does insurance cover drooping tip correction?
Ans. Cosmetic tip rhinoplasty should not be assumed to be covered by health insurance. Coverage, where it exists at all, applies only to documented functional indications — for example valve collapse with obstruction — and must be confirmed directly with your insurer before surgery.
Related Links
- Rhinoplasty Surgery (hub)
- Rhinoplasty Cost
- Rhinoplasty Before & After Gallery
- Bulbous & Boxy Tip Correction
- Nasal Tip Plasty
- Reduction Rhinoplasty
- Nasal Hump / Dorsum Deformities
- Broad Nose Correction
- Wide Nostril Correction
- Crooked Nose Correction
- Functional Rhinoplasty
- Non-Surgical Rhinoplasty
- Nasal Deformities Treated by Rhinoplasty
- Revision Rhinoplasty
- Rhinoplasty Recovery Timeline
- How to Prepare for Rhinoplasty
- Rhinoplasty Risks & Safety

