
Wide Nostril Correction in Mumbai: Balanced, Natural Nostril Reduction That Suits Your Face

Indian Board Certified Plastic Surgeon
M.CH, MS, ISAPS Mentor
16000+ Cosmetic Surgeries
1500+ Rhinoplasty Surgeries
Wide nostril correction (alar base reduction) narrows nostrils that look too broad, flared or spread for the face by removing a few precise millimetres at the nostril base and hiding the incision in the natural crease. At Allure Medspa Mumbai, Dr. Milan Doshi first checks whether the width is real or an illusion created by a low bridge or weak tip — so the nostrils end up cleaner and better proportioned, still natural for an Indian face, never pinched.
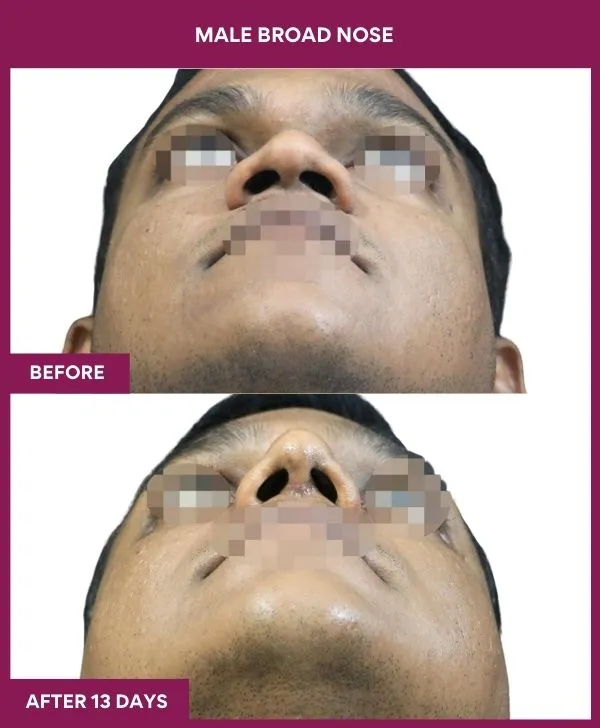
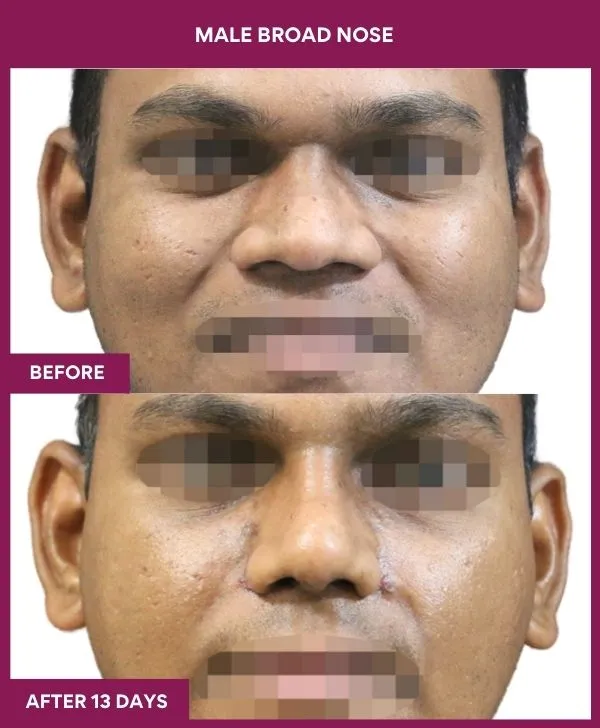
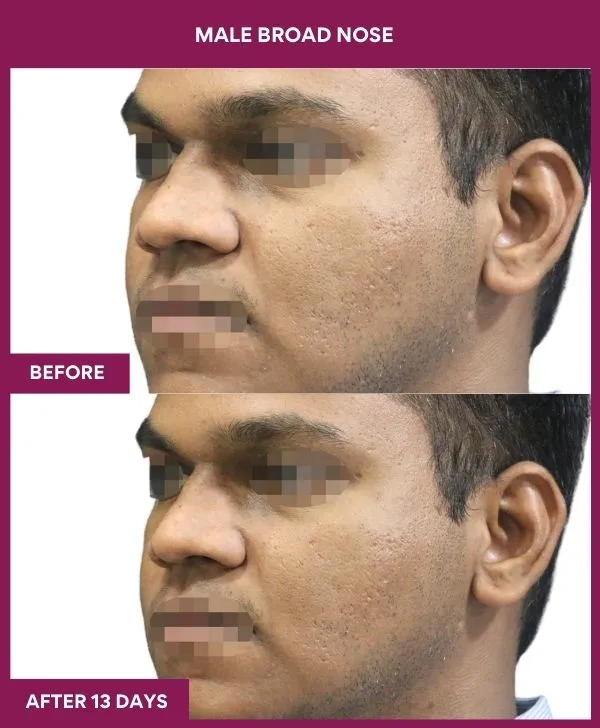
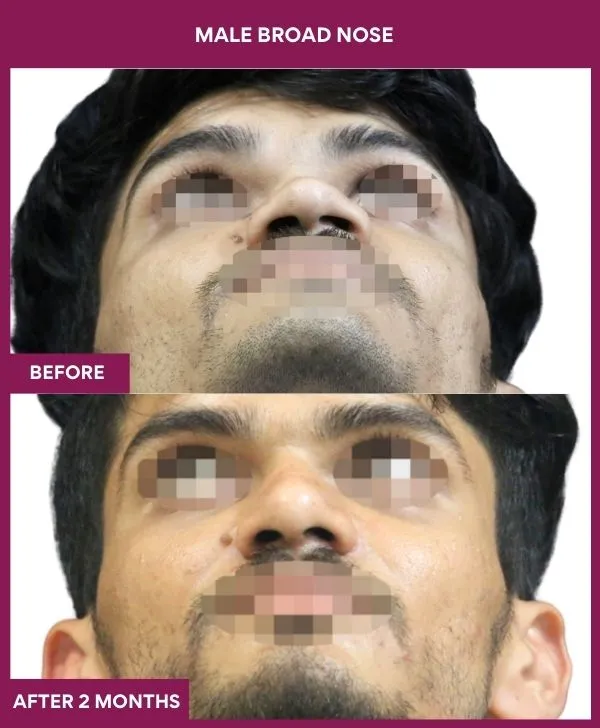
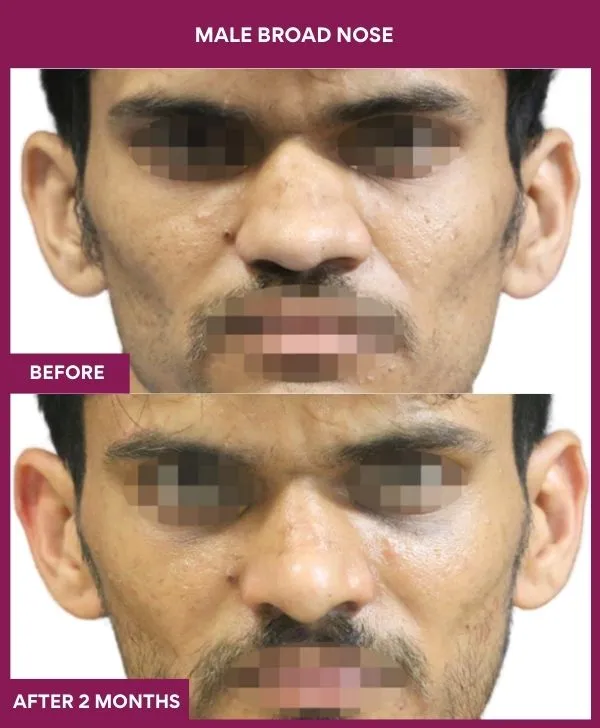
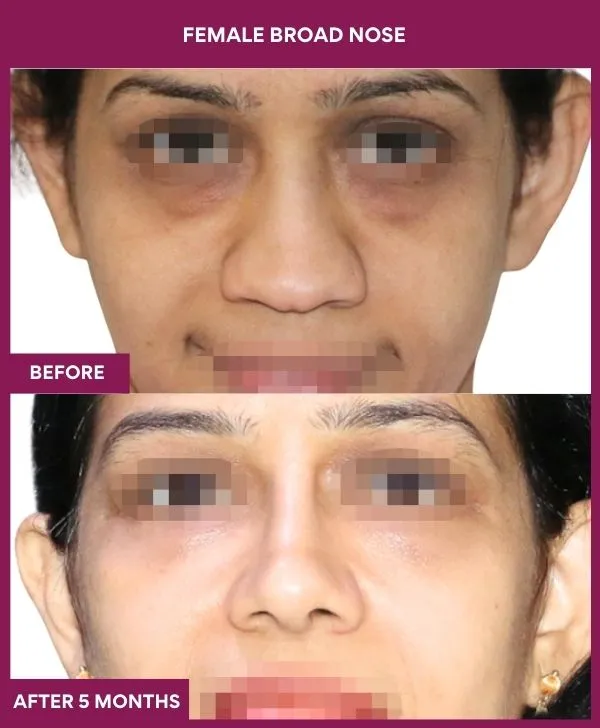
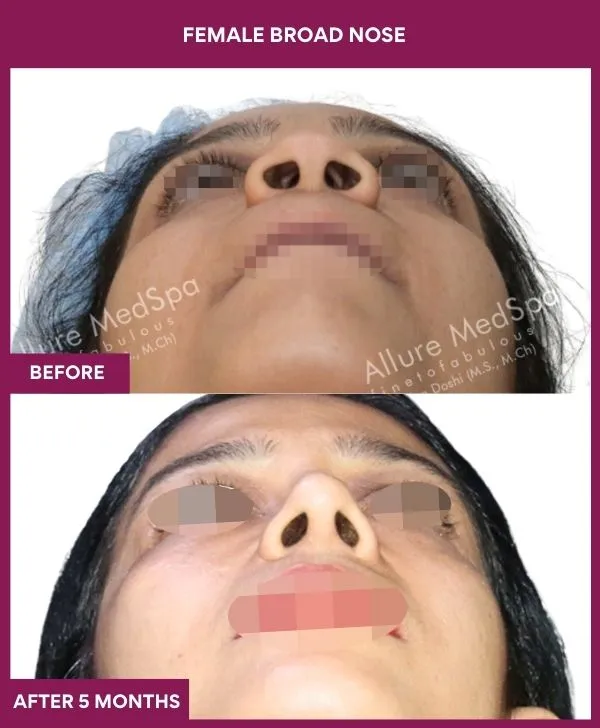
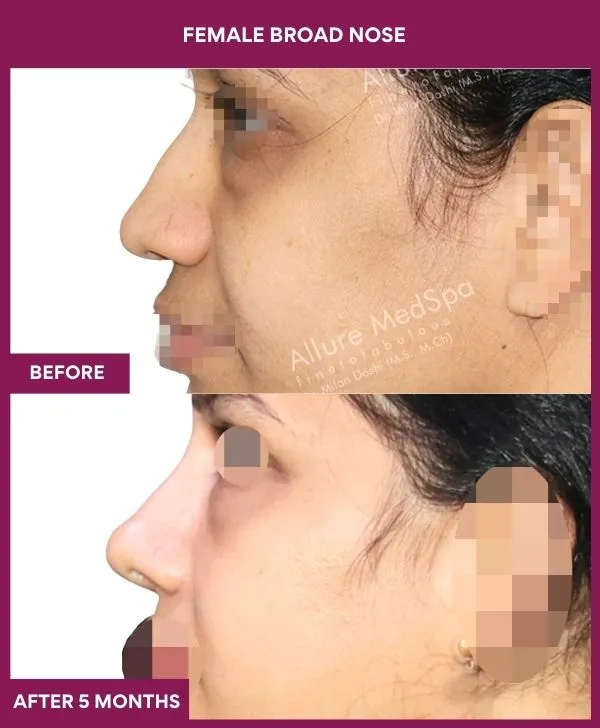
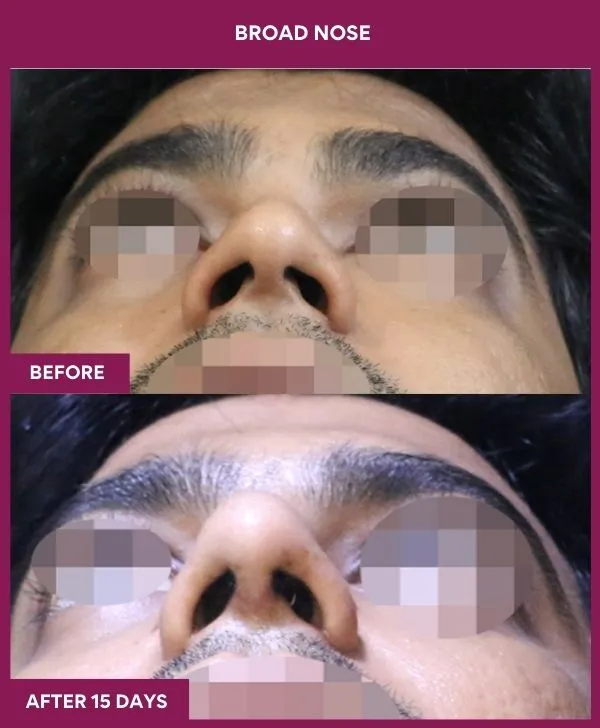
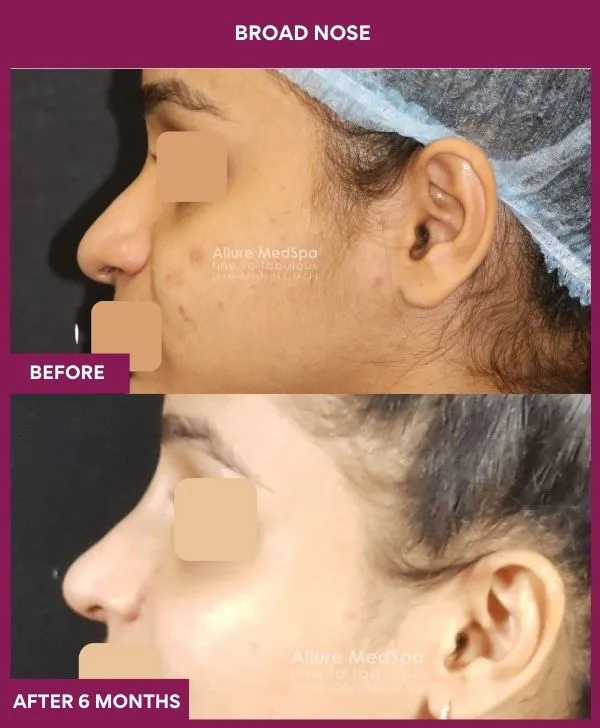
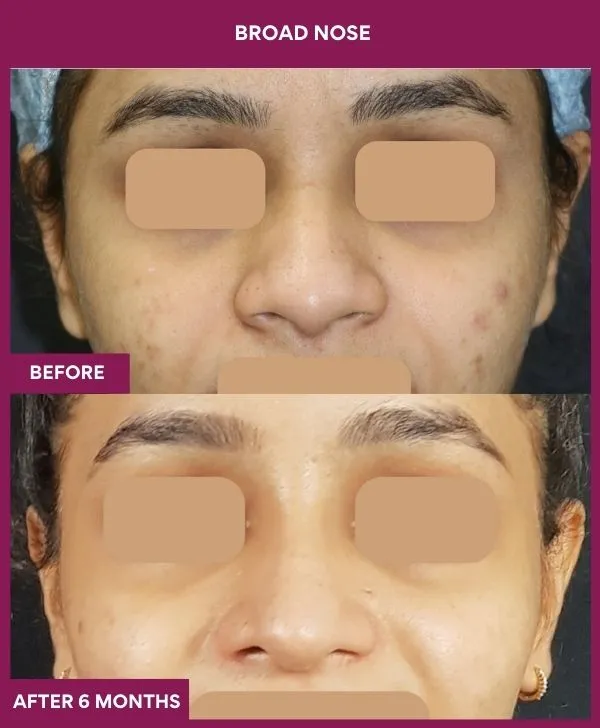
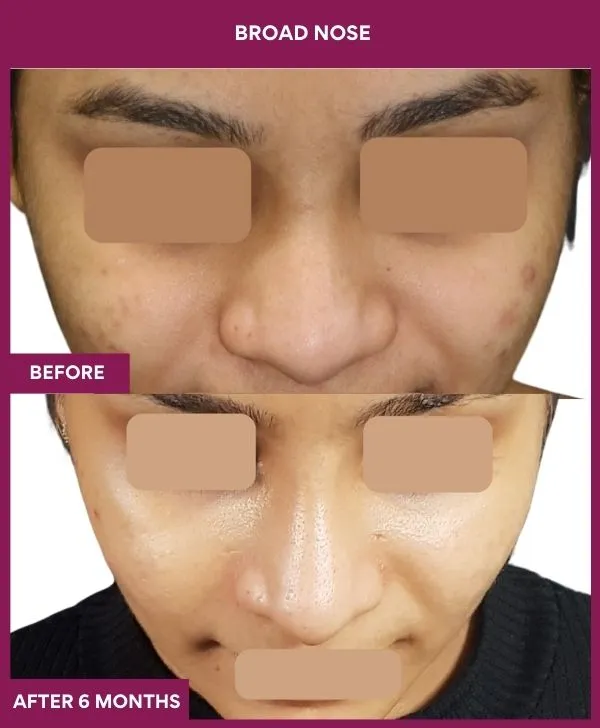
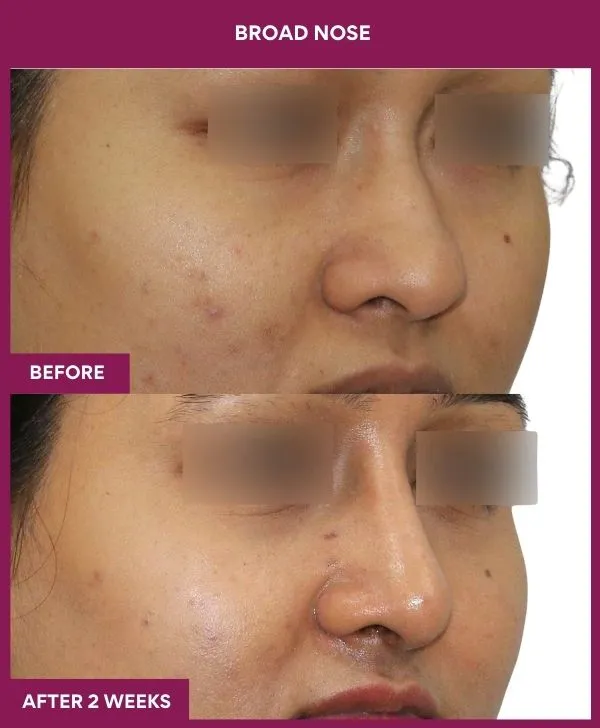
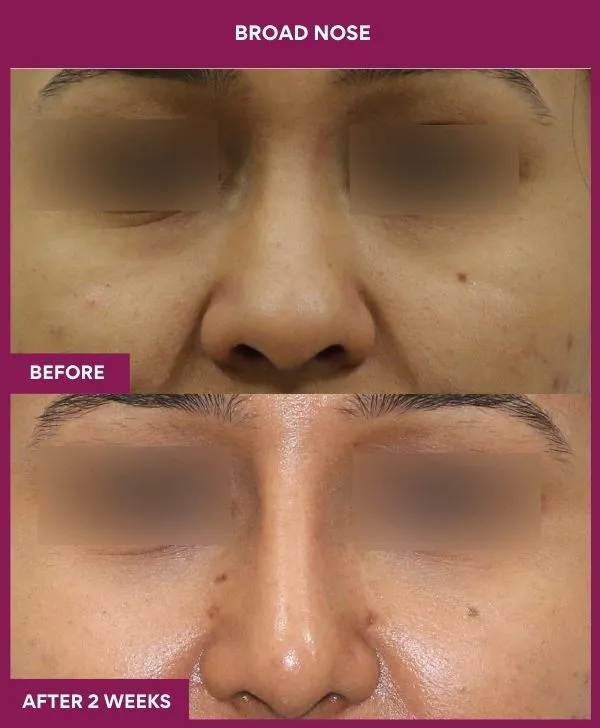
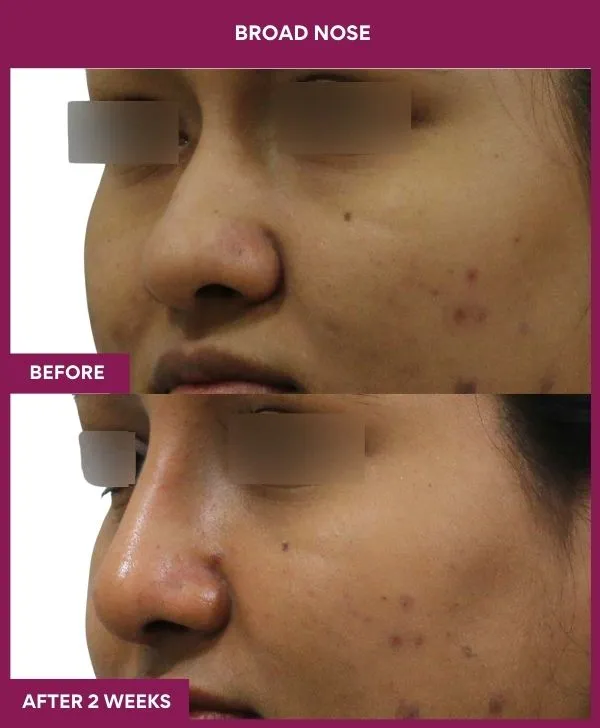
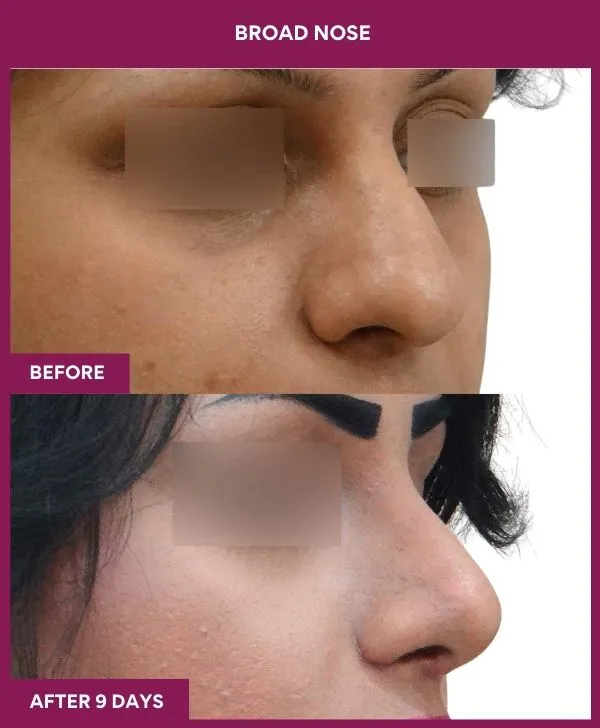
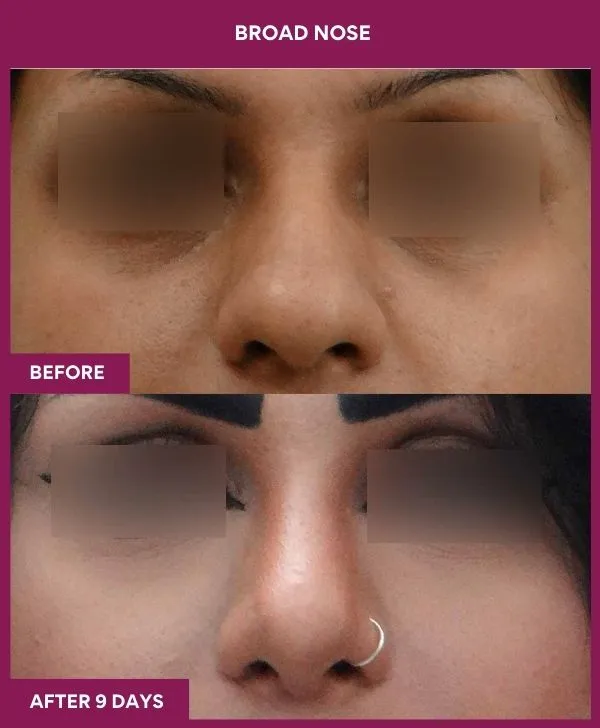
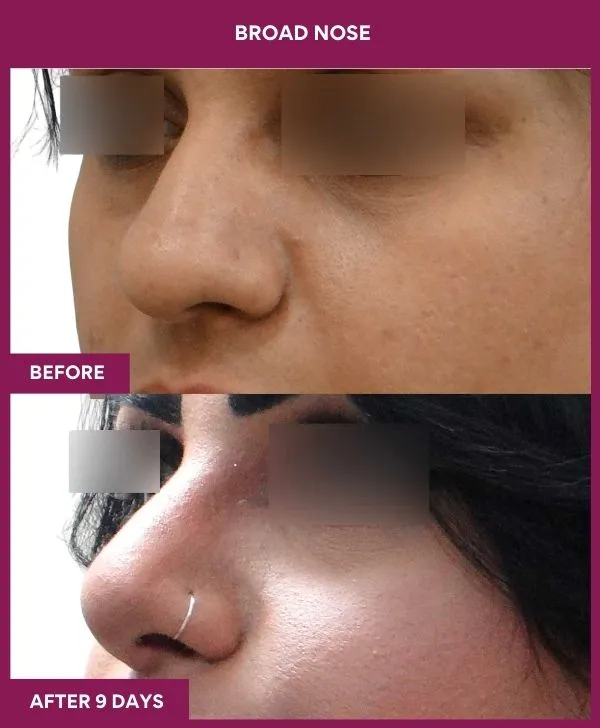
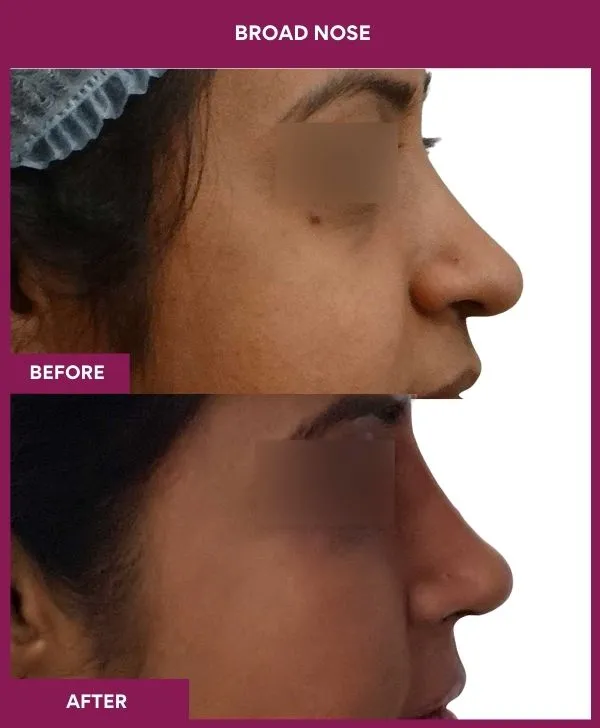
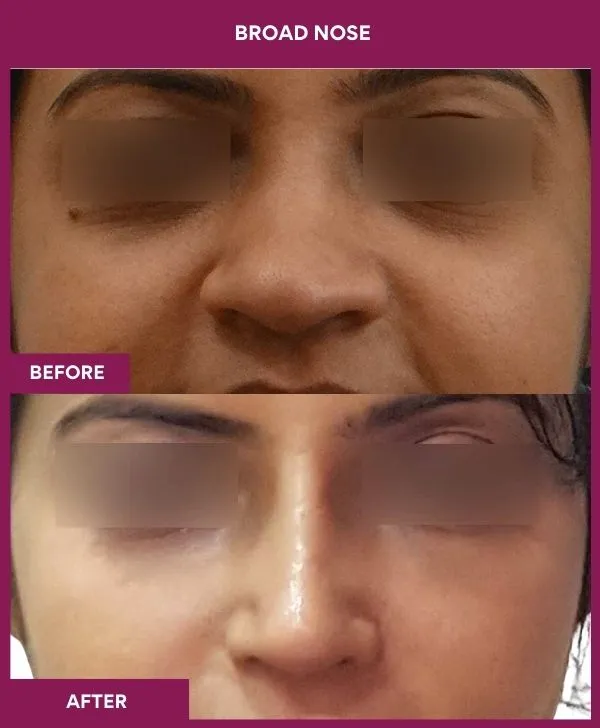
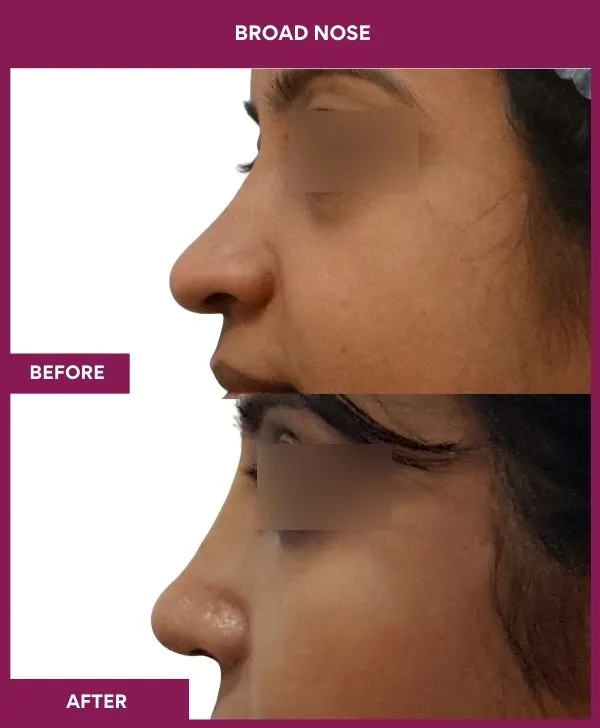
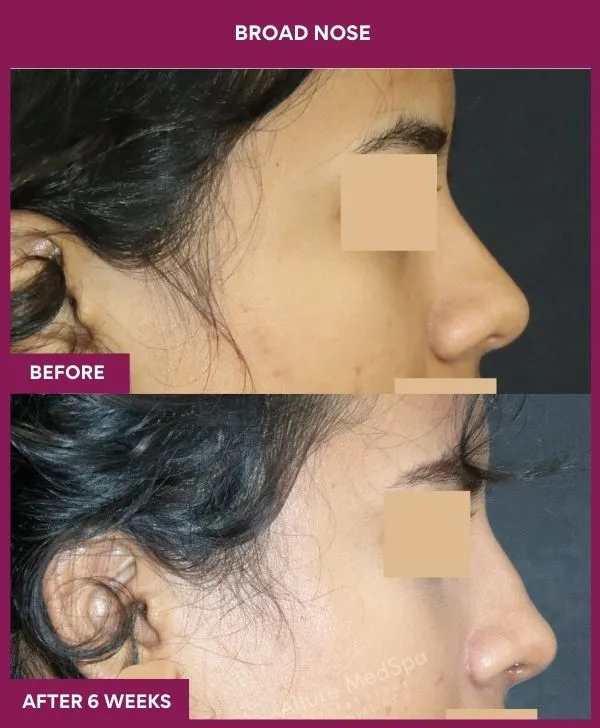
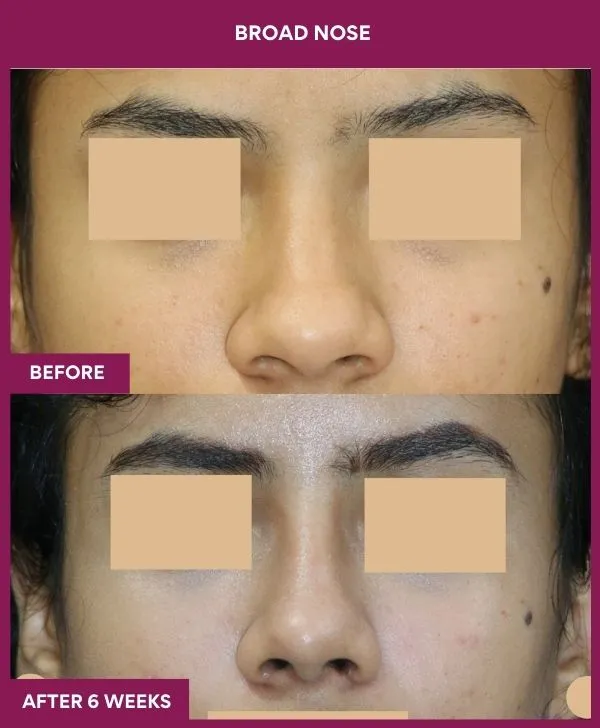
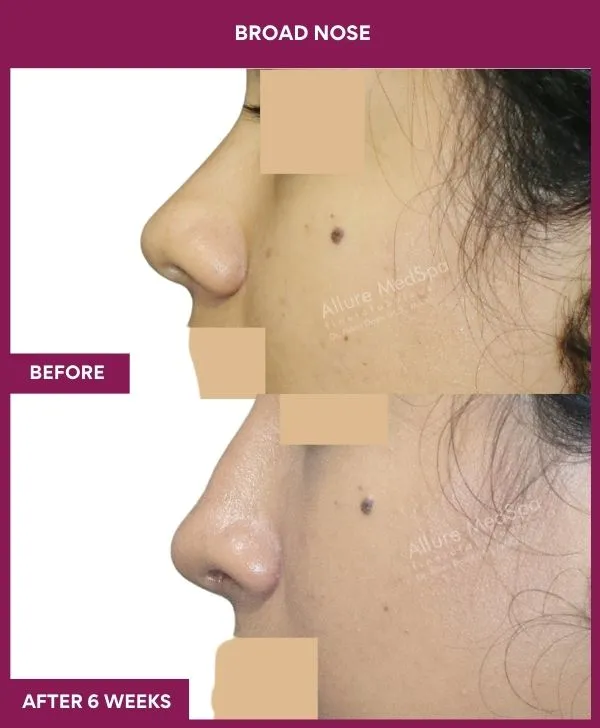
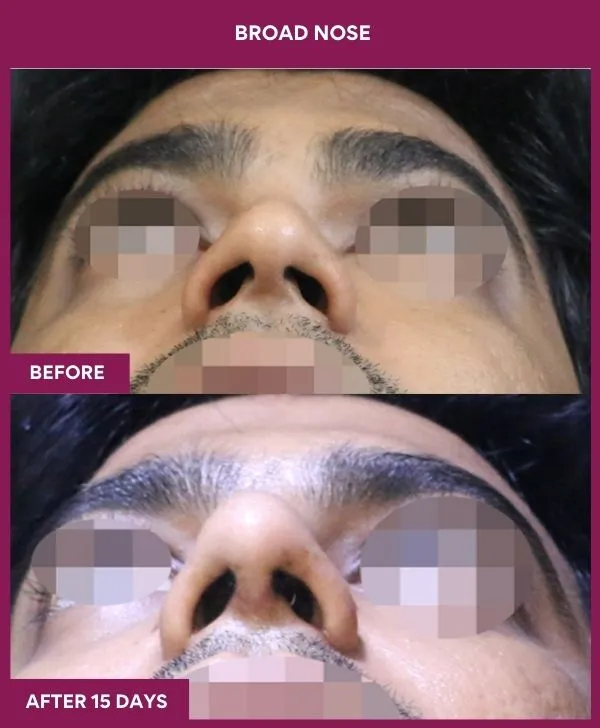
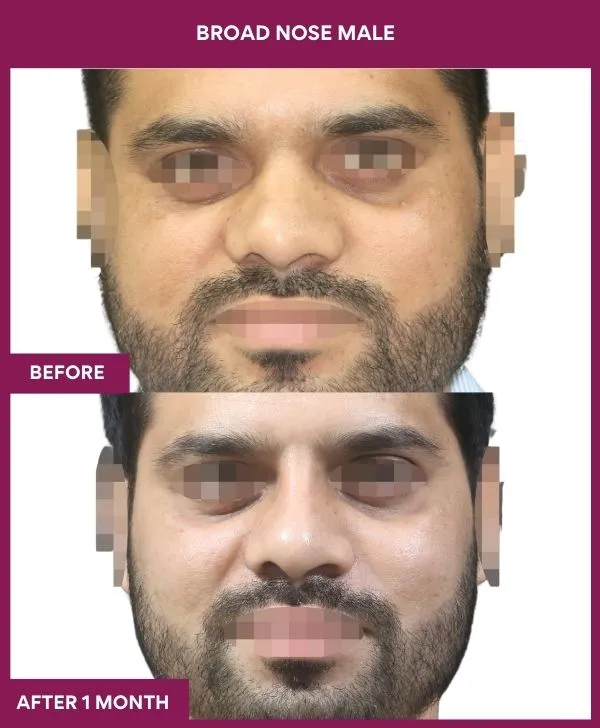
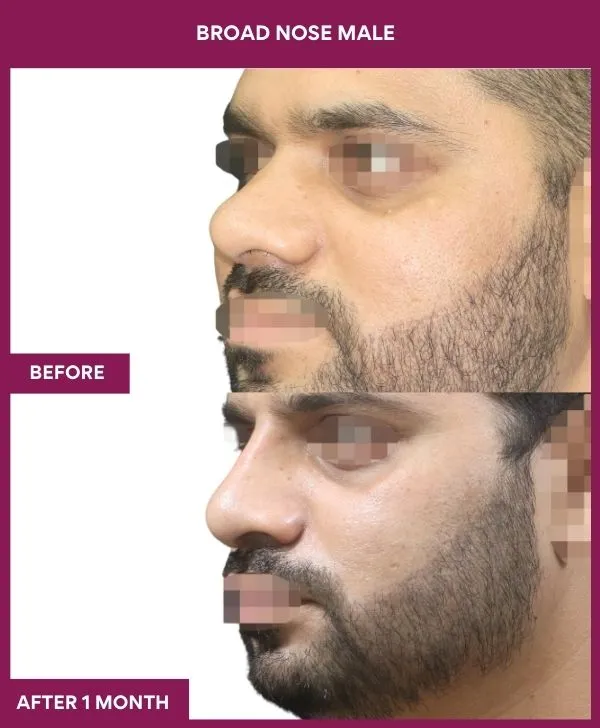
Wide nostril correction Rhinoplasty Before And After Images

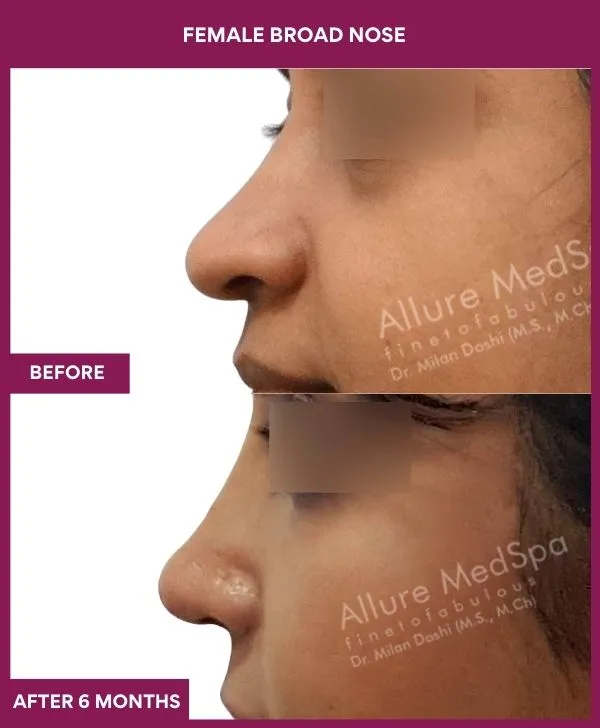

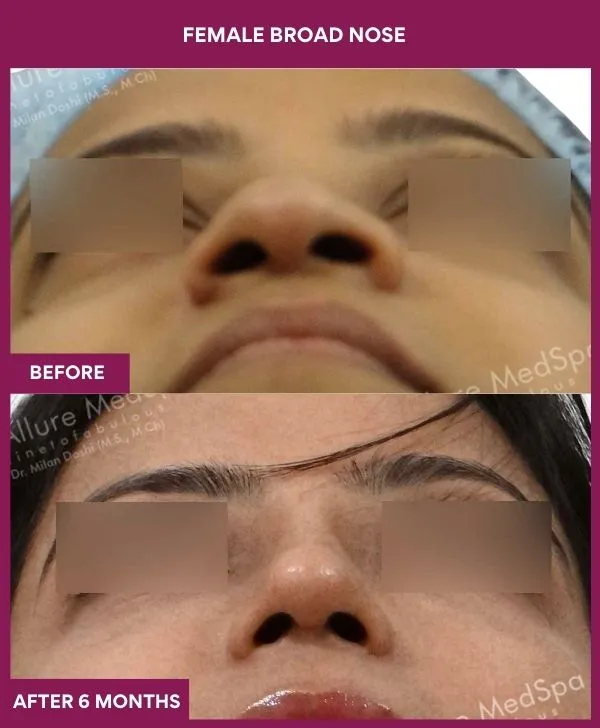
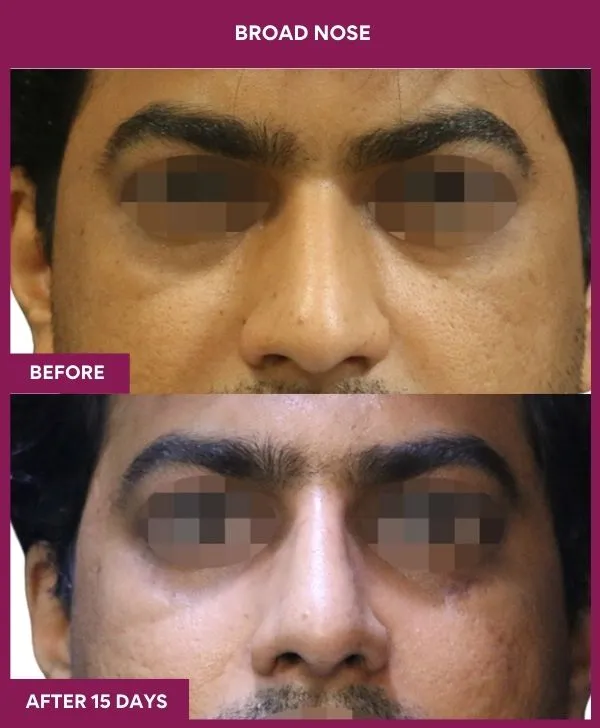
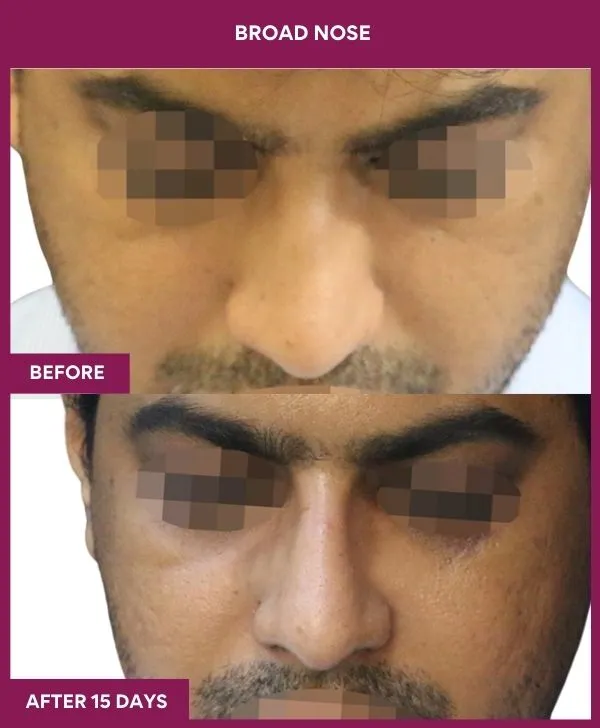
Rhinoplasty Surgery Testimonials: Celebrities Patient

Awarded by Google.com
Rating: 4.7
Reviews: 485+

Awarded by WhatClinic.com
Rating: 4.8
Reviews: 119+

Awarded by Realself
Rating: 4.9
Reviews:453+

Awarded by Facebook
Rating: 4.6
Reviews:105+
Dr Milan Doshi and his staff are very professional and committed as the centre is highly equipped with advanced technology. I had closed rhinoplasty 4 months back and I’m seeing the results as to how it becomes successful.
Deepika Shetty
The doctor explained everything clearly and the surgery was smooth. Recovery was faster than I expected and the team was very supportive.
Rahul Mehta
Very natural results and excellent staff. From consultation to follow-up, the experience was outstanding and boosted my confidence.
Sneha Kapoor
Video: Best Rhinoplasty Surgeon explain nose reshape procedure
Dr Milan Doshi is describing the Rhinoplasty Surgery in detail with benefits, techniques, recovery, result, risk and complecations
Am I a Candidate?
(4 quick questions)
Quick Facts About Wide Nostril Correction
TIME REQUIRED
2–3 hours
ANESTHESIA
General
HOSPITAL STAY
Day-care or 1 night
PAIN LEVEL
Mild–moderate
BACK TO WORK
3–5 days
RESULTS LAST
Permanent
SUCCESS RATE
97–98%
COMPLICATIONS
Under 2-3%
How Much Does Wide Nostril Correction Cost in Mumbai?
Isolated wide nostril correction (alar base reduction) in Mumbai starts from ₹70,000 to ₹1,80,000 and varies with the technique required (wedge, sill or combined), whether one or both sides need different amounts of reduction, anaesthesia choice, and whether it is a revision. When alar base reduction is combined with rhinoplasty, it is quoted as part of the full surgical plan rather than separately. A final quotation follows examination and a written surgical plan — it cannot be given accurately by phone or from photographs.
| Wide nostril correction scope | Indicative price range |
|---|---|
| Alar flare correction only (Weir / wedge excision, both sides) | ₹70,000 – ₹1,00,000 |
| Nostril sill excision only (wide base) | ₹70,000 – ₹1,00,000 |
| Combined wedge + sill excision (flare + wide base) | ₹90,000 – ₹1,40,000 |
| Alar cinch suture (selected cases) | ₹70,000 – ₹90,000 |
| Asymmetric / one-sided correction with scar revision | ₹90,000 – ₹1,50,000 |
| Revision alar base correction (notching, asymmetry from earlier surgery) | ₹1,20,000 – ₹1,80,000 |
| Alar base reduction combined with rhinoplasty | Included in rhinoplasty plan — see rhinoplasty cost guide (₹1,00,000–₹3,50,000) |
Get your exact quote & surgery plan
Share your details — our team responds within working hours with cost, EMI options and next steps.
Most Common Question People Ask
Q1. Is wide nostril correction the same as broad nose correction?
Ans. No. Wide nostril correction treats the alar base and nostril opening. Broad nose correction treats overall nasal width, including the bridge, bones and midvault. Some patients need both, but they are different surgical problems
Q2. How much does wide nostril correction cost in Mumbai?
Ans. The guide range for isolated alar base reduction is ₹70,000–₹1,80,000 plus 5% GST. If combined with rhinoplasty, it is priced within the full plan. The final quote is given only after consultation.
Q3. Will there be a visible scar?
Ans. Scars are placed in the alar-facial crease or nostril sill so they are less obvious. Scar visibility depends on skin type, pigmentation, incision design, wound tension, healing and aftercare. No scar can be promised invisible, and thick or darker skin needs extra counselling.
Q4. Can wide nostrils be made smaller?
Ans. Yes. Wide nostrils can be reduced using alar base reduction techniques such as Weir excision, sill excision or combined wedge-and-sill excision. The result depends on anatomy, surgical planning, scar behaviour and healing.
Q5. Can nostril reduction affect breathing?
Ans. Most patients do not need airway correction for nostril reduction alone, but over-narrowing can affect the external nasal valve and cause obstruction. Functional assessment and conservative planning are important before reducing the base.
Q6. How long is recovery?
Ans. Many patients return to normal daily activity within about 1–2 weeks — often 3–5 days for the stand-alone procedure. Swelling settles over weeks, and scars mature gradually. Final scar appearance may take 6–12 months.
Q7. Will it look natural?
Ans. A natural result depends on removing only what is truly excess, keeping the natural curve of the nostril, and matching the base to the bridge and tip. The aim is cleaner, more proportionate nostrils that still look like yours — not a narrowed, tight or operated base. Results vary between individuals and cannot be guaranteed.

Why Choose Dr. Milan Doshi?
Dr. Milan Doshi, MCh, MS — Indian board-certified plastic surgeon with 27+ years in aesthetic surgery and 1,500+ rhinoplasties, with alar base work planned as part of the whole nose rather than in isolation. ISAPS mentor, trusted by patients from 70+ countries. Consults at Andheri West; surgeries at the NABH-accredited surgical centre, Goregaon West
🩺 Dr Doshi Note: “Wide nostril correction is not just about making the nostrils smaller. In Indian faces, which are often softer and more rounded, over-reduction can look tight or artificial. I first assess alar flare, nostril base width, tip shape, bridge height, smile movement, scar position, and facial balance. With my rhinoplasty experience, the aim is controlled refinement — a cleaner, more balanced nostril base that suits the patient’s face and does not look operated.”
The Complete Guide About Wide Nostril Correction
What Is Wide Nostril Correction (Alar Base Reduction)?
Wide nostril correction, medically called alar base reduction or alarplasty, narrows nostrils whose width, flare or spacing looks broad for the face. It works on the alar base — the outer nostril edges (alae), the nostril floor (sill) and the fleshy sidewall (alar lobule) — by removing a small, precisely measured wedge of tissue and closing the incision in the natural crease where the nostril meets the cheek.
Patients may describe this as “big nostrils,” “flared nostrils,” “wide base,” or “nostrils spreading when smiling.” Surgically, the concern may come from the alar base, nostril sill, alar rim, alar lobule, or dynamic flare during smiling or breathing. Correction focuses on the nostril base and must distinguish true base excess from facial-proportion imbalance.
This distinction matters. A wider alar base is common in many ethnic groups, including South-Asian, East-Asian, African and Middle-Eastern noses. The aim is not to erase ethnicity — it is a more balanced nostril base that still looks natural. Reducing nostrils that only look wide because the bridge is low produces a base that is too small for the nose above it.
Where the width comes from
| Concern | What it means | How it looks | Planning direction |
|---|---|---|---|
| Wide alar base | Outer nostril edges are far apart | Base looks broad at rest | Alar base reduction may help |
| Alar flare | Alar rims spread outward | Nostrils look flared from front / base | Weir excision or flare correction |
| Wide nostril sill | Nostril floor is broad | Nostrils look horizontally wide | Sill excision may be considered |
| Large alar lobule | Side nostril tissue looks bulky | Alar sidewall appears heavy | Alar wedge planning may help |
| Dynamic flare | Flare increases with smiling / inspiration | Base spreads during movement | Functional / dynamic assessment |
| Optical width | Wide look from low bridge or weak tip | Measurement may be acceptable | Bridge / tip planning may be better |
Is wide nostril correction cosmetic or reconstructive?
| Type | Main purpose | Common example |
|---|---|---|
| Cosmetic (aesthetic) | Improve proportion of a healthy nostril base — reduce flare, narrow the base | Primary alar base reduction, alone or with rhinoplasty |
| Reconstructive / functional | Restore nostril shape or airway after injury, cleft, burn or a previous over-reduction | Correction of alar notching or nostril stenosis after earlier surgery; cleft-nose alar repositioning |
Most wide nostril corrections in private practice are cosmetic. Cosmetic alar base reduction should not be assumed to be covered by health insurance; coverage, where it exists, applies only to documented reconstructive indications and requires prior verification with your insurer.
Synonyms for wide nostril correction
Patient terms: nostril reduction surgery, nostril narrowing, flared nostril surgery, big nostril surgery, nose base reduction, nostril shrinking
Medical terms: alar base reduction, alarplasty, alar base excision, Weir excision, nostril sill excision, alar wedge resection, alar cinch
Sources: PMC5122555 · PubMed 34782134
Do Your Nostrils Only Look Wide?
Many people describe the same experience: the nostrils look fine from the side, but in front-facing photographs — and especially when smiling — they seem to spread across the face and draw the eye. That gap is real. But wide nostrils may sometimes be an optical effect rather than true alar base excess. A low bridge, under-projected tip or bulbous tip can make the nostrils appear wider, so correction should be planned only after the bridge, tip and base are assessed together.
Three questions patients actually ask at consultation:
- “My nostrils flare when I smile — can that be fixed, or is it just how I smile?”
- “Will the scar show? I’ve seen photos where you can see the cut at the nostril.”
- “If I get my bridge raised, will my nostrils look smaller anyway?”
These concerns do not automatically mean surgery is needed. This is especially relevant in South-Asian and Asian noses, where a low dorsum or weak tip projection may visually exaggerate the base. In such patients, aggressive nostril reduction can make the base too narrow compared with the rest of the nose. If rhinoplasty is being combined with alar base reduction, nostril planning is often considered after the new bridge and tip proportions are understood — this helps avoid over-reduction. The useful question is not “how much can be removed?” but “is the width real, and what will the rest of the nose look like?”
Global and Indian trends
Alar base reduction is one of the most requested add-ons to rhinoplasty worldwide and is especially common in Indian, South-Asian, East-Asian and African patients, where a wider alar base is a normal ethnic feature rather than a deformity. The trend in ethnic rhinoplasty has moved firmly away from Western-proportion narrowing towards conservative, identity-preserving refinement — which is the standard at Allure Medspa.
Sources: PubMed 27261942 · Archives of Facial Plastic Surgery 7(2):94
What Are the Benefits of Wide Nostril Correction?
The main benefits of wide nostril correction are a narrower, better-proportioned nostril base, reduced flare at rest and when smiling, a nostril shape that matches the tip and bridge, and improved balance of the whole lower face — achieved through a short, day-care procedure with a scar hidden in the natural crease. Because tissue is removed, the change is permanent.
Cosmetic benefits
- Reduced flare — the outer nostril edges sit closer to the face instead of spreading outward.
- Narrower base — the distance between the nostrils is brought into proportion with the eyes and mouth.
- Cleaner nostril shape — the nostril opening becomes a softer teardrop rather than a wide oval, particularly in the basal view.
- Less spread when smiling — dynamic flare is reduced, which patients often notice most in photographs.
- Better match with the rest of the nose — when combined with rhinoplasty, the base is sized to the new bridge and tip so nothing looks out of scale.
- Preserved identity — the aim is your nostrils, refined; everyone notices better proportion, no one knows it was surgery.
Practical benefits
- Short procedure, often under local anaesthesia with sedation when done alone.
- Day-care — home the same day; back to routine in days rather than weeks.
- Can be done alone, or added to rhinoplasty without extending recovery meaningfully.
Which Problems Can Wide Nostril Correction Correct?
Wide nostril correction mainly treats alar flare, a wide nostril base, a broad nostril sill, a bulky alar lobule and asymmetric nostrils, alone or combined. It does not reliably correct: a broad bridge or wide bony vault (that is broad nose correction), a bulbous or heavy tip (that is tip surgery), nostrils that only look wide because the bridge is low, thick skin itself, or a nostril shape that is normal for the face but disliked in comparison to a different ethnicity.
| Concern | Relevance to this page | Possible approach | Learn more |
|---|---|---|---|
| Alar flare (rims spread outward) | Core target | Weir / alar wedge excision | This page |
| Wide nostril base / sill | Core target | Nostril sill excision | This page |
| Flare + wide base together | Core target | Combined wedge + sill excision | This page |
| Bulky alar lobule | Core target | Alar wedge planning | This page |
| Asymmetric nostrils | Core target | Differential (side-specific) excision | This page |
| Dynamic flare when smiling | Assessed; treated when true excess exists | Wedge excision ± cinch suture | This page |
| Nostrils look wide because bridge is low | Optical — often NOT this surgery | Dorsal augmentation first | Augmentation Rhinoplasty |
| Whole nose looks wide | Different diagnosis | Broad nose correction | Broad Nose Correction |
| Round, heavy tip | Different diagnosis | Bulbous tip correction | Bulbous Tip Correction |
| Notching / stenosis after earlier surgery | Revision case | Alar rim grafts, scar revision | Revision Rhinoplasty |
| Nostril collapse on breathing in | Assessed first | External valve support (batten / rim grafts) | Functional Rhinoplasty |
The anatomy of the nostril base — the structures this surgery works on
Understanding a few terms makes consultation far easier. (This section also absorbs the former “Alar anatomy” article, which redirects here.)
- Ala (plural alae) — the fleshy, curved outer wall of each nostril. It contains fibro-fatty tissue rather than cartilage, which is why it can be trimmed without weakening the nose’s framework.
- Alar base — where the ala meets the cheek and upper lip. The alar-facial crease here is where the incision is hidden.
- Nostril sill — the floor of the nostril between the ala and the columella. Removing sill tissue narrows the distance between the nostrils.
- Alar rim — the free edge of the nostril. Over-resection here causes notching; it must be preserved.
- Interalar distance — the width between the outer nostril edges. Classically compared with the distance between the inner corners of the eyes, but Indian faces are wider here and the “rule” is only a guide.
- External nasal valve — the nostril opening itself. Narrow it too much and breathing in becomes harder, especially during exercise.
- Skin–soft-tissue envelope — thick, oily or pigmented skin at the base scars less predictably and swells longer.
Sources: PMC5122555
What Are the Limitations of Wide Nostril Correction?
Wide nostril correction cannot narrow the bridge or refine the tip, cannot make nostrils narrower than the airway allows, cannot guarantee an invisible scar, and cannot make two naturally different nostrils perfectly identical. It removes a few millimetres of excess at the base. Being clear about these boundaries before surgery is one of the strongest predictors of satisfaction afterwards.
Millimetres matter here more than anywhere else on the nose. Removing 2 mm too much converts a natural result into a pinched, notched or stenosed nostril that is far harder to repair than it was to create. The alar rim has no cartilage to hold its curve; once the natural arc is interrupted, a step-off or notch is permanent without grafting.
A narrowed base on a nose with a low bridge or weak tip can look worse, not better, because the top of the nose has not changed. Some patients need complementary planning — dorsal augmentation, tip support — to get the balance they are picturing; in those cases the nostril work is often planned last, after the new proportions are known. Results vary by individual anatomy, skin type and healing.
Why “narrowest” is not the goal
- Pinched base: nostrils look tight and operated.
- Alar notching: rim looks indented or cut.
- Nostril stenosis: opening becomes too narrow to breathe well.
- Step-off: the natural curve of the nostril base is interrupted.
- Asymmetry: sides heal or sit differently.
- Facial mismatch: a small base under a broad nose.
- Loss of identity: ethnic character reduced.
Sources: PMC11578213 · PubMed 32812083
Why Consult Before Wide Nostril Correction?
A wide nostril consultation is a diagnostic appointment, not a sales appointment. Its purpose is to decide whether the width is true base excess or an optical effect, exactly which part of the base is responsible (flare, sill, lobule), how your skin is likely to scar, and whether the base should be treated alone or after the bridge and tip.
What happens during a wide nostril consultation?
Assessment typically covers the nose from the front, basal and profile views at rest and while smiling; measurement of interalar distance in relation to your own facial width, not a Western formula; whether the width is flare, sill, lobule or a combination; bridge height and tip projection, to rule out optical width; the alar-facial crease where the scar would sit; skin thickness, oiliness and pigmentation; a check of the external nasal valve and breathing; documented nostril asymmetry (almost everyone has some); full medical history including medicines, supplements, isotretinoin and nicotine use; previous nasal surgery or fillers; scar history elsewhere on the body; and your goals in your own words. You should leave understanding whether the width is real, the recommended technique, the alternatives including no treatment, the realistic amount of narrowing in millimetres, scar expectations for your skin, the risks and the recovery required.
What should I prepare before consultation?
- Your main concern — flare, base width, spread on smiling, or the whole nose.
- Photographs from below and front, at rest and smiling, in even light without makeup — these show flare far better than selfies.
- How your skin has scarred before — a piercing, an old cut, acne marks; photos help.
- All medicines and supplements, including isotretinoin, blood thinners and herbal products.
- Medical and surgical history, including keloid tendency in you or your family.
- Previous nasal treatments — fillers, threads, rhinoplasty — with approximate dates.
- Reference photographs, useful for discussing goals — not as a target to replicate.
Is an online wide nostril consultation possible?
If you are outside Mumbai, you can request a preliminary WhatsApp photo pre-check with front, basal, side and smiling photographs in even, natural lighting, without makeup or filters. This is preliminary guidance only. Photographs cannot assess skin thickness, scar behaviour, nostril valve function or medical fitness, and no definitive diagnosis, technique recommendation or final quotation can be given from them.
Consultation fee: ₹1,500
Link: How to prepare
Which Techniques Are Used in Wide Nostril Correction?
“Technique” in wide nostril correction refers to where and how much tissue is removed from the alar base — the outer wedge for flare, the sill for base width, both for combined problems — and how the incision is designed to hide the scar and preserve the nostril’s natural curve. The selected method depends on whether the main issue is flare, base width, nostril size or combined alar imbalance.
Alar base reduction is a small-area surgery, but not a casual one. A few millimetres can change nostril shape, scar position, facial balance and symmetry, so planning must be conservative, accurate and customised to the patient’s facial proportion, nostril shape, smile movement and Indian facial anatomy.
| Technique | Purpose | Used for | Key caution |
|---|---|---|---|
| Weir excision / alar wedge | Reduces alar flare and lobule width | Excessive flare on front view | Avoid notching or unnatural crease |
| Nostril sill excision | Reduces interalar distance and sill width | Wide nostril floor or wide base | Avoid nostril stenosis |
| Combined wedge + sill excision | Reduces both flare and base width | Mixed flare + wide nostril size | Preserve natural curve |
| Alar cinch suture | Pulls alae inward without external excision | Selected flare or orthognathic context | Effect may be limited |
| Refined incision designs (crease-hugging, stair-step) | Help hide scars, preserve alar curve | Selected ethnic / thick-skin cases | Technique-specific |
| Differential (side-specific) excision | Corrects asymmetry | One nostril wider or more flared | Measured in millimetres per side |
| With rhinoplasty | Matches base with new tip / dorsum | When bridge or tip is also corrected | Usually planned after tip / dorsum changes |
Alar wedge (Weir) excision: A crescent of fleshy alar tissue is removed from the outer nostril wall where it meets the cheek, pulling the flared rim inward. The incision sits in the alar-facial crease. This addresses flare but does not change the distance between the nostrils much.
Sill excision: A small segment of the nostril floor is removed and the nostril is closed inward, bringing the two nostrils closer together. This narrows the base without changing the flare of the rim. The scar sits inside the nostril floor and is rarely visible.
Combined excision: Most patients with true base excess have both flare and width, so a wedge that extends from the outer crease into the sill treats both in one incision. The amount taken from each component is planned separately.
Cinch suture: A suture passed under the base pulls the alae toward the midline without removing skin. Useful for mild dynamic flare, or where excision is undesirable, but the effect is modest and may relax over time.
Is more removal always better?
No. In this surgery, less is almost always more — and “how many millimetres” is the question that matters, not which technique name.
- Anatomy matters most. Flare needs a wedge; width needs a sill cut; taking a sill cut for a flare problem narrows the airway without fixing the flare.
- Ethnicity matters. Indian and South-Asian faces are wider at the base than Western norms; reducing to a Western ratio looks tight and foreign.
- Sequence matters. When rhinoplasty is combined, the base is sized after the new bridge and tip are set, because raising the bridge alone often reduces apparent nostril width.
- Reversal is hard. Tissue removed cannot be put back; an over-reduced base needs grafts to repair. A slightly under-reduced base can be trimmed later.
The right question at consultation is not “which technique do you use?” but “how many millimetres does my base need, and where?”
Sources: PubMed 32812083 · PubMed 34782134 · SAGE Journals – Alar Base Surgery
What Are the Types of Wide Nostril Correction?
Where technique describes how tissue is removed, type describes the scope — whether the base is treated alone or with the rest of the nose, and which components are involved.
- Isolated alar base reduction — for a balanced nose with a base-only concern. Local anaesthesia with sedation, 45–90 minutes, home the same day. The most limited option and the fastest recovery.
- Flare correction — for nostrils that spread outward but are not too far apart. Wedge excision only.
- Base-width correction — for nostrils that sit too far apart without much flare. Sill excision only.
- Combined flare + width correction — for the common mix of both. Combined wedge-and-sill excision. The most comprehensive stand-alone option.
- Asymmetric nostril correction — for one nostril wider, more flared or set differently. Side-specific measurements; some asymmetry usually remains.
- Alar base reduction with rhinoplasty — for a base that must match a new bridge or tip. Done last in the operation, under general anaesthesia, sized to the new proportions. → Rhinoplasty Surgery · Ethnic Rhinoplasty
- Revision alar base correction — for notching, stenosis, step-off or asymmetry after earlier surgery. Often needs alar rim grafts or composite grafts from the ear to restore the curve; technically more demanding. → Revision Rhinoplasty
Combined planning: add bridge augmentation or tip refinement only when it solves a separate concern — and remember that in a low-bridge nose, raising the bridge may reduce the apparent nostril width enough that less (or no) base reduction is needed. → Augmentation Rhinoplasty · Bulbous Tip Correction
Non-surgical options: there is no filler or thread that narrows the nostril base. Filler along a low bridge can preview the “narrower by contrast” effect for 12–18 months but does not change the nostrils themselves. → Non-Surgical Rhinoplasty
How are wide nostrils different from a broad nose or bulbous tip?
| Concern | Main area | Patient usually says | Owned by |
|---|---|---|---|
| Wide nostrils | Alar base / nostril opening | “My nostrils are too wide.” | This page |
| Alar flare | Alar rim / nostril sidewall | “My nostrils flare outward.” | This page |
| Broad nose | Overall bridge, midvault, width | “My whole nose looks wide.” | Broad nose correction |
| Bulbous tip | Nasal tip / lower third | “My tip is round or bulky.” | Bulbous tip correction |
| Low-bridge illusion | Bridge and tip projection | “Nostrils look wide because the nose looks flat.” | Dorsum / tip planning |
How Is Wide Nostril Correction Performed Step-by-Step?
Wide nostril correction is measured before it is cut: the excision is drawn in millimetres on each side with the patient upright and smiling, then removed and closed in the natural crease with fine sutures. When combined with rhinoplasty, the base is done last, after the new bridge and tip are set.
| Step | What happens |
|---|---|
| 1. Consultation and planning | True width vs optical width decided; flare, sill and lobule components measured; skin and scar tendency assessed; alone or with rhinoplasty decided; alternatives, risks and recovery discussed |
| 2. Preoperative preparation | Medical assessment, medication and supplement adjustment (isotretinoin stopped well in advance), confirmed nicotine cessation, standard photographs at rest and smiling |
| 3. Surgical markings | Excision drawn on each ala and sill in millimetres with the patient upright and smiling; existing asymmetry recorded; both sides compared with calipers |
| 4. Anaesthesia | Local anaesthetic with sedation for the stand-alone procedure; general anaesthesia when combined with rhinoplasty. Monitoring is continuous |
| 5. Incision | Placed exactly in the alar-facial crease and / or the nostril floor so the final scar sits in a natural shadow; the alar rim itself is never incised |
| 6. Excision | A measured wedge of alar soft tissue and / or sill removed — conservative on the first pass, checked, trimmed only if needed |
| 7. Symmetry check | Both sides compared before closure; adjustment made in fractions of a millimetre |
| 8. Cinch suture (if planned) | Deep suture passed under the base to bring the alae inward without further excision |
| 9. Layered closure | Deep absorbable sutures take the tension; fine skin sutures close the crease with minimal tension to protect the scar |
| 10. Rhinoplasty sequence (if combined) | Alar base work performed as the final step after dorsum and tip are set, so the base matches the new proportions |
| 11. Dressing | Small tapes or a light dressing at the base; no splint needed for the stand-alone procedure |
| 12. Observation and discharge | Short recovery-room observation; home the same day with written care instructions |
Surgical elements and devices
| Element / device | Possible role | Important consideration |
|---|---|---|
| Calipers and skin marker | Millimetre-accurate, symmetric marking | Marking is the most important step of the operation |
| Fine scalpel (No. 11 / 15) | Precise crease incision | Bevelled to match the crease and hide the scar |
| Deep absorbable sutures | Take tension off the skin closure | Reduce scar widening |
| Fine skin sutures (6-0 / 7-0) | Crease closure | Removed at about 5–7 days |
| Cinch suture (permanent or long-lasting) | Draws alae inward | Used selectively; may relax |
| Alar rim / composite grafts (revision only) | Restore notched or over-reduced rim | Ear cartilage-skin graft; revision cases |
| Silicone scar gel / tape | Scar maturation after suture removal | Started once the wound has sealed |
Sources: PubMed 32812083 · PMC11578213
When Will I See Final Wide Nostril Correction Results?
The narrower base is visible immediately, but swelling at the nostril base and early redness of the incision blur it for the first couple of weeks. A clear sense of the new nostril shape emerges at 3–4 weeks, the base settles fully over 3 months, and the scar continues to fade and flatten for 6–12 months — longer in darker or thicker skin.
| Time | What you may notice |
|---|---|
| First few days | Swelling and tightness at the base, small dressings, mild bruising. Nostrils may look slightly over-narrowed because of swelling — do not judge the result yet |
| 5–7 days | Skin sutures removed. Incision line pink; nostril shape already cleaner |
| 2–3 weeks | Most swelling gone. Scar may be pink or slightly dark; makeup usually permitted once the wound is sealed |
| 4–6 weeks | Base settles into its new shape; smiling no longer pulls at the incision |
| 3 months | Nostril shape essentially final. Scar still maturing; may be darker than surrounding skin in pigmented skin |
| 6–12 months | Scar flattens and fades towards skin colour; final scar appearance. Scars do not disappear but usually sit unnoticed in the crease |
What can affect the final result?
Whether the width was true excess or optical; how many millimetres were removed and from which component; skin thickness, oiliness and pigmentation; keloid or hypertrophic tendency; smoking and nicotine exposure; sun exposure on the healing scar; whether smiling, rubbing or glasses disturbed the incision early; individual healing; and adherence to scar care and follow-up.
Sources: PubMed 17398339 · PMC11578213
What Is the Aftercare After Wide Nostril Correction?
Aftercare after nostril reduction centres on protecting a small incision in a mobile, visible area — keeping it clean and dry, avoiding tension from wide smiling or rubbing in the first days, no nicotine, strict sun protection once healed, and following scar care exactly. These are general principles — your written personal instructions always take priority.
What care is usually advised?
- Keep the incision clean and dry — gentle cleaning as shown; pat, never rub.
- Apply the prescribed ointment to the incision line until sutures are removed.
- Sleep with the head slightly elevated for the first few nights to limit swelling.
- Limit wide smiling, laughing and yawning for the first week — the base moves with the upper lip and tension widens scars.
- Take medicines exactly as prescribed and do not restart blood-thinning medicines or supplements without approval.
- Start scar care once the wound is sealed — silicone gel or tape as instructed, usually from week 2 for 3–6 months.
- Strict sun protection on the scar for at least 6 months — SPF and shade; the base sits in direct light.
- Attend all follow-up appointments — suture removal at 5–7 days, scar review at 3–4 weeks, and later photographs.
What should patients avoid after wide nostril correction?
| Avoid | Why |
|---|---|
| Smoking, vaping, nicotine in any form | Reduces blood supply to the small skin flaps; increases wound breakdown, infection and poor scarring |
| Rubbing, picking or wiping the nose hard | Can open the incision or widen the scar |
| Wide facial expressions in week one | Tension across the incision widens and thickens the scar |
| Makeup or skincare on the incision before it is sealed | Infection and irritation risk |
| Direct sun on the scar (6+ months) | The commonest cause of a dark, visible scar in Indian skin |
| Strenuous exercise (1–2 weeks) | Raises blood pressure and swelling; sweat irritates the incision |
| Swimming, steam, sauna (2 weeks) | Soaks the incision; heat increases swelling |
| Unapproved scar creams, bleaching agents, home remedies | Can cause irritation or pigmentation — check every product with your surgeon |
| Glasses resting on the nose (if combined with rhinoplasty) | Pressure on the healing framework |
| Judging the scar in the first 3 months | Early pinkness or darkness is normal and fades |
Full aftercare detail: Rhinoplasty recovery timeline
What Are the Risks and Complications of Wide Nostril Correction?
Wide nostril correction is generally safe for an appropriately selected patient operated on by a trained plastic surgeon in an equipped facility, and it is a small procedure — but it is surgery on the most visible, least forgiving few millimetres of the face. Expected postoperative effects must be separated from true complications — and no surgeon can eliminate risk.
Common / expected early effects (normal healing, not complications): swelling and tightness at the base; mild bruising; a pink or slightly dark incision line for weeks to months; temporary numbness of the base; mild asymmetry while swelling settles.
Uncommon complications: bleeding; infection; delayed healing or small wound opening at the crease; visible scar; hyperpigmentation of the scar (more common in darker skin); hypertrophic scar; asymmetry after healing; under-correction (width remains); over-correction (base too narrow); dissatisfaction leading to a revision request.
Rare but important: alar notching (rim looks indented or cut); step-off deformity (natural curve of the base interrupted); nostril stenosis (opening too narrow to breathe through comfortably); external valve obstruction; keloid; skin compromise, most strongly associated with nicotine.
How risk is minimised
| Risk area | How we work to minimise it |
|---|---|
| Treating optical width | Bridge and tip assessed first; base reduced only for true excess, and last when combined with rhinoplasty |
| Over-reduction / notching / stenosis | Conservative millimetre planning; alar rim never incised; first pass deliberately under-corrected and checked |
| Asymmetry | Caliper marking on both sides with the patient upright and smiling; side-by-side check before closure |
| Visible or dark scar | Incision hidden in the alar-facial crease; layered, tension-free closure; silicone scar care; strict sun protection; extra counselling in pigmented skin |
| Hypertrophic / keloid scar | Scar history taken; high-risk patients counselled or deferred; early scar treatment if thickening starts |
| Breathing change | External valve checked before surgery; sill excision limited to preserve the airway |
| Nicotine-related healing failure | A clear, enforced nicotine cessation requirement before and after surgery |
| Bleeding | Medication and supplement review, careful haemostasis |
| Infection | Sterile technique, perioperative antibiotics, wound-care instruction |
| Facility and equipment risk | Surgery at an NABH-accredited surgical centre with appropriate equipment |
| Delayed recognition of a problem | Written warning signs, accessible follow-up |
⚠️ When to seek urgent medical attention
Seek urgent advice or immediate emergency care for: rapidly increasing swelling · severe pain · fever · pus-like discharge · wound opening · spreading redness · new or worsening nasal obstruction · chest pain or breathlessness.
In an emergency, go to the nearest emergency department or call emergency services. Do not wait for a WhatsApp or email reply.
Full risk guide: Rhinoplasty Risks & Safety
Sources: Cleveland Clinic – Rhinoplasty · PMC11578213
What Is the Wide Nostril Correction Recovery Timeline?
Recovery after wide nostril correction is short. Swelling and tightness at the base are most noticeable in the first few days; sutures come out at 5–7 days; most patients return to work and daily activity within 3–5 days for the stand-alone procedure, or 7–10 days when combined with rhinoplasty. The scar keeps maturing for 6–12 months. This is a summary — for detailed day-by-day guidance on sleeping position, nasal care, exercise, travel and sun protection, see the rhinoplasty recovery timeline.
| Timepoint | What typically happens |
|---|---|
| First 24–48 hours | Swelling, tightness and mild bruising at the base; small dressings. Mild discomfort controlled with simple medication. Home the same day; rest with head elevated |
| Days 3–5 | Swelling begins reducing. Many patients return to desk work and light social activity (stand-alone procedure) |
| Days 5–7 | Skin sutures removed. Incision pink but closed; gentle cleaning continues |
| Weeks 2–3 | Most swelling gone; makeup permitted over the sealed incision. Silicone scar care begins. Exercise usually cleared |
| Weeks 4–6 | Base settles into its final shape; smiling comfortable. Scar may be pink or slightly dark |
| 3 months | Nostril shape final. Scar maturing; scar care and sun protection continue |
| 6–12 months | Final scar appearance — flattened, faded, sitting in the crease. Revision, if ever needed, is not assessed before this point |
Key recovery points: stand-alone nostril reduction is a day-care procedure with a 3–5 day return to routine · sutures out at 5–7 days · scar care (silicone, sun protection) is the part of recovery that most determines the final look, and it runs for months, not days · when combined with rhinoplasty, follow the rhinoplasty timeline (splint, glasses, 7–10 days) · outstation patients can usually travel home after suture removal.
Do not use another patient’s timeline as permission for exercise, travel or restarting medication.
“Patients treat nostril reduction as a minor procedure — and the operation is. The scar care afterwards is not. The nostril base sits in full sun on an Indian face, and the difference between an invisible scar and a dark line at six months is usually sunscreen and silicone, not surgery.”
Links: Recovery timeline day 1 to final result · Outstation patients
Medical Codes for Wide Nostril Correction
Codes below are for administrative and documentation reference. All codes must be verified against the current CPT and ICD-10 code sets before publication and before any use in documentation.
| CPT Code | CPT Description | ICD-10 |
|---|---|---|
| 30400 | Rhinoplasty, primary; lateral and alar cartilages and/or elevation of nasal tip (used for isolated alar base work by many payers) | Z41.1 (cosmetic) · M95.0 (acquired deformity of nose) |
| 30410 | Rhinoplasty, primary; complete, external parts including bony pyramid, lateral and alar cartilages, and/or elevation of nasal tip (when combined with rhinoplasty) | Z41.1 · M95.0 |
| 30430 | Rhinoplasty, secondary; minor revision (small amount of nasal tip / alar work) — revision alar base cases | Z41.1 · Z98.890 |
| 30460 | Rhinoplasty for nasal deformity secondary to congenital cleft lip and/or palate, including columellar lengthening; tip only (cleft alar repositioning) | Q30.x · Q35–Q37 |
| 21235 | Graft; ear cartilage, autogenous, to nose or ear (composite graft for notching repair) | — |
| 11440–11446 | Excision, benign lesion, face/nose (sometimes used by payers for isolated soft-tissue alar excision) | — |
(FAQs) Frequently Asked Questions About Wide Nostril Correction
Q1. Can wide nostril correction fail or need revision?
Ans. Yes. Under-correction (width remains), over-correction (notching, stenosis), asymmetry or a visible scar can occur. Under-correction is easy to revise with a small further trim; over-correction is much harder and may need grafts from the ear to rebuild the rim. Revision is assessed only after 6–12 months of scar maturation.
Q2. Is wide nostril correction safe in India?
Ans. It is generally safe for an appropriately selected patient when performed by a qualified plastic surgeon in an accredited facility. Recognised risks remain — scarring, asymmetry, notching. Judge the surgeon’s qualification, rhinoplasty volume and experience with Indian skin, not the country.
Q3. How long does wide nostril correction surgery take?
Ans. The stand-alone procedure usually takes 45–90 minutes under local anaesthesia with sedation. When combined with rhinoplasty it adds about 20–30 minutes at the end of the operation. The planned duration is confirmed after examination.
Q4. Can alar base reduction be done alone?
Ans. Yes, when the concern is isolated nostril width or flare on an otherwise balanced nose. It can also be combined with rhinoplasty when the bridge, tip or overall proportions need correction together — in which case the base is done last.
Q5. Is wide nostril correction the same as bulbous tip correction?
Ans. No. A bulbous tip is a tip-definition problem, while wide nostrils are an alar-base problem. They may coexist, but the techniques differ — tip surgery reshapes the tip cartilages, alar base reduction changes nostril-base width or flare.
Q6. Can wide nostril correction be overdone?
Ans. Yes. Over-reduction can create a pinched base, alar notching, nostril stenosis, asymmetry or an unnatural nostril shape. Conservative planning is especially important in ethnic noses where identity should be preserved.
Q7. Does wide nostril correction work for Indian noses?
Ans. Yes, but planning must respect Indian and South-Asian facial features. Wider alar bases and thicker, more pigmented skin are common, so the goal is balanced, natural reduction rather than narrowing to a Western ratio that changes ethnic character — and scar care is planned for Indian skin.
Q8. If my bridge is low, do I still need nostril reduction?
Ans. Not always. A low bridge or under-projected tip can make nostrils look wider. In some cases, bridge augmentation or tip refinement reduces the apparent base width and reduces or removes the need for alar base reduction. This is why the base is assessed after the bridge and tip.
Q9. Will the scar be dark on my skin?
Ans. In darker or thicker skin the scar often goes through a darker phase in the first months before fading. Hiding the incision in the crease, tension-free closure, silicone scar care and strict sun protection for six months are what keep it subtle. No scar can be promised invisible.
Q10. When can I fly after wide nostril correction?
Ans. For the stand-alone procedure, usually after suture removal at 5–7 days, with clearance at that review. When combined with rhinoplasty, follow the rhinoplasty clearance. Do not book non-refundable travel around an assumed date.
Q11. Does insurance cover wide nostril correction?
Ans. Cosmetic alar base reduction should not be assumed to be covered by health insurance. Coverage, where it exists at all, applies only to documented reconstructive indications (cleft, injury, stenosis affecting breathing) and must be confirmed directly with your insurer before surgery.
Related Links
- Rhinoplasty Surgery (hub)
- Rhinoplasty Cost
- Rhinoplasty Before & After Gallery
- Broad Nose Correction
- Bulbous & Boxy Tip Correction
- Drooping Tip Correction
- Crooked Nose Correction
- Ethnic Rhinoplasty
- Augmentation Rhinoplasty
- Nasal Deformities Treated by Rhinoplasty
- Revision Rhinoplasty
- Functional Rhinoplasty
- Rhinoplasty Recovery Timeline
- How to Prepare for Rhinoplasty
- Rhinoplasty Risks & Safety

