
Ethnic Rhinoplasty in Mumbai: Refined With Precision, Recognisably You

Indian Board Certified Plastic Surgeon
M.CH, MS, ISAPS Mentor
16000+ Cosmetic Surgeries
1500+ Rhinoplasty Surgeries
Ethnic rhinoplasty is nose surgery planned around your own anatomy, background and identity rather than one universal “ideal” nose — building a low bridge, supporting a weak tip under thick skin, balancing a wide base — so the nose looks refined and proportionate while the face stays recognisably yours. At Allure Medspa Mumbai, Dr. Milan Doshi has spent 27 years refining Indian, South-Asian, Asian, African, Middle-Eastern and mixed-heritage noses on the principle that features are not flaws: everyone notices better balance, no one knows it was surgery.
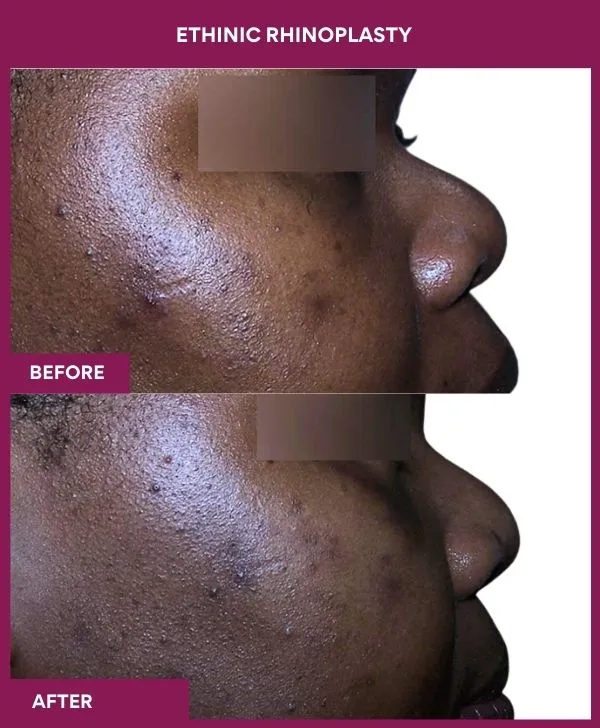
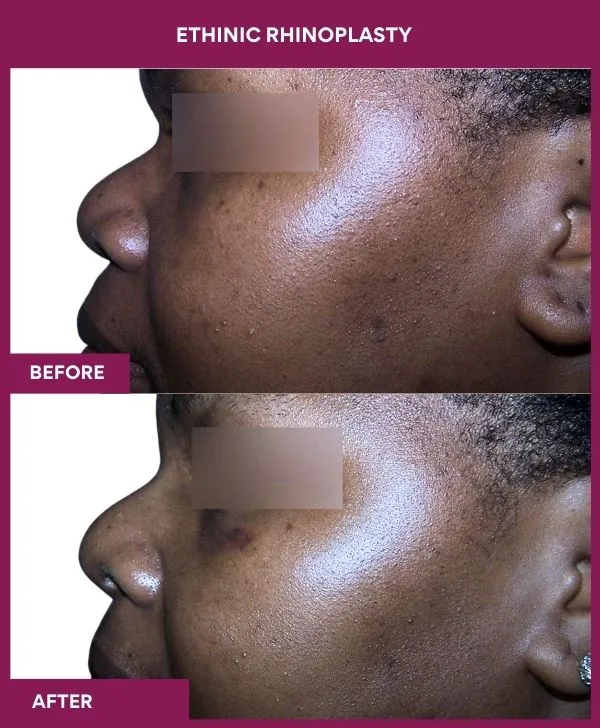
Ethnic Rhinoplasty Before And After Images
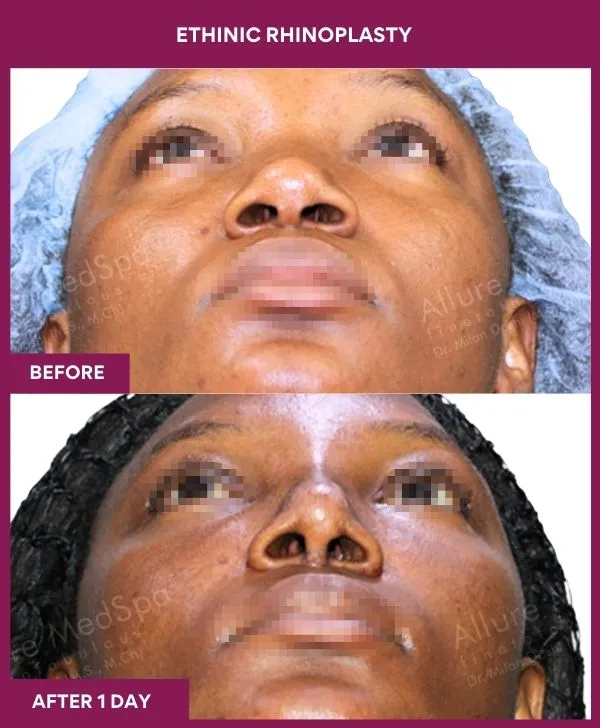
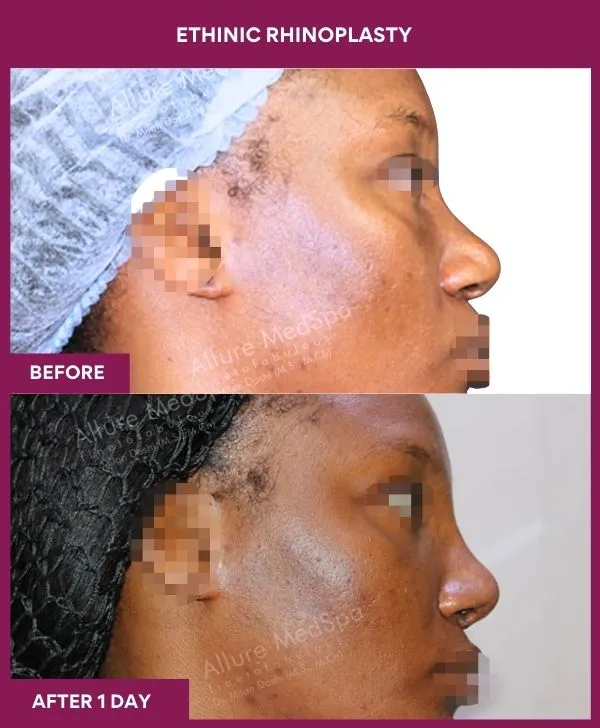
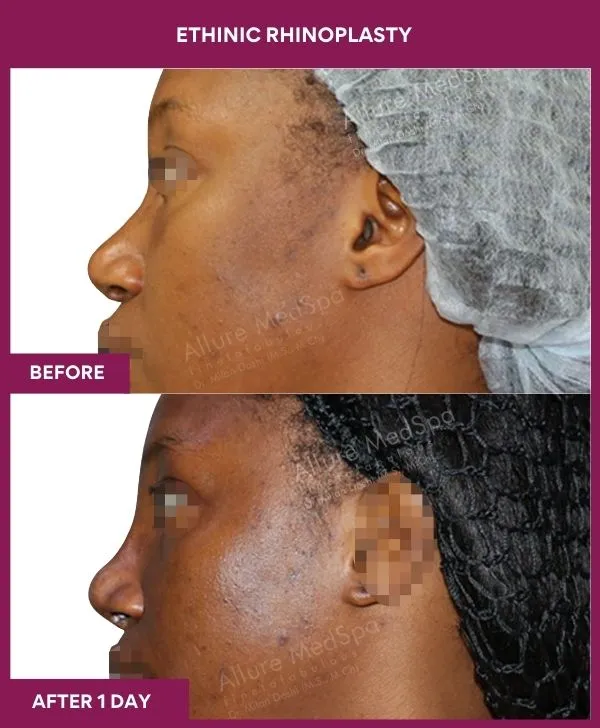
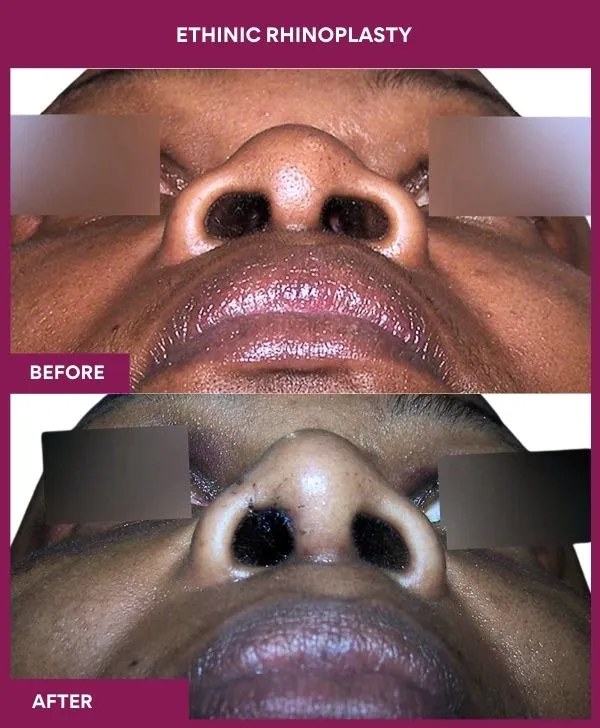
Rhinoplasty Surgery Testimonials: Celebrities Patient

Awarded by Google.com
Rating: 4.7
Reviews: 485+

Awarded by WhatClinic.com
Rating: 4.8
Reviews: 119+

Awarded by Realself
Rating: 4.9
Reviews:453+

Awarded by Facebook
Rating: 4.6
Reviews:105+
Dr Milan Doshi and his staff are very professional and committed as the centre is highly equipped with advanced technology. I had closed rhinoplasty 4 months back and I’m seeing the results as to how it becomes successful.
Deepika Shetty
The doctor explained everything clearly and the surgery was smooth. Recovery was faster than I expected and the team was very supportive.
Rahul Mehta
Very natural results and excellent staff. From consultation to follow-up, the experience was outstanding and boosted my confidence.
Sneha Kapoor
Video: Best Rhinoplasty Surgeon explain nose reshape procedure
Dr Milan Doshi is describing the Rhinoplasty Surgery in detail with benefits, techniques, recovery, result, risk and complecations
Am I a Candidate?
(4 quick questions)
Quick Facts About Ethnic Rhinoplasty
TIME REQUIRED
2–3.5 hours
ANESTHESIA
General
HOSPITAL STAY
Day-care or 1 night
PAIN LEVEL
Mild–moderate
BACK TO WORK
7–10 days
RESULTS LAST
Permanent
SUCCESS RATE
97–98%
COMPLICATIONS
Under 2–3%
How Much Does Ethnic Rhinoplasty Cost in Mumbai?
Ethnic rhinoplasty in Mumbai starts from ₹1,40,000 to ₹2,80,000 and varies with what the nose needs — bridge augmentation, tip support, base refinement, hump softening, or a whole-nose plan — the material chosen (septal, ear or rib cartilage, or an implant), whether alar base or septal work is combined, and whether the case is primary or revision. A final quotation follows examination and a written surgical plan — it cannot be given accurately by phone or from photographs.
| Ethnic rhinoplasty scope | Indicative price range |
|---|---|
| Tip support and refinement only (thick-skin bulbous tip) | ₹1,40,000 – ₹1,80,000 |
| Bridge augmentation with septal / ear cartilage ± tip support | ₹1,50,000 – ₹2,10,000 |
| Bridge + tip + alar base (the typical Indian / Asian whole-nose plan) | ₹1,80,000 – ₹2,50,000 |
| Hump softening with tip definition (Middle-Eastern pattern) | ₹1,60,000 – ₹2,30,000 |
| Broad nose narrowing with structural support | ₹1,70,000 – ₹2,50,000 |
| Rib cartilage augmentation (major low bridge) | ₹2,10,000 – ₹2,80,000 |
| Ethnic rhinoplasty with septoplasty (functional component) | ₹1,80,000 – ₹2,80,000 |
| Revision ethnic rhinoplasty | Quoted after examination |
Disclaimer note: +5% GST · Includes surgeon, anaesthesia, OT, hospital stay, medicines and follow-ups. Implant material, if chosen, is quoted separately. EMI available.
Get your exact quote & surgery plan
Share your details — our team responds within working hours with cost, EMI options and next steps.
Most Common Question People Ask
Q1. Will I still look like myself?
Ans. That is the aim. The plan defines what changes and what remains unchanged. A refined bridge, supported tip or balanced base should improve facial harmony without making the face look unfamiliar or culturally disconnected — your family should notice balance, not surgery.
Q2. How much does ethnic rhinoplasty cost in Mumbai?
Ans. The guide range is ₹1,40,000–₹2,80,000 plus 5% GST, depending on whether augmentation, cartilage grafting, implant, alar-base work, septal correction or revision surgery is required. A written quotation follows examination.
Q3. Is ethnic rhinoplasty only for Indian patients?
Ans. No. It includes Indian, South-Asian, East-Asian, African, Middle-Eastern, Latin and mixed-ethnicity patients. The term means the surgeon plans around ethnic anatomy, skin type, cartilage strength and identity rather than using one standard template.
Q4. Why do some ethnic rhinoplasty cases need augmentation?
Ans. Many Asian and some South-Asian noses have lower dorsal height or weaker projection. In such cases, augmentation and support create better balance than reduction alone — building, not flattening. Material choice depends on skin, cartilage, revision status and patient preference.
Q5. Does thick skin limit the result?
Ans. Thick skin reduces visible sharpness and slows swelling resolution. This does not mean surgery cannot help; it means the underlying structure must be strong and expectations should focus on gradual refinement rather than early sharp definition.
Q6. How long does recovery take?
Ans. Splint off at about a week, desk work in 7–10 days, social recovery over 2–3 weeks. Thick skin and structural grafting make final definition slower — often 12 months, sometimes 18 — so early swelling should not be judged as the result.
Q7. Will it look natural?
Ans. A natural result depends on refusing over-narrowing, over-rotation and over-projection, building support where the nose is weak rather than cutting, and matching the nose to your own eyes, lips, cheeks and chin — not to a Western reference. Results vary between individuals and cannot be guaranteed.

Why Choose Dr. Milan Doshi?
Dr. Milan Doshi, MCh, MS — Indian board-certified plastic surgeon with 27+ years in aesthetic surgery and 1,500+ rhinoplasties, the large majority on Indian and South-Asian noses. Choosing a surgeon for ethnic rhinoplasty is not only about technique; it is about judgement — careful listening, facial analysis, honest limits, and a plan that explains what should change and what should deliberately remain unchanged. ISAPS mentor, trusted by patients from 70+ countries. Consults at Andheri West; surgeries at the NABH-accredited surgical centre, Goregaon West.
Dr Doshi Note: “In ethnic rhinoplasty, my first job is to listen and understand what the patient wants, but also to explain what should not be changed. Every face is different, so every rhinoplasty must be tailor-made. Sometimes saying “no” to an unsuitable request is the most important decision. The goal is natural refinement — everyone notices better balance, but no one knows it was surgery.”
The Complete Guide About Ethnic Rhinoplasty
What Is Ethnic Rhinoplasty?
Ethnic rhinoplasty means nose surgery planned around your ethnic anatomy, cultural identity and personal goals rather than one universal “ideal” nose. The philosophy is careful refinement: improve proportion where needed, preserve meaningful features, and avoid a homogenised result that no longer belongs to your face. In practice, preserving identity may mean refusing over-narrowing, avoiding an over-sharp tip, or preserving a gentle dorsal character when it suits the patient’s face.
This distinction matters. Classical rhinoplasty teaching was developed on thin-skinned, high-bridged European noses and is largely about reduction. Most Indian, Asian and African noses have thick skin, a low bridge and weak tip support — and need building, not reducing. Applying reduction thinking to them produces the flat, pinched, operated look that patients fear most.
What this means in planning
- Identity: your ethnic features are not treated as flaws.
- Balance: the nose is planned with the eyes, lips, cheeks, chin and face.
- Specificity: Indian, Asian, African, Middle-Eastern and mixed-ethnicity noses are not planned the same way.
- Restraint: not every wide bridge needs aggressive narrowing.
- Support: low dorsum or weak tip support may need augmentation, not reduction.
- Function: breathing and structure must be protected.
How do ethnic noses differ anatomically?
Ethnic rhinoplasty starts with anatomical mapping, because skin thickness, dorsum height, tip strength, cartilage quality and alar base width can vary by background. These are planning patterns, not labels; every patient still needs individual assessment before deciding on augmentation, reduction, grafting or base refinement.
| Background | Skin | Dorsum / bridge | Tip | Base |
|---|---|---|---|---|
| Indian / South-Asian | Often thicker | Often lower dorsal height | May be broad or under-projected | May be relatively broad |
| East-Asian | Often thick, sebaceous | Low, wide radix or dorsum | Rounded, under-projected, weaker LLC | Often wider or flared |
| African / Afro-descendant | Thick, fibrofatty | Low radix, short nasal bones, flat dorsum | Bulbous or under-projected | Wide alar base and flare |
| Middle-Eastern | Thin to moderate | Prominent dorsal hump / strong profile | More projected in many cases | May still need width assessment |
| Mixed ethnicity | Variable | Variable | Variable | Variable |
Is ethnic rhinoplasty cosmetic or reconstructive?
| Type | Main purpose | Common example |
|---|---|---|
| Cosmetic (aesthetic) | Refine proportion in a healthy nose while preserving ethnic character | Bridge augmentation with tip support in a South-Asian nose |
| Functional / reconstructive | Restore breathing or structure after injury, or rebuild a nose Westernised by previous surgery | Revision with rib cartilage to restore dorsal height and ethnic profile after over-reduction |
Most ethnic rhinoplasties in private practice are cosmetic. Cosmetic rhinoplasty should not be assumed to be covered by health insurance; coverage, where it exists, applies only to documented functional indications and requires prior verification with your insurer.
Synonyms for ethnic rhinoplasty
Patient terms: Indian nose job, Asian nose job, nose surgery for Indian face, natural rhinoplasty, rhinoplasty without looking Western, nose refinement surgery, thick skin nose job
Medical terms: ethnic rhinoplasty, identity-preserving rhinoplasty, structural rhinoplasty, augmentation rhinoplasty, Asian rhinoplasty, South-Asian rhinoplasty, African-American rhinoplasty, Middle-Eastern rhinoplasty
Sources: PMC12456530 · PMC11607280 · PMC4656157 · PMC4174207
🩺 Dr. Doshi’s Note —
“Preserving identity means I do not make every nose small, narrow, and Western-looking. In many Indian faces, over-narrowing can look artificial. Some patients may even look better with a little dorsal strength or character, especially in Kashmiri, Punjabi, Middle-Eastern, or mixed-ethnicity noses. My aim is refinement, not removing the patient’s natural identity.”
Will I Still Look Like Myself?
Many patients considering ethnic rhinoplasty are not asking for a new face; they are asking whether the bridge can look cleaner, the tip more supported, or the base more balanced while they still look like themselves. This concern is valid, and it should guide the consultation.
Three things patients actually say at consultation:
- “I want refinement, not a different identity — I do not want my nose to look copied from someone else.”
- “I want my family to notice harmony, not surgery.”
- “I am worried about going too sharp, too narrow, or too lifted.”
These concerns do not automatically mean surgery is needed, and they certainly do not mean a Western template. A good consultation should make these points explicit. The surgeon should ask what you want changed and also what you want preserved. The useful question is not “what is the ideal nose?” but “which specific changes create natural balance for this person — and which features should be deliberately left alone?”
Why is a “Western ideal” nose the wrong goal?
A Western-template nose can look disconnected when placed on a non-Western face. In ethnic rhinoplasty, the better goal is proportion: a bridge, tip and base that work with the patient’s ethnicity, skin, lips, eyes, cheeks and chin rather than against them.
- Over-rotation: the tip looks too lifted.
- Over-projection: the nose looks too sharp for the face.
- Over-narrowing: the bridge or base looks pinched.
- Identity mismatch: the face looks less recognisable.
- Reduction-only thinking: low-dorsum noses may need support, not flattening.
- Revision difficulty: over-reduction may be hard to reverse.
The question should not be, “How do we make this look Western?” It should be, “Which specific changes create natural balance for this person?”
Global and Indian trends
Rhinoplasty is one of the most requested cosmetic operations worldwide, and the fastest growth is in Asia, the Middle East and among diaspora patients — exactly the noses classical techniques were not designed for. Surgical teaching has shifted decisively from reduction to structural, identity-preserving approaches; the leading rhinoplasty societies now describe “ethnic rhinoplasty” not as a niche but as the majority of modern practice. In India, where nearly every rhinoplasty patient has thick skin and a low-to-moderate bridge, that structural, support-first philosophy is the standard at Allure Medspa.
What Are the Benefits of Ethnic Rhinoplasty?
The main benefits of ethnic rhinoplasty are a nose in proportion to your own face — a defined bridge where there was none, a supported tip that no longer looks heavy, a base in balance with the eyes and mouth, a profile softened where it was strong — achieved without the pinched, flattened or “done” look that follows template surgery. Because the work is structural, the result is durable, and because the plan protects identity, it ages naturally with the face.
Cosmetic benefits
- Definition without Westernisation — dorsal lines and tip-defining points appear, but the nose still belongs to your heritage.
- A bridge that suits the face — built up in low-bridge noses, gently softened in strong-profile noses; never flattened, never over-built.
- A supported tip — structural grafts lift and define a weak tip through thick skin without cutting cartilage away.
- Balanced base — nostrils and width refined in proportion to the new bridge and tip, not to a Western ratio.
- Harmony with the rest of the face — the nose stops drawing attention; eyes and smile become the focus.
- Preserved identity — family and friends notice you look well, rested or balanced; no one can say what changed.
Functional and long-term benefits
- Support-first techniques protect or improve breathing rather than narrowing the airway.
- A structurally supported nose resists the collapse and drooping that over-reduced ethnic noses suffer with age.
- Conservative planning keeps revision options open — cartilage is preserved, not discarded.
Which Problems Can Ethnic Rhinoplasty Correct?
Ethnic rhinoplasty addresses the concerns typical of thick-skinned, low-bridged or strong-profiled noses — a flat bridge, a heavy under-projected tip, width at the bones or base, a dorsal hump on a strong face, and the “whole nose” combination — always routed to the technique the anatomy needs. It does not reliably correct: skin thickness itself, a Western template wish, features around the nose that make it look big (a small chin, flat cheeks), or breathing problems on their own.
| Concern | Relevance to this page | Possible approach | Learn more |
|---|---|---|---|
| Low or flat bridge (Indian, Asian, African) | Core target | Dorsal augmentation — cartilage, DC-F or selected implant | Augmentation rhinoplasty |
| Round, heavy, under-projected tip under thick skin | Core target | Structural tip support, grafts, conservative soft-tissue management | Bulbous tip correction |
| Whole nose looks wide | Core target | Augmentation first; osteotomies with support if still needed | Broad nose correction |
| Wide nostrils / alar flare | Core target | Conservative alar base reduction to ethnic proportion | Wide nostril correction |
| Dorsal hump on a strong face (Middle-Eastern) | Core target | Conservative hump softening; profile character preserved | Reduction rhinoplasty |
| Drooping tip when smiling | Addressed when present | Tip rotation and support | Drooping tip correction |
| “The whole lower nose looks heavy” | Core target | Bridge + tip + base whole-nose plan | This page |
| Nose Westernised by previous surgery | Revision case | Rebuild dorsal height and tip with rib / ear cartilage | Revision rhinoplasty |
| Deviated septum / blocked breathing | Combined when present | Septorhinoplasty | Septorhinoplasty |
| Small chin making the nose look large | Not corrected by rhinoplasty | Chin augmentation assessed | Chin augmentation |
Common goals by background
Ethnic rhinoplasty goals differ by anatomy and patient preference, so they should be discussed as patterns rather than assumptions. One South-Asian patient may need dorsal support, another tip refinement, and another only subtle base balance.
- South-Asian / Indian: dorsal definition, tip support, broad-nose refinement, bulbous tip correction, base balance.
- East-Asian: bridge augmentation, tip projection, rounded-tip refinement, alar base balance.
- African / Afro-descendant: nostril and alar-base refinement, tip definition, possible dorsal support.
- Middle-Eastern: dorsal hump refinement, profile straightening, tip definition, preservation of facial strength.
- Mixed ethnicity: custom planning based on actual anatomy, not category assumptions.
The anatomy behind ethnic planning — the structures this surgery works on
- Skin–soft-tissue envelope — thick, sebaceous skin with a fibrofatty layer beneath. It hides fine work, swells for longer, and is the main reason ethnic rhinoplasty builds structure rather than removing it.
- Radix and dorsum — often low in Indian, Asian and African noses; height here creates dorsal lines and makes the nose look narrower without any narrowing.
- Nasal bones — often short and wide; narrowing must be conservative to keep the airway open.
- Lower lateral cartilages (tip) — frequently thin, weak and splayed; the tip needs reinforcement (struts, extension grafts), not trimming.
- Alar base — naturally wider in many ethnic groups; the “ideal” inter-canthal rule is a Western guide, not a target.
- Septum — the usual graft source; often smaller in Asian noses, which is why ear or rib cartilage is more frequently needed.
- Surrounding face — cheek projection, chin size and lip position decide how the nose reads; they are assessed even when only the nose is treated.
Sources: Rhinoplasty Society – Ethnic Rhinoplasty · ScienceDirect S1043181008000237 · PMC4656157
What Are the Limitations of Ethnic Rhinoplasty?
Ethnic rhinoplasty cannot make thick skin thin, cannot make a nose as small or sharp as a thin-skinned Western reference without cost, cannot change the features around the nose, cannot guarantee symmetry, and will not produce another person’s nose. It refines what is there within the limits of your tissue — and deliberately declines requests that would erase identity. Being clear about these boundaries before surgery is one of the strongest predictors of satisfaction afterwards.
Thick skin is the ceiling. In ethnic rhinoplasty, thick skin matters because it can soften visible definition and delay final refinement. The practical implication is not “nothing can be done” — it means the surgeon may need stronger structure underneath, and the patient must judge the result later, not too early. This is especially relevant in many South-Asian, East-Asian and African-descent noses. Cutting more cartilage to force definition through thick skin weakens support without sharpening the surface.
A refined nose on a face with flat cheeks or a small chin can still look large; some patients need complementary planning to get the balance they are picturing. Template requests — “this celebrity’s nose” — are declined, because the outcome would be a nose that fits neither the reference nor the patient. Results vary by individual anatomy, skin thickness and healing.
Why “smaller, sharper, narrower” is not the goal
- Pinched tip: over-resected cartilage under thick skin collapses.
- Flat, wide look: reducing a low bridge removes the only definition it had.
- Operated look: an over-lifted or over-narrow nose reads as foreign on the face.
- Breathing loss: aggressive narrowing closes the valve.
- Loss of identity: the face no longer matches the family, the culture or the person.
- Hard revision: rebuilding a Westernised nose needs rib cartilage and rarely fully restores what was removed.
Sources: PubMed 17398339 · PMC4174207 · PMC11607280
Why Consult Before Ethnic Rhinoplasty?
An ethnic rhinoplasty consultation is a diagnostic appointment, not a sales appointment. Its purpose is to translate your concern into anatomy — bridge, tip, base, hump, width, projection — to decide what needs building, what needs refining and what should be preserved, and to make sure the plan protects both breathing and identity.
What happens during an ethnic rhinoplasty consultation?
Assessment typically covers the nose in relation to your whole face — eyes, cheeks, lips, chin — from the front, profile, three-quarter and base with the patient upright; skin thickness by pinch and its sebaceous quality; radix and dorsal height; tip strength, projection and rotation; nasal bone width; alar base width in relation to your own facial width, not a Western formula; cartilage availability (septum, ear) for grafting; the airway — septum and valves — with a breathing history; documented asymmetry; full medical history including medicines, supplements and nicotine use; previous nasal surgery, fillers or trauma; and, above all, your goals in your own words — what you want changed and what you want kept.
You should leave understanding your diagnosis by component, the recommended plan and where support will be built, the alternatives including no treatment, the realistic degree of definition for your skin, what will deliberately not be changed, the risks and the recovery required.
What should I prepare before consultation?
- Your main concerns — bridge, tip, width, base or profile — in order of priority.
- What you want to KEEP — this matters as much as what you want changed.
- Clear front, side, oblique and base-view photographs in even light without makeup.
- Family photographs if you want the result to sit naturally among relatives.
- All medicines and supplements, including blood thinners, isotretinoin and herbal products.
- Medical and surgical history, including anaesthetic problems and breathing issues.
- Previous nasal treatments — fillers, threads, prior rhinoplasty — with approximate dates.
- Examples of what you like and dislike — as communication tools, not as templates; the final plan comes from your anatomy and goals.
Is an online ethnic rhinoplasty consultation possible?
If you are outside Mumbai — many of our ethnic rhinoplasty patients are NRIs or from overseas — you can request a preliminary WhatsApp photo pre-check with front, side, three-quarter and basal photographs in even, natural lighting, without makeup or filters. This is preliminary guidance only. Photographs cannot assess skin thickness, cartilage strength, tip support, airway function or medical fitness, and no definitive diagnosis, technique recommendation or final quotation can be given from them. Outstation and overseas patients are guided on how long to stay in Mumbai.
Consultation fee: ₹1,500
Links: How to prepare · Outstation patients
Which Techniques Are Used in Ethnic Rhinoplasty?
“Technique” in ethnic rhinoplasty is mostly about building: augmenting the bridge, reinforcing the tip, managing thick soft tissue and refining the base — with reduction used sparingly and always with support. Ethnic rhinoplasty often uses augmentation and structural support, because many patients need better projection, stronger tip definition or a more stable bridge rather than reduction alone. Material choice may include septal, ear or rib cartilage, diced cartilage, selected implants and structural tip grafts. These are surgical decisions made from your anatomy, not a menu.
| Option | Common use | Advantages | Cautions |
|---|---|---|---|
| Septal cartilage | Small grafts, spreader grafts, tip support | Natural tissue, same surgical field | Quantity may be limited |
| Ear cartilage | Tip contour or selected support | Natural tissue, useful curve | Donor-site scar / soreness |
| Rib cartilage | Major augmentation or revision support | Strong volume and support | Warping, donor-site morbidity |
| Diced cartilage (in fascia) | Dorsal contouring | Softer dorsal shaping | Technique-dependent |
| Silicone implant | Dorsal augmentation | Predictable shape, no donor site | Infection, extrusion, displacement |
| ePTFE / Gore-Tex | Dorsal augmentation | Selected implant option | Infection / extrusion / revision complexity |
| Septal extension graft | Tip projection and rotation | Strong tip control | Can feel stiff if overbuilt |
| Tip / shield grafts | Definition through thick skin | Pushes definition to the surface | Must be well-camouflaged |
| Conservative soft-tissue debulking | Thick supratip / tip | Lets the framework show | Must protect blood supply |
| Conservative osteotomies + spreader support | Wide bony vault | Narrows without collapsing the valve | Restraint; ethnic width is normal |
| Alar base reduction (millimetre-planned) | Wide or flared nostrils | Balances base to new bridge | Scar, notching; ethnic proportion, not Western |
| Open approach | Full exposure for grafting | Most ethnic cases | Small columellar scar |
| Closed approach | Selected limited refinements | No external scar | Less exposure |
Build the bridge: a low dorsum is raised with carved or diced cartilage — or, in selected cases, an implant kept off the tip — creating the dorsal lines that make a wide nose look narrow. This single step often removes the need for any bone narrowing.
Support the tip: a septal extension graft or strut anchors the weak tip cartilages, and a tip graft pushes definition through thick skin. Cartilage is added, not removed.
Manage the envelope: in selected thick-skin noses the fibrofatty layer is conservatively thinned so the refined framework can show — always sparingly, to protect the skin.
Refine the base last: nostrils are sized to the new bridge and tip, in millimetres, to the patient’s own facial proportion.
Is cartilage always better than an implant in ethnic noses?
Cartilage is usually preferred — but neither option is universally superior, and the honest answer depends on the nose.
- Skin matters most. Thick ethnic skin tolerates an implant well and hides graft edges; thin-skinned Middle-Eastern noses favour cartilage and fascia.
- Height matters. Moderate augmentation with tip support is best done with the patient’s own cartilage; large augmentation means rib or an implant, and that trade-off is discussed openly.
- Follow-up matters. Overseas and outstation patients who cannot return easily are usually better served by cartilage, which needs no lifelong surveillance.
- Revision matters. A nose Westernised by earlier surgery almost always needs rib cartilage to rebuild; implants are avoided in scarred, thin tissue.
The right question at consultation is not “do you use implants?” but “what does my bridge, my tip and my skin need — and what happens if it ever has to be revised?”
Links:
Augmentation rhinoplasty (materials in detail) · Open technique · Closed technique
Sources: PubMed 35365029 · PubMed 36041000 · PMC3321146
🩺 Dr. Doshi’s Note —
“For ethnic rhinoplasty, my first preference is usually the patient’s own cartilage whenever good structural support is needed. It is natural tissue and useful for tip support, bridge shaping, and revision planning. Implants may be considered in selected bridge-augmentation cases, but not as a casual shortcut. The final choice depends on cartilage availability, skin thickness, required height, revision status, and the patient’s anatomy.”
What Are the Types of Ethnic Rhinoplasty?
Where technique describes how each component is built or refined, type describes the pattern — which background and which combination of concerns the plan is built around. These are starting patterns; every plan is individual.
- Indian / South-Asian rhinoplasty — the commonest pattern at Allure Medspa: thick skin, moderate-to-low bridge, heavy under-projected tip, sometimes a wide base or a modest hump. Bridge support, tip reinforcement and conservative base work; hump softened rather than removed.
→ Broad nose correction | Bulbous tip correction - East-Asian rhinoplasty — low radix and dorsum, weak rounded tip, wider base. Dorsal augmentation with tip projection; alar base balanced last.
→ Augmentation rhinoplasty - African / Afro-descendant rhinoplasty — thick fibrofatty skin, flat dorsum, short bones, wide flared base. Structural augmentation, tip definition through grafts, millimetre-planned alar base work.
→ Wide nostril correction - Middle-Eastern rhinoplasty — thin-to-moderate skin, strong dorsal hump, projected tip. Conservative hump reduction with spreader support, tip refinement, profile strength preserved.
→ Reduction rhinoplasty - Mixed-heritage rhinoplasty — no category assumptions; each component assessed on its own anatomy.
- Ethnic septorhinoplasty — any of the above combined with septal correction for breathing.
→ Septorhinoplasty - Revision ethnic rhinoplasty — restoring dorsal height, tip support and ethnic character to a nose over-reduced or Westernised by earlier surgery; usually rib cartilage.
→ Revision rhinoplasty
Combined planning: chin augmentation or cheek support is considered when the surrounding face is what makes the nose look large; alar base work is added only when the base will look wide under the new bridge. More procedures do not automatically mean a better result.
Non-surgical options: hyaluronic-acid filler along a low bridge can preview the augmentation effect for 12–18 months; it cannot reduce, narrow or support anything and carries a rare but serious vascular risk.
→ Non-surgical rhinoplasty
How Is Ethnic Rhinoplasty Performed Step-by-Step?
Ethnic rhinoplasty builds before it refines — graft material first, bridge and tip support second, conservative reduction and base work last — so the nose is never left smaller but weaker. Most cases are done open for the exposure grafting needs; incisions sit inside the nostrils plus a small cut across the columella, with hidden incisions at the ear or breast fold if cartilage is harvested there.
| Step | What happens |
|---|---|
| 1. Consultation and planning | Concern translated into components; what to build, refine and preserve decided; skin, cartilage and airway assessed; material chosen with the patient; alternatives, risks and recovery discussed. |
| 2. Preoperative preparation | Medical assessment, investigations, anaesthetic review, medication and supplement adjustment, confirmed nicotine cessation, standard photographs. |
| 3. Surgical markings | Dorsal target line, tip position, base marks and existing asymmetry marked with the patient upright; donor site marked. |
| 4. Anaesthesia | General anaesthesia with the airway protected; local anaesthetic with adrenaline in the nose and donor site. Monitoring is continuous. |
| 5. Graft harvest | Septal cartilage through the nose; ear or rib cartilage through hidden incisions where more material is needed. |
| 6. Exposure | Open (usual) or closed approach; skin and soft tissue lifted in the correct plane; thick supratip tissue conservatively thinned if planned. |
| 7. Septal work (if needed) | Deviation corrected with the L-strut preserved; airway assessed. |
| 8. Bridge | Dorsum built with carved or diced cartilage (or selected implant); hump softened conservatively in strong-profile noses; spreader support placed. |
| 9. Tip support | Septal extension graft or strut placed; tip cartilages sutured to it at the planned projection and rotation. |
| 10. Tip definition | Dome sutures and tip / shield graft to push definition through thick skin; cartilage preserved, not trimmed. |
| 11. Width and base | Conservative osteotomies only if still needed after augmentation; alar base reduced in millimetres to the patient’s own proportion. |
| 12. Closure, splint and observation | Incisions closed with fine sutures; internal splints if septal work done; external tapes and splint applied; donor site dressed; monitored recovery, day-care or overnight. |
Surgical elements and devices
| Element / device | Possible role | Important consideration |
|---|---|---|
| Septal cartilage | Extension graft, strut, spreader grafts | Often smaller in Asian noses — plan for ear / rib. |
| Ear (conchal) cartilage | Tip grafts, DC-F filler, small dorsal onlay | Hidden post-auricular incision. |
| Rib (costal) cartilage | Major dorsal augmentation, revision rebuild | Carved from the central core to limit warping; chest incision. |
| Temporalis fascia | Wrap for diced cartilage; edge camouflage | Small additional donor site. |
| Silicone / ePTFE implant (selected) | Dorsal augmentation in thick-skinned noses | Kept off the tip; snug midline pocket. |
| Permanent fine sutures | Graft fixation, dome shaping | Placement decides projection and definition. |
| Osteotomes (conventional / piezoelectric) | Conservative bone narrowing where needed | Used less often in ethnic noses than in reduction. |
| Internal silicone splints | Support septum if septal work done | Removed at first follow-up. |
| External splint and tapes | Hold bridge and tip position; compress supratip | Night taping may continue for weeks in thick skin. |
Sources: PubMed 35365029 · PMC4656157 · PMC4174207
When Will I See Final Ethnic Rhinoplasty Results?
The new bridge and profile are visible when the splint comes off at about a week, but thick skin holds swelling for longer than thin skin — especially over the tip and supratip. A clearer sense of the new nose emerges at 2–3 months, definition improves through 6–9 months, and the final result in thick-skinned, grafted noses is judged at 12 months, sometimes 18. Judge the nose late, not early.
| Time | What you may notice |
|---|---|
| First few days | Splint on, mild-to-moderate bruising, blocked feeling; donor site sore if ear or rib used. Do not judge the result at this stage. |
| 1 week | Splint and sutures removed. Bridge visibly changed; tip and supratip swollen and rounded. |
| 2–4 weeks | Bruising gone; presentable in public. Nose still fuller than the final result — normal for thick skin. |
| 2–3 months | Bridge close to final; dorsal lines show; tip definition beginning. |
| 6 months | Most of the intended shape visible; supratip settling. |
| 9–12 months | Final result in most patients; nose feels soft and natural. |
| 12–18 months | Final tip definition in very thick-skinned, grafted and revision noses. Revision, if ever considered, waits until here. |
What can affect the final result?
Skin thickness and sebaceous quality above all; how much structural support was built; graft strength, source and take; whether soft-tissue thinning was done; previous surgery or fillers; smoking and nicotine exposure; individual healing and scar response; adherence to taping and follow-up; and weight change or sun exposure during the first year.
Sources: PubMed 17398339 · PMC4174207
What Is the Aftercare After Ethnic Rhinoplasty?
Aftercare after ethnic rhinoplasty centres on protecting the grafts and any implant while they fix in place — no pressure, no knocks, no glasses on the bridge — controlling thick-skin swelling with taping, donor-site care, strict infection prevention, head elevation and no nicotine. These are general principles — your written personal instructions always take priority.
What care is usually advised?
- Keep your head elevated on two pillows for the first week or as instructed.
- Protect the splint and tapes — keep them dry; do not press, adjust or remove them.
- Do not touch, press or “check” the bridge or tip — grafts are held by sutures until scar fixes them.
- Continue night taping for as long as instructed — in thick skin this genuinely speeds settling of the tip and supratip.
- Do not blow your nose for the period advised; sneeze with the mouth open.
- Use saline spray and ointment inside the nostrils as shown; keep incisions clean.
- Care for any donor site — ear: keep the dressing on, sleep on the other side; rib: keep the chest dressing dry, no heavy lifting for 4 weeks.
- Take medicines exactly as prescribed, complete the antibiotic course, and do not restart blood-thinning medicines or supplements without approval.
- Attend all follow-up appointments — splint removal, graft position check, taping review, and — in thick skin — the occasional supratip steroid injection if advised.
What should patients avoid after ethnic rhinoplasty?
| Avoid | Why |
|---|---|
| Glasses resting on the bridge (4–6 weeks, or as advised) | Pressure on a freshly built bridge can dent or shift the graft; tape glasses to the forehead or use contact lenses. |
| Contact sports, crowded transport, playing with small children near the face | A knock can displace grafts or bones before they fix. |
| Smoking, vaping, nicotine in any form | Reduces blood supply to thick skin and grafts; increases infection, resorption and healing problems. |
| Sleeping on your side or face | Pressure can push grafts or bones asymmetric. |
| Strenuous exercise and heavy lifting (2–4 weeks; longer with rib harvest) | Raises blood pressure and swelling. |
| Swimming, steam, sauna, hot yoga (4 weeks) | Heat and moisture increase thick-skin swelling; infection risk. |
| Direct sun on the nose | Worsens swelling and can darken the columellar and alar base scars in pigmented skin. |
| Facials, extractions, harsh skincare on the nose (6 weeks) | Traction and inflammation over healing soft tissue. |
| Unapproved medicines or supplements | Some affect bleeding or healing — check every product with your surgeon. |
| Judging your result in the first months | Thick-skin swelling hides the framework for longer than thin skin. |
Full aftercare detail:
Rhinoplasty recovery timeline
What Are the Risks and Complications of Ethnic Rhinoplasty?
Ethnic rhinoplasty is generally safe for an appropriately selected patient operated on by a trained plastic surgeon in an equipped facility, but it is structural surgery that usually adds material — and augmentation and implant-related risks are the most relevant safety issues on this page. Expected postoperative effects must be separated from true complications — and no surgeon can eliminate risk.
Common / expected early effects (normal healing, not complications): prolonged tip and supratip swelling in thick skin; bruising; a blocked, stuffy nose; numbness of the tip; mild aching; donor-site soreness; temporary asymmetry; a rounded supratip that settles slowly.
Uncommon complications: infection of graft or implant; graft or implant visibility; implant displacement; graft warping (rib); graft resorption with loss of height; prolonged swelling or a true polly-beak in thick skin; asymmetry; alar-base scarring, notching or asymmetry when nostril reduction is added; under-correction (thick skin hides the change); donor-site problems; prolonged numbness; dissatisfaction leading to a revision request.
Rare but important: implant extrusion; over-projection or over-rotation producing an artificial, Westernised look; skin compromise after aggressive soft-tissue thinning, most strongly associated with nicotine; pinched tip or valve collapse if cartilage was over-resected; pneumothorax during rib harvest; anaesthesia-related complications.
Augmentation- and implant-specific risks
- Implant infection: may require treatment or removal.
- Extrusion: implant may become exposed or threaten skin.
- Displacement: implant or graft may shift.
- Warping: mainly relevant to rib cartilage.
- Donor-site morbidity: rib or ear cartilage creates a second healing area.
- Over-projection: can make the nose look artificial.
- Alar-base scarring: relevant when nostril reduction is added.
How risk is minimised
| Risk area | How we work to minimise it |
|---|---|
| Westernised / operated look | Identity-preservation plan agreed in writing — what changes AND what stays; template requests declined. |
| Over-resection under thick skin | Support-first techniques; cartilage added, not removed; generous rims preserved. |
| Implant infection / extrusion | Implants only in suitable thick-skinned noses; never extended to the tip; snug midline pocket; sterile handling; full antibiotic course. |
| Rib graft warping | Central-core carving, balanced cross-sections, dicing where appropriate, fixation. |
| Thick-skin swelling / polly-beak | Conservative soft-tissue management; taping protocol; selective supratip steroid injection. |
| Alar base notching / dark scars | Millimetre planning; incision in the crease; tension-free closure; silicone scar care and sun protection for pigmented skin. |
| Undetected medical risk | Preoperative medical evaluation, investigations and anaesthetic review before scheduling. |
| Nicotine-related healing failure | A clear, enforced nicotine cessation requirement before and after surgery. |
| Bleeding | Medication and supplement review, blood-pressure control, meticulous haemostasis. |
| Infection | Sterile technique, theatre sterilisation protocols, perioperative antibiotics, wound-care instruction. |
| Facility and equipment risk | Surgery at an NABH-accredited surgical centre with appropriate equipment. |
| Delayed recognition of a problem | Structured postoperative observation, written warning signs, accessible follow-up — including for overseas patients by WhatsApp. |
🩺 Dr. Doshi’s Note —
“The noses I revise from elsewhere are rarely under-done. They are over-done — narrowed, lifted and sharpened to a template that was never meant for an Indian face, and now they look operated and breathe worse. Rebuilding them takes rib cartilage and a year. I would far rather say no to a template at the first consultation than rebuild the nose at the fourth.”
⚠️ When to seek urgent medical attention
Seek urgent advice or immediate emergency care for: severe pain · heavy bleeding · spreading redness or warmth over the bridge · fever · pus or discharge · any implant edge becoming visible · sudden breathing difficulty · rapidly increasing swelling · chest pain or breathlessness after rib harvest · after any nasal filler: blanching, colour change, severe pain, eye pain or any vision symptom.
In an emergency, go to the nearest emergency department or call emergency services. Do not wait for a WhatsApp or email reply.
Full risk guide: Rhinoplasty risks and safety
Sources: PubMed 35365029 · PubMed 36041000
What Is the Ethnic Rhinoplasty Recovery Timeline?
Recovery after ethnic rhinoplasty is gradual and, because of thick skin, longer in its final phase than a thin-skinned reduction. Bruising clears over 2 weeks; the splint comes off at about a week; most patients return to desk work within 7–10 days; social recovery improves over 2–3 weeks. The framework is stable at 6 weeks, but definition keeps emerging through thick skin for 12 months or more. Recovery depends on whether the procedure includes augmentation, grafting, alar-base work, septal correction or revision planning. This is a summary — for detailed day-by-day guidance, see the rhinoplasty recovery timeline.
| Timepoint | What typically happens |
|---|---|
| First 24–48 hours | Splint and tapes in place; swelling, some bruising, blocked nose, mild aching; donor site sore if used. Rest head-elevated; day-care discharge or overnight observation. |
| Days 3–7 | Swelling begins reducing. Saline spray and ointment routine. Splint and sutures removed at the first follow-up around day 7. |
| Weeks 2–3 | Bruising gone; presentable in public; many patients return to desk work. Night taping continues. Nose still full — normal for thick skin. |
| Weeks 4–6 | Framework stable; glasses, gentle exercise and travel usually cleared at review. Bridge and dorsal lines show; tip still settling. |
| 3–6 months | Definition emerging; supratip fullness softening. Selective steroid injection if swelling is stubborn. |
| 9–12 months | Final shape in most patients. |
| 12–18 months | Final tip definition in very thick-skinned, grafted and revision noses. Revision assessment waits until here. |
Key recovery points: downtime is about a week; settling in thick skin is about a year · the nose will look fuller than expected for months — this is swelling over a built framework, not a failed result · night taping genuinely helps in thick skin · glasses stay off the bridge for 4–6 weeks · flying requires written clearance at follow-up — overseas patients usually stay in Mumbai 7–10 days and are followed by WhatsApp thereafter · do not book non-refundable travel around an assumed date.
Do not use another patient’s timeline as permission for glasses, exercise, travel or restarting medication.
🩺 Dr. Doshi’s Note —
“My overseas patients always ask the same question at week two, from the airport: ‘Is it supposed to still look this swollen?’ It is. Thick Indian skin gives up its swelling slowly — the bridge first, then the tip, and the tip takes a year. I tell them to send me a photograph every month, and by the sixth one they have stopped asking.”
Medical Codes for Ethnic Rhinoplasty
Codes below are for administrative and documentation reference. All codes must be verified against the current CPT and ICD-10 code sets before publication and before any use in documentation.
| CPT Code | CPT Description | ICD-10 |
|---|---|---|
| 30410 | Rhinoplasty, primary; complete, external parts including bony pyramid, lateral and alar cartilages, and/or elevation of nasal tip | Z41.1 (cosmetic) · M95.0 (acquired deformity of nose) |
| 30400 | Rhinoplasty, primary; lateral and alar cartilages and/or elevation of nasal tip (tip-focused ethnic cases) | Z41.1 · M95.0 |
| 30420 | Rhinoplasty, primary; including major septal repair (ethnic septorhinoplasty) | J34.2 · M95.0 |
| 30435 / 30450 | Rhinoplasty, secondary; intermediate / major revision (revision ethnic cases) | M95.0 · Z98.890 |
| 20910 / 21235 / 20912 | Cartilage graft harvest — costochondral / ear / nasal septum | — |
| 20926 | Tissue grafts, other (fascia) — for diced cartilage in fascia | — |
(FAQs) Frequently Asked Questions About Ethnic Rhinoplasty
Q1. Can ethnic rhinoplasty fail or need revision?
Ans. Yes. Under-correction hidden by thick skin, prolonged supratip fullness, graft warping or resorption, implant problems, or — from elsewhere — a Westernised, over-reduced nose can all lead to revision. Rebuilding an over-reduced ethnic nose is the most demanding revision and usually needs rib cartilage. Revision is assessed only after 12 months, longer in thick skin.
Q2. Is ethnic rhinoplasty safe in India?
Ans. It is generally safe for an appropriately selected patient when performed by a qualified plastic surgeon in an accredited facility with proper anaesthetic support. Recognised risks remain — infection, graft problems, prolonged swelling. Judge the surgeon’s qualification, rhinoplasty volume on noses like yours, and the facility’s accreditation, not the country; Indian surgeons see thick-skinned, low-bridged noses every day.
Q3. How long does ethnic rhinoplasty surgery take?
Ans. Usually 2–3.5 hours; longer with rib cartilage harvest, alar base work or septal correction. The planned duration is confirmed only after examination and surgical planning.
Q4. Is cartilage better than an implant?
Ans. Both have roles. Autologous cartilage avoids implant extrusion risk but may require a donor site. Implants can offer predictable dorsal shape but carry infection, extrusion, displacement and revision concerns. Dr. Doshi’s first preference is usually the patient’s own cartilage when structural support is needed; the choice is personalised.
Q5. Can ethnic rhinoplasty correct a broad nose?
Ans. Yes, if a broad nose is part of the concern — and often the first step is raising the bridge rather than narrowing the bones. Detailed broad-nose planning is on the broad nose correction page, because width can come from the bridge, midvault, tip, base or low dorsum.
Q6. Can ethnic rhinoplasty correct wide nostrils?
Ans. Yes, when alar-base width or flare is part of the surgical plan — reduced in millimetres to your own facial proportion, not a Western ratio. Wide nostril correction has its own scar, notching and symmetry considerations, so detailed alar-base guidance is on that page.
Q7. Will my nose look “done” to other Indians?
Ans. Not if identity is preserved. The tell-tale signs of an operated Indian nose are an over-narrowed bridge, an over-lifted tip and nostrils reduced to a Western ratio — each of which is deliberately avoided. Family typically say you look well or balanced; they rarely identify the nose.
Q8. I live abroad — how does consultation and follow-up work?
Ans. Many ethnic rhinoplasty patients are NRIs or overseas. A WhatsApp photo pre-check gives preliminary guidance; the in-person consultation and surgery are scheduled together, with a stay in Mumbai of about 7–10 days until the splint is off; follow-up thereafter is by monthly photographs and video call. Cartilage is usually preferred over implants for patients who cannot return easily.
Q9. What should I bring to consultation?
Ans. Bring clear front, side, oblique and base-view photographs if possible, and family photographs if you want the result to sit naturally among relatives. Also bring examples of what you like and dislike, but use them as communication tools, not as templates. The final plan comes from your anatomy and goals — and from what you want kept.
Q10. When can I fly after ethnic rhinoplasty?
Ans. Only after written clearance at a follow-up review, usually once the splint is off and graft position is confirmed — about 7–10 days, longer with rib harvest. Do not book non-refundable travel around an assumed date.
Q11. Does insurance cover ethnic rhinoplasty?
Ans. Cosmetic rhinoplasty should not be assumed to be covered by health insurance. Coverage, where it exists at all, applies only to documented functional indications — for example a deviated septum with obstruction corrected in the same operation — and must be confirmed directly with your insurer before surgery.

