
Nasal Tip Plasty in Mumbai: A Refined, Supported, Natural Nasal Tip

Indian Board Certified Plastic Surgeon
M.CH, MS, ISAPS Mentor
16000+ Cosmetic Surgeries
1500+ Rhinoplasty Surgeries
Nasal tip plasty is a focused rhinoplasty procedure for the lower third of the nose — tip projection, rotation, definition, symmetry and support — when the bridge and upper nose are already acceptable. It is smaller in area than full rhinoplasty, but not casual surgery: the nasal tip influences facial balance, nostril shape and the external nasal valve, and a few millimetres change the whole expression of the face. Dr. Milan Doshi plans tip plasty around support, skin thickness and breathing first, so the result looks refined, stable and natural — not pinched, over-lifted, or disconnected from the rest of the nose.
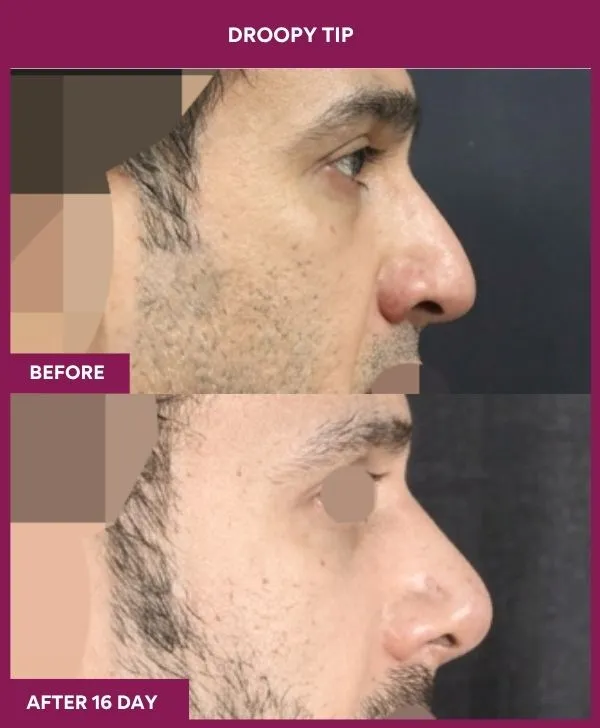
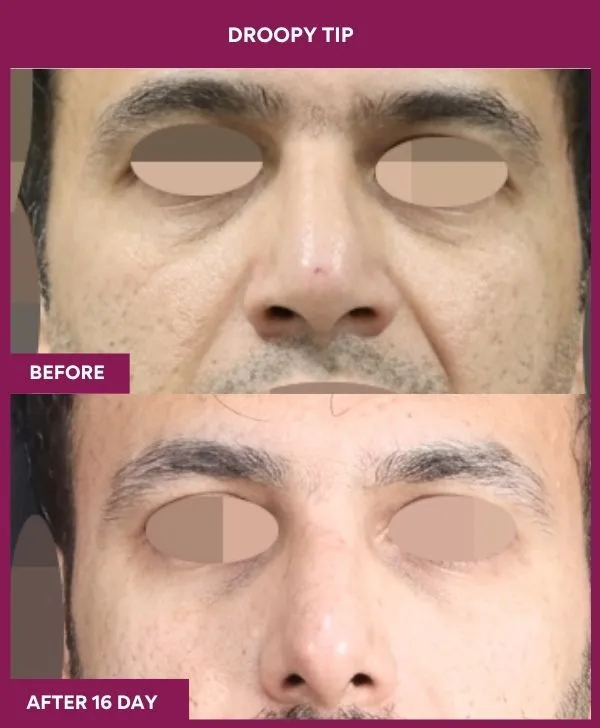
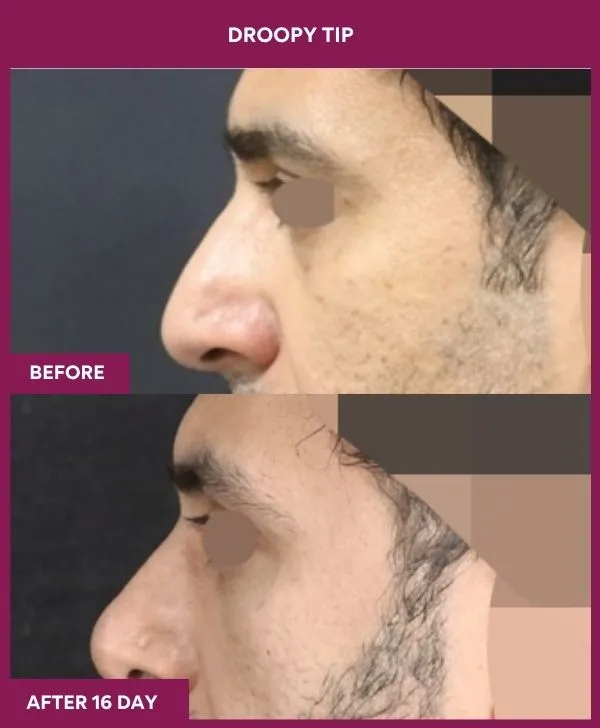
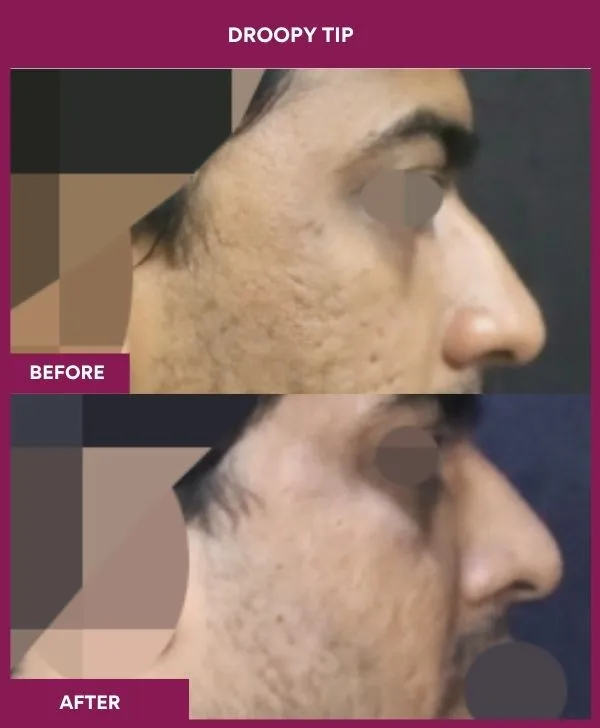
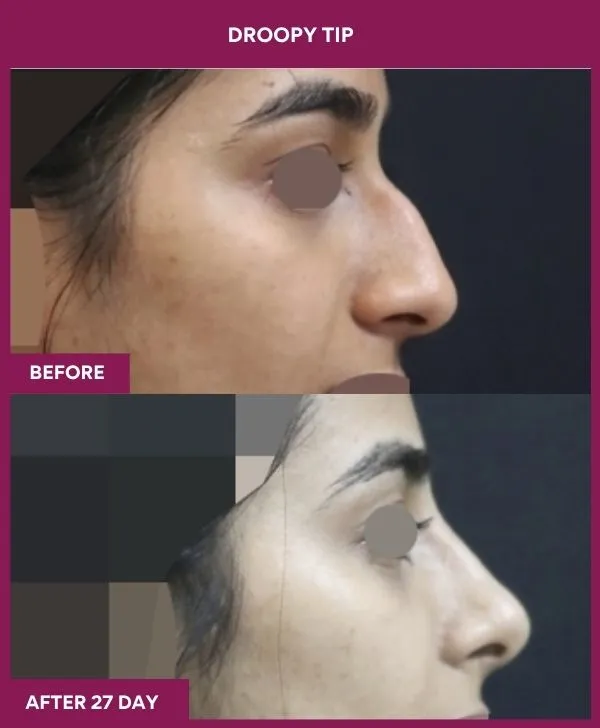
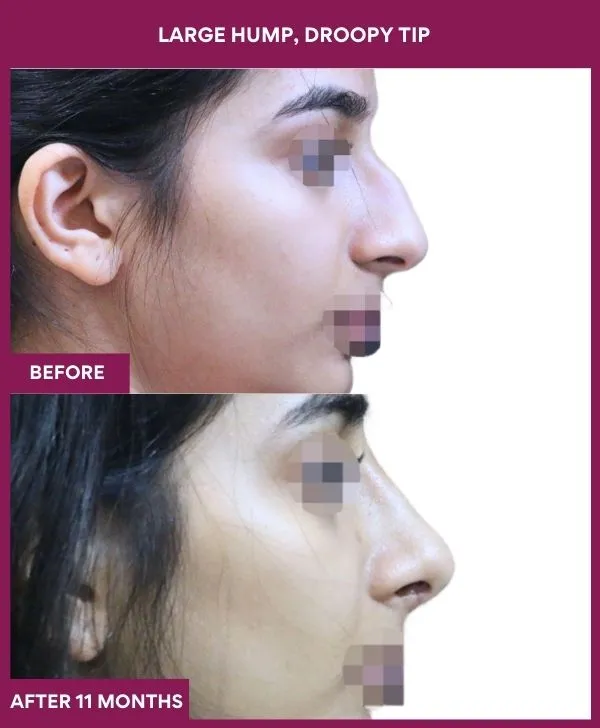
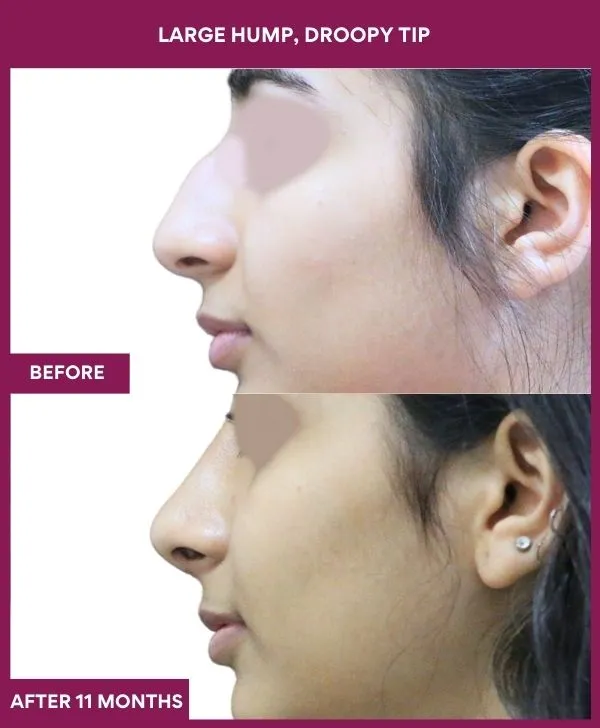
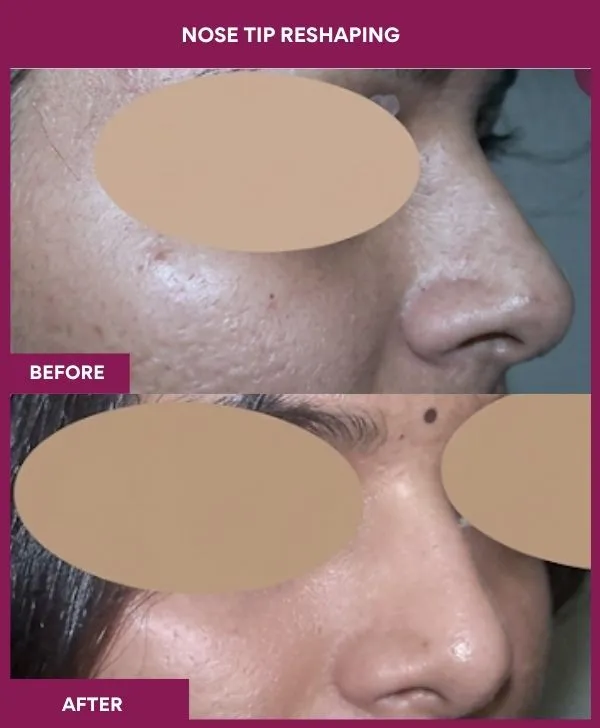
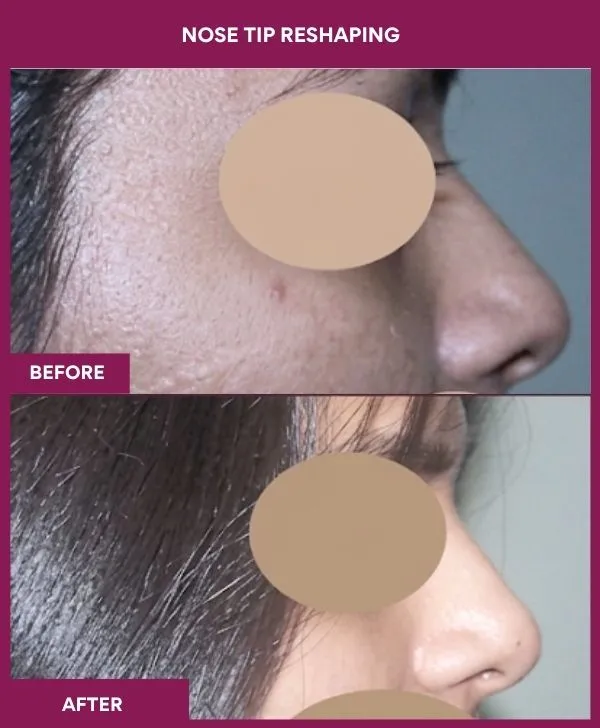
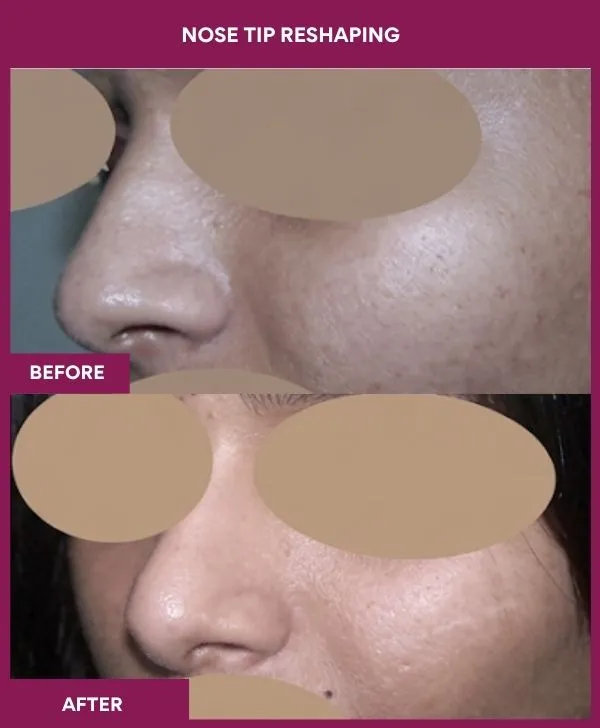
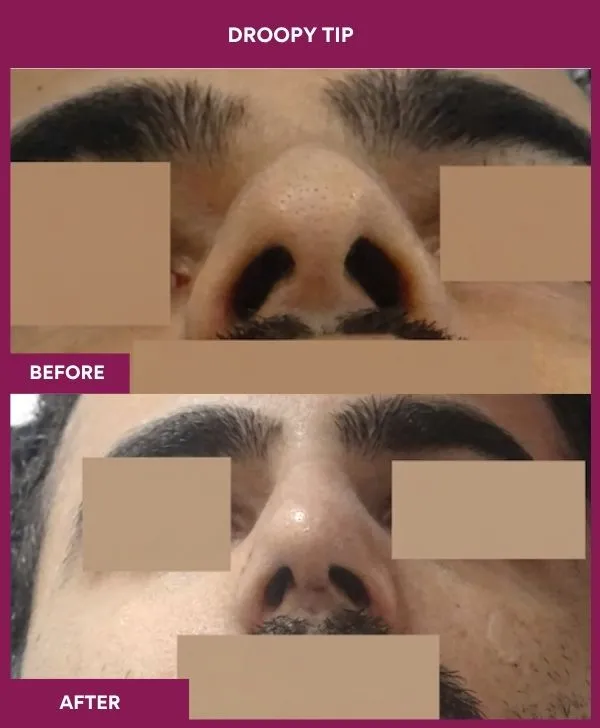
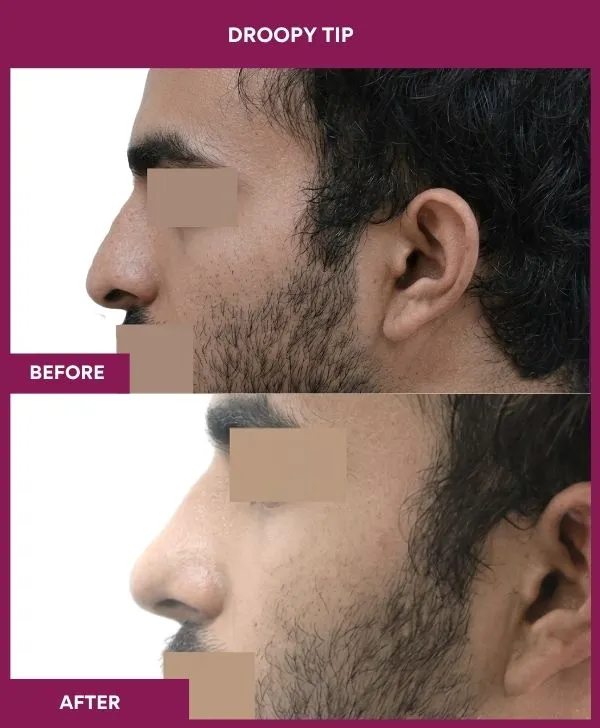
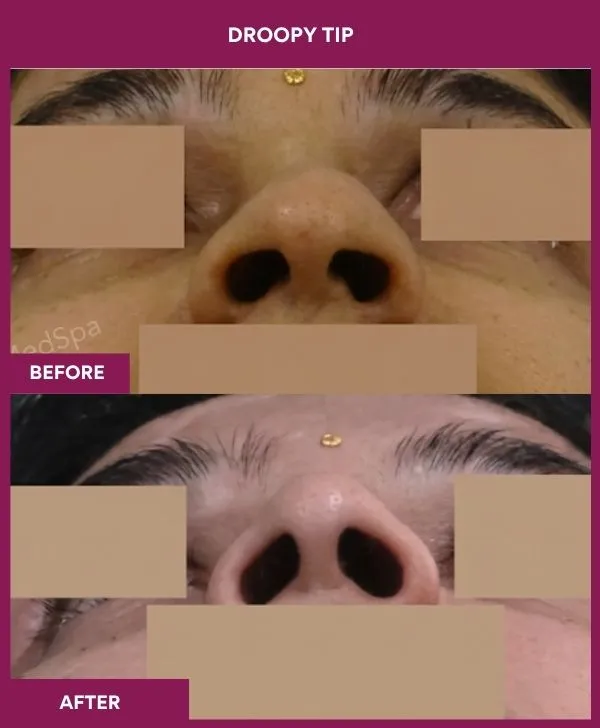
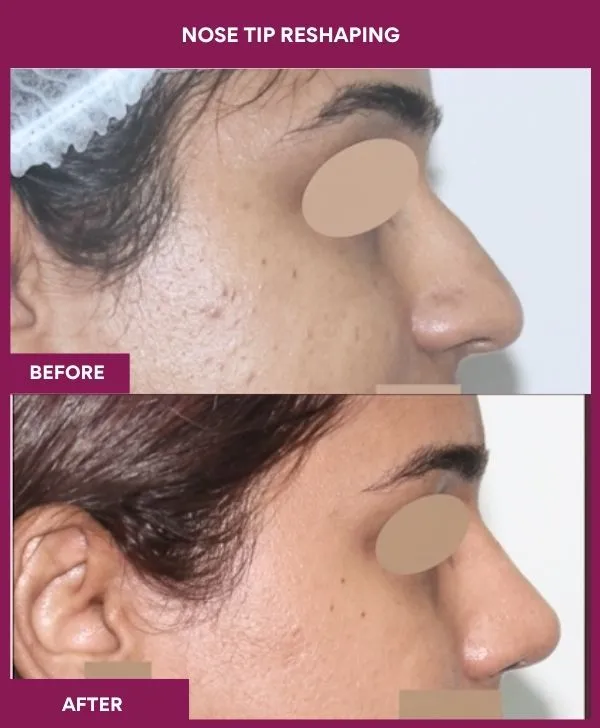
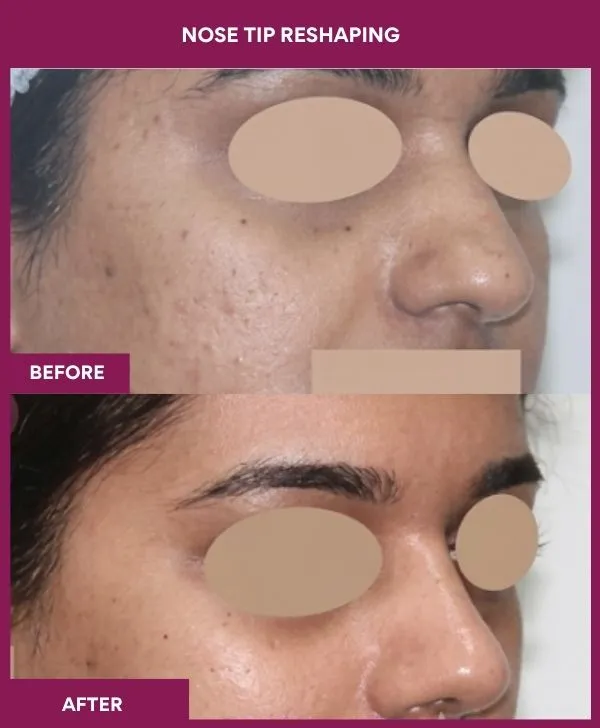
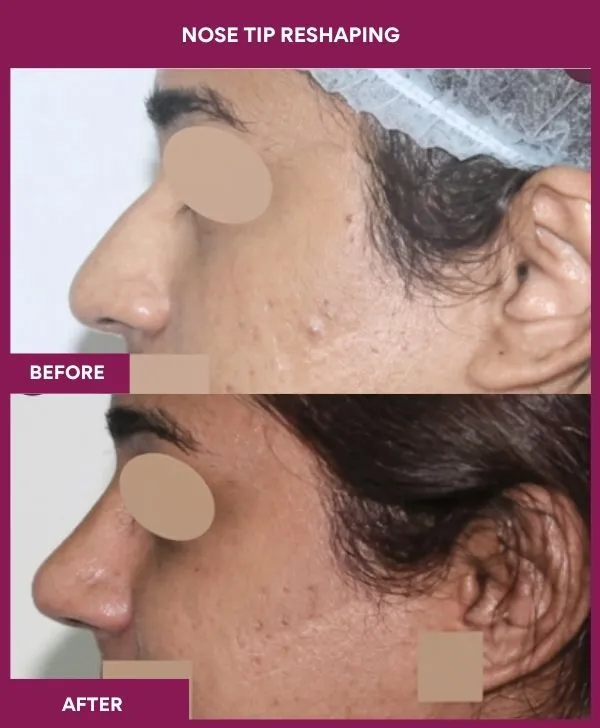
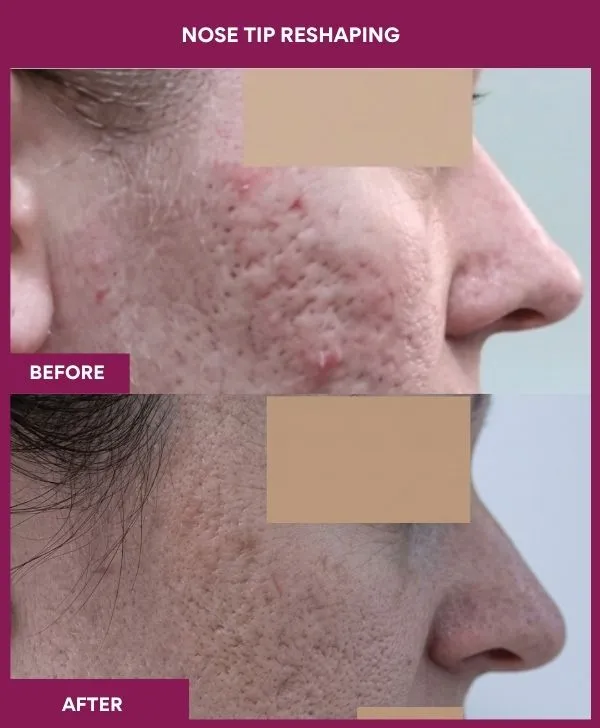
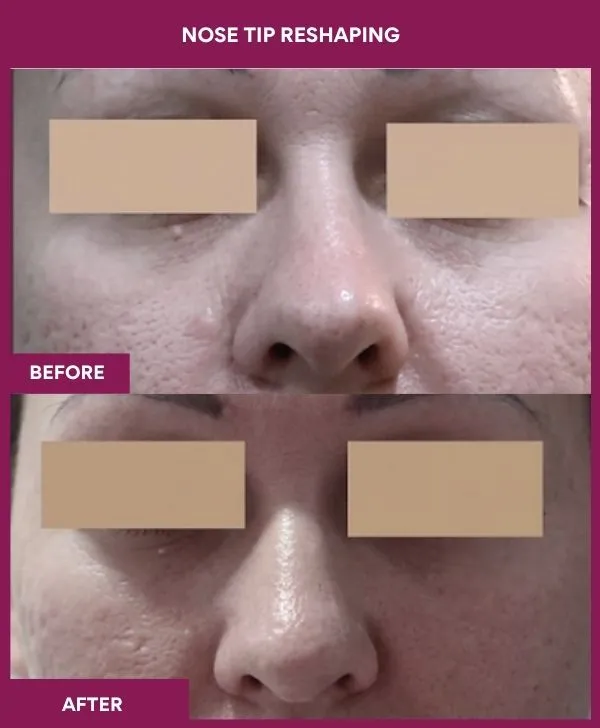
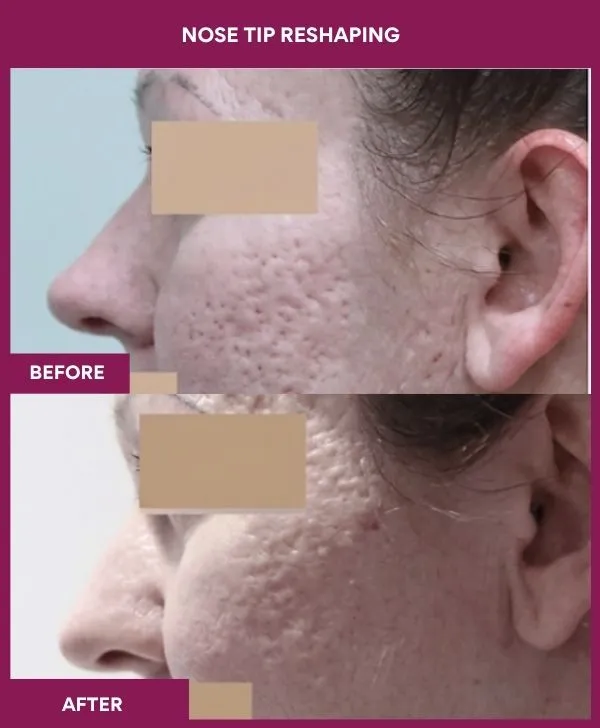
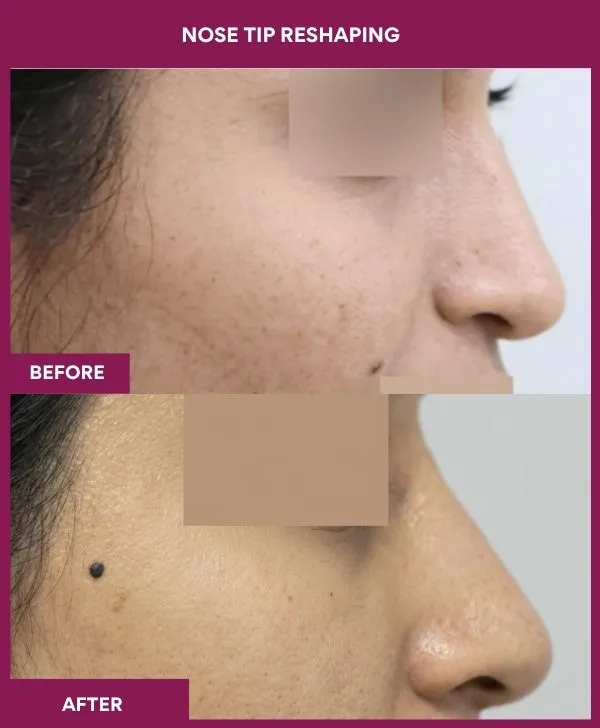
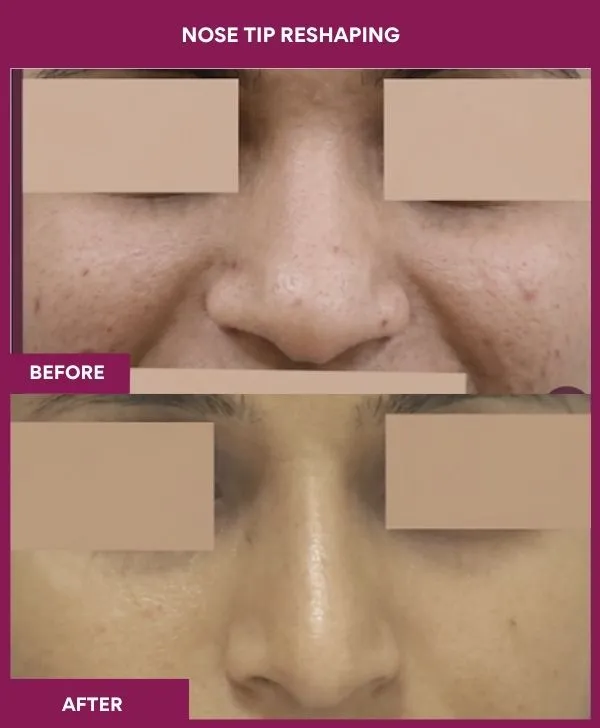
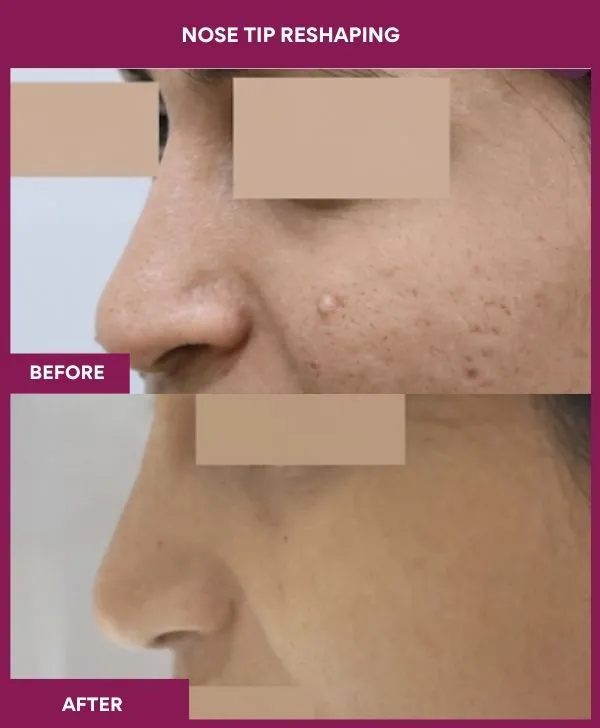
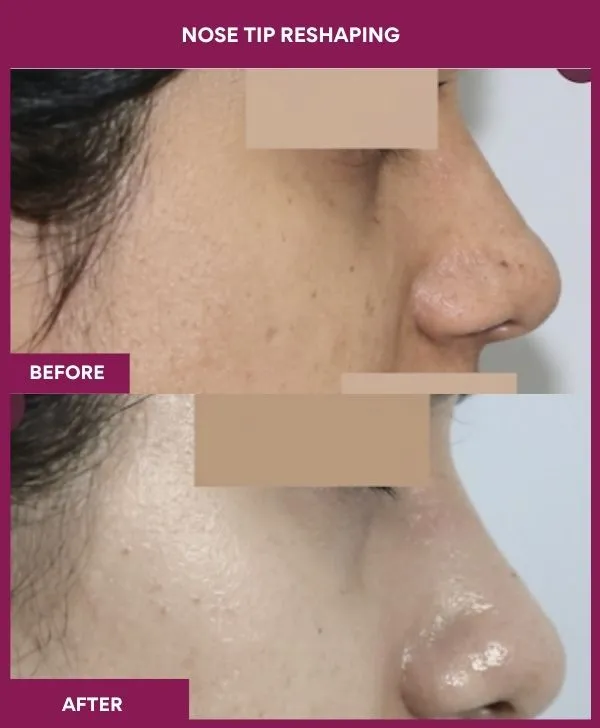
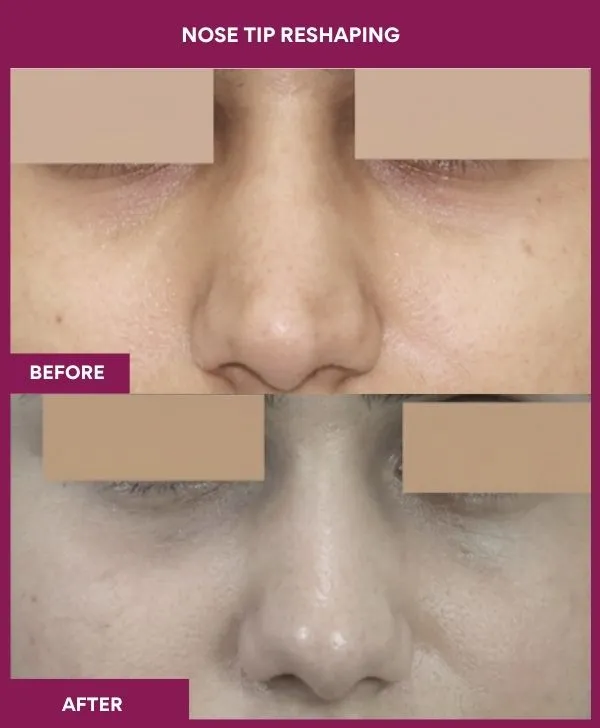
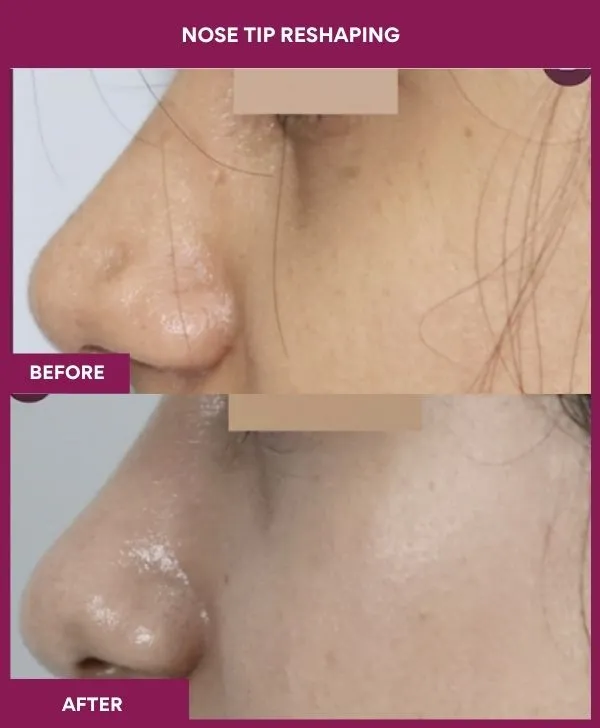
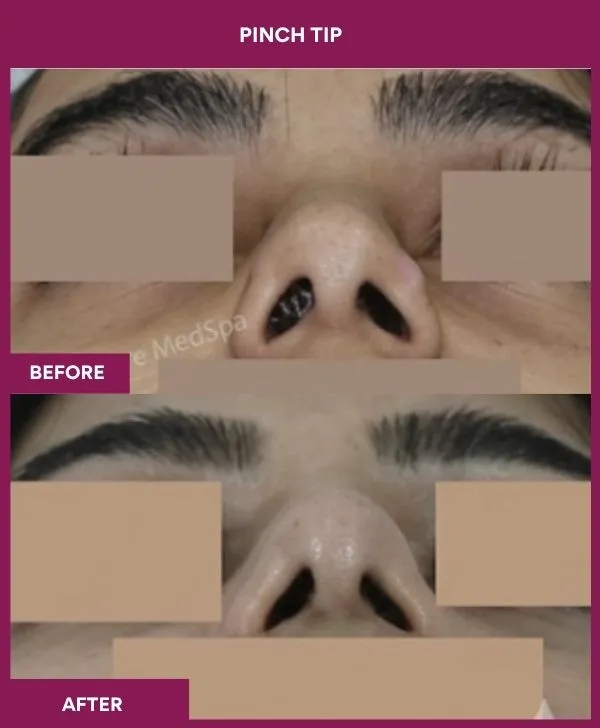
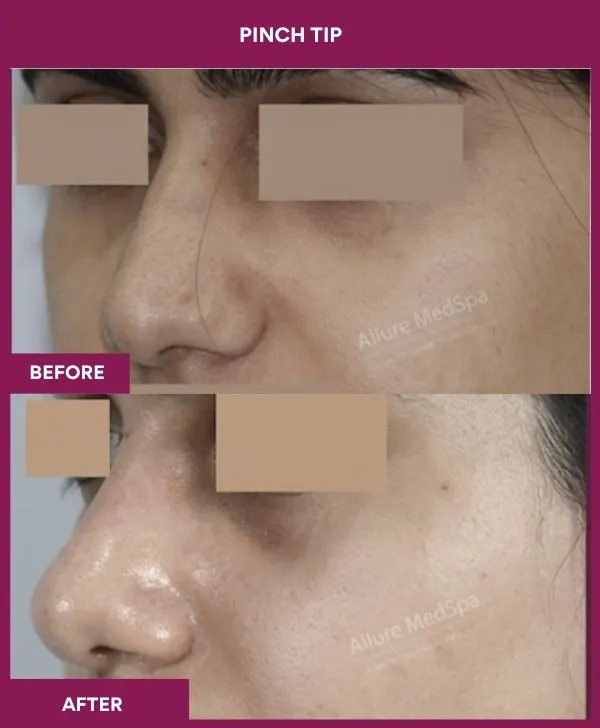
Nasal Tip Plasty Before And After Images
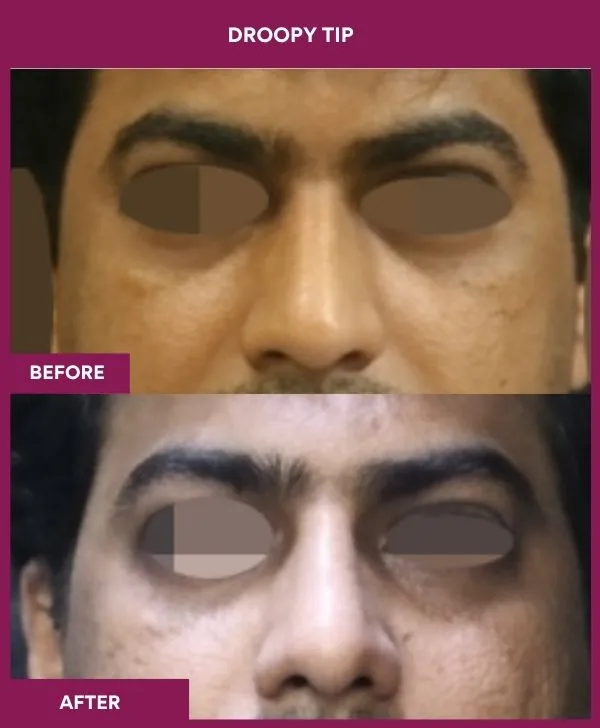
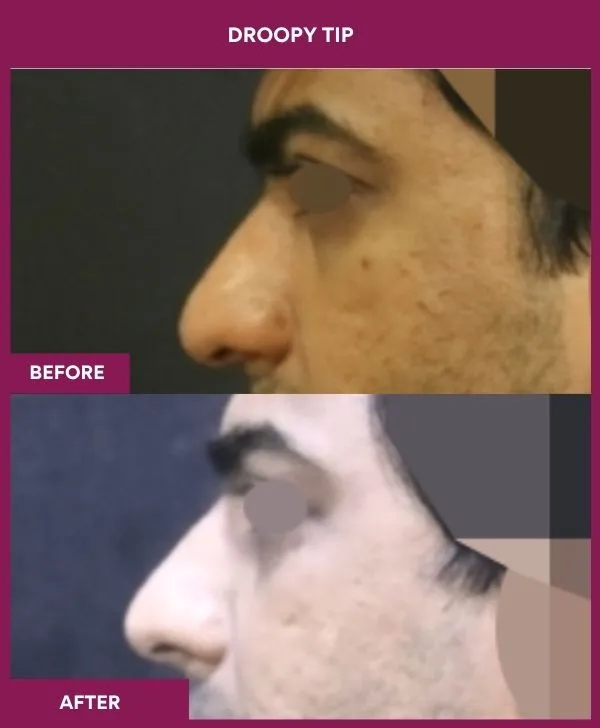
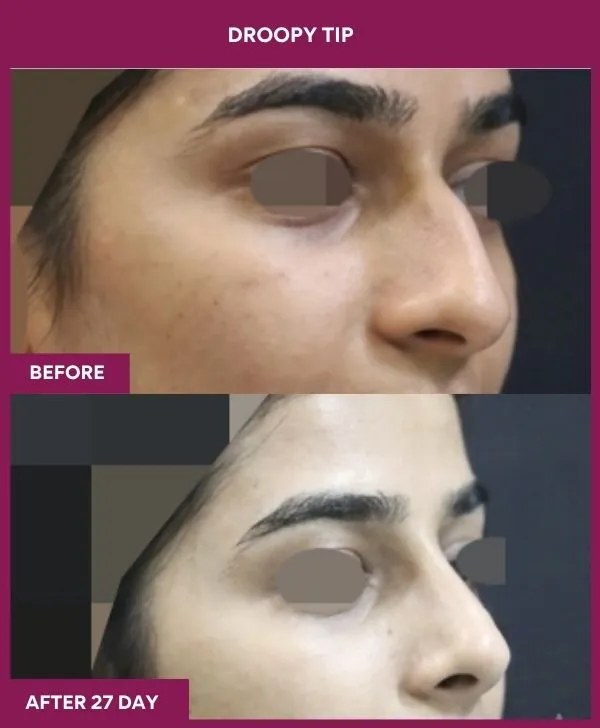
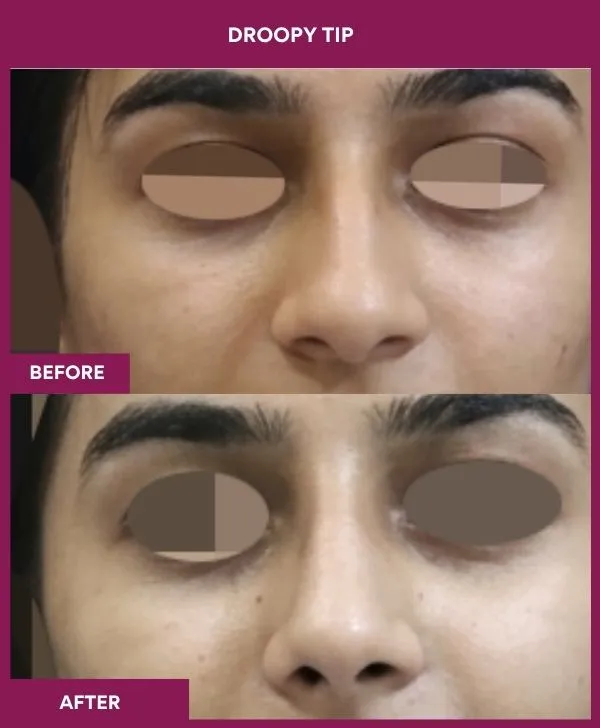


Rhinoplasty Surgery Testimonials: Celebrities Patient

Awarded by Google.com
Rating: 4.7
Reviews: 485+

Awarded by WhatClinic.com
Rating: 4.8
Reviews: 119+

Awarded by Realself
Rating: 4.9
Reviews:453+

Awarded by Facebook
Rating: 4.6
Reviews:105+
Dr Milan Doshi and his staff are very professional and committed as the centre is highly equipped with advanced technology. I had closed rhinoplasty 4 months back and I’m seeing the results as to how it becomes successful.
Deepika Shetty
The doctor explained everything clearly and the surgery was smooth. Recovery was faster than I expected and the team was very supportive.
Rahul Mehta
Very natural results and excellent staff. From consultation to follow-up, the experience was outstanding and boosted my confidence.
Sneha Kapoor
Video: Best Rhinoplasty Surgeon explain nose reshape procedure
Dr Milan Doshi is describing the Rhinoplasty Surgery in detail with benefits, techniques, recovery, result, risk and complecations
Am I a Candidate?
(4 quick questions)
Quick Facts About Nasal Tip Plasty
TIME REQUIRED
1.5–2.5 hours
ANESTHESIA
General
HOSPITAL STAY
Day-care or 1 night
PAIN LEVEL
Mild–moderate
BACK TO WORK
7–10 days
RESULTS LAST
Permanent
SUCCESS RATE
97–98%
COMPLICATIONS
Under 2-3%
How Much Does Nasal Tip Plasty Cost in Mumbai?
Nasal tip plasty cost in Mumbai at Allure Medspa is a guide range of ₹70,000 to ₹1,80,000, with 5% GST extra. This is a guide range, not a quote — final cost is confirmed only after consultation, because technique, open versus closed approach, grafting, anaesthesia, facility, and whether full rhinoplasty is required can change the estimate. The table shows where different tip corrections typically fall within the range.
| Scope of tip plasty | Typical range (₹) | What it usually involves |
|---|---|---|
| Closed suture-only refinement | 70,000 – 1,00,000 | Transdomal / interdomal sutures, minimal cephalic trim; boxy or mildly broad tip; day-care |
| Open tip refinement | 90,000 – 1,30,000 | Open approach for exposure; sutures + controlled trim; boxy, mildly asymmetric or over-projected tip |
| Support-based tip plasty | 1,10,000 – 1,50,000 | Columellar strut, tip graft, septal extension or tongue-in-groove; droopy, flat or ageing tip |
| Structural / reconstructive tip work | 1,30,000 – 1,80,000 | Lateral crural strut or alar grafts, ear-cartilage harvest; pinched or asymmetric tip, previous filler |
| Pinched tip after previous surgery | See revision page | Classified as revision rhinoplasty |
| Tip + bridge / septum / nostril base | See rhinoplasty cost | No longer tip plasty — full rhinoplasty or septorhinoplasty range applies |
Get your exact quote & surgery plan
Share your details — our team responds within working hours with cost, EMI options and next steps.
Most Common Question People Ask
Q1. What is nasal tip plasty?
Ans. Nasal tip plasty is a focused rhinoplasty procedure that reshapes the lower third of the nose. It can refine projection, rotation, definition, and symmetry, but it does not correct major bridge, septal, midvault, or nasal bone issues unless combined with full rhinoplasty.
Q2. Is nasal tip plasty enough for my nose?
Ans. It may be enough if the bridge, septum, nasal bones, and breathing are acceptable and the main concern is the tip. If you also have a hump, crooked nose, deviated septum, or wide bridge, full rhinoplasty may be more suitable.
Q3. When should I choose full rhinoplasty instead?
Ans. Choose full rhinoplasty when the bridge, nasal bones, septum, midvault, nostril base, or breathing function also need correction. Tip-only surgery is the wrong shortcut when the problem is not limited to the tip.
Q4. How long is recovery after nasal tip plasty?
Ans. Many patients resume daily activity in about 7–10 days, but the tip can remain swollen for weeks to months. Thick skin may take longer to show final definition. See the recovery guide for full aftercare.
Q5. What is the cost of nasal tip plasty in Mumbai?
Ans. The guide range is ₹70,000–₹1,80,000 with 5% GST extra. Final cost depends on technique, approach, grafting, complexity, and whether full rhinoplasty is needed.
Q6. Will nasal tip plasty leave scars?
Ans. Closed nasal tip plasty uses internal incisions. Open nasal tip plasty may leave a small columellar scar. The best approach depends on deformity complexity, exposure needed, and surgeon preference.
Q7. Why is bulbous tip not explained fully here?
Ans. Bulbous tip correction has its own dedicated page because it is a common, broad topic involving thick skin, wide domes, and cartilage definition. Read the dedicated bulbous tip correction guide for the full detail.

Why Choose Dr. Milan Doshi?
Dr. Milan Doshi, MCh, MS — Indian board-certified plastic and cosmetic surgeon with 27+ years of experience, 16,000+ surgeries, and 1,500+ rhinoplasties. Nasal tip plasty requires a surgeon who can refine a small area without weakening the nose, over-narrowing the tip, or compromising breathing: refinement must not weaken support; the external valve must be protected; the tip must match bridge, lips, chin and face; thick skin needs realistic planning; male and female tip goals differ; natural identity should be preserved; and over-resection is a costly mistake. ISAPS, IAAPS and MUHS; consults at Andheri West; surgeries at the NABH-accredited surgical centre, Goregaon West.
The Complete Guide About Nasal Tip Plasty
What Is Nasal Tip Plasty?
Nasal tip plasty is a focused rhinoplasty procedure for the lower third of the nose, especially tip projection, rotation, definition, symmetry, and support. It cannot reliably correct bridge, septal, midvault, or breathing problems when those structures are the real cause.
Tip plasty is smaller in area than full rhinoplasty, but not casual surgery. The nasal tip is structurally important because it influences facial balance, nostril shape, tip projection, and the external nasal valve.
Tip plasty may help when the bridge and upper nose are acceptable but the lower third looks heavy, droopy, flat, pinched, over-projecting, or asymmetric. If the bridge, septum, nasal bones, or airway also need correction, full rhinoplasty or septorhinoplasty may be more appropriate.
| Cosmetic tip plasty | Reconstructive / functional tip work |
|---|---|
| Refining a boxy, droopy, flat or over-projected tip for appearance | Rebuilding a pinched or collapsed tip after previous surgery, trauma or filler; restoring external-valve support |
| Sutures, conservative trim, small support grafts | Lateral crural struts, alar grafts, ear or septal cartilage; often classified as revision |
| Not covered by insurance | Functional component may be documented for insurance; cosmetic portion is not |
Also called: tip rhinoplasty · tip plasty · nose tip surgery · nasal tip refinement · tip-only rhinoplasty · lower-third rhinoplasty.
Sources: NCBI – Nasal Tip Surgery (StatPearls)
“Tip plasty may sound like a small procedure, but the nasal tip is one of the most judgment-sensitive parts of rhinoplasty. A few millimetres can change the whole expression of the face. In my practice, I do not plan tip plasty only to make the tip smaller or sharper. I first assess tip support, skin thickness, cartilage strength, nostril shape, projection, rotation, and breathing. The right tip should look refined, stable, and natural — not pinched, over-lifted, or disconnected from the rest of the nose.”
Does Your Nasal Tip Look Heavy, Droopy, Square Or Uneven?
You may like your profile and your bridge, and still avoid photographs from the front or from below because the tip looks heavy, round, flat or slightly off-centre. You may have noticed the tip dips when you smile, or that make-up and lighting cannot hide a square edge. And you may have been told — or read online — that you need a “full nose job” when the only thing that bothers you is the tip.
You may be thinking: “Can only the tip be done?”, “Will it look pinched or fake?”, “My skin is thick — will anything even show?”, or “Is filler the easier answer?”
The answer depends on where the problem actually is. A tip that looks wrong because the bridge is low, the nostrils are wide, or the septum is deviated will not be fixed by tip-only surgery. A tip that is truly the only concern can be refined on its own, with a faster recovery and no change to the rest of the nose.
What Are The Benefits Of Nasal Tip Plasty?
Nasal tip plasty can improve the shape, definition, support, symmetry and projection of the nasal tip without changing the parts of the nose you already like. Because it usually focuses only on the lower third of the nose and often avoids nasal bone work, recovery may be shorter with less bruising than a full rhinoplasty.
- Targeted change: only the lower third is altered; the bridge, profile and identity you already like are untouched.
- Refined definition: a boxy, round or broad tip becomes softly defined — not sharp.
- Better support and rotation: a droopy or flat tip is lifted and projected by rebuilding support, so it stays stable when you smile and as you age.
- Symmetry improvement: uneven domes and nostril relationships are balanced (improvement, not mirror image).
- Breathing protected — or improved: external-valve support is preserved or rebuilt, which matters most in pinched-tip repair.
- Shorter recovery than full rhinoplasty: no bone work in most cases; daily activity in about 7–10 days.
- Often no bruising under the eyes: because the nasal bones are not touched.
- Frequently closed approach: selected refinements are done through internal incisions with no external scar.
Which Tip Concerns Can Nasal Tip Plasty Address?
Nasal tip plasty can address several lower-third concerns, but each deformity has a different cause and correction strategy. It should not be planned by appearance alone; the surgeon must identify whether the problem comes from cartilage width, weak support, scarring, projection, rotation, or skin thickness.
| Tip concern | What it means | Learn more |
|---|---|---|
| Droopy / ptotic tip | Tip points downward or falls with age/support loss | Drooping tip correction |
| Boxy tip | Tip looks square, broad, or angular | Bulbous & boxy tip correction |
| Bulbous tip | Wide or under-defined tip | Bulbous tip correction |
| Over-projected tip | Tip sticks too far forward | This page — Types section |
| Under-projected / flat tip | Tip looks flat or lacks forward support | This page — Types section · Augmentation |
| Pinched tip | Tip looks over-narrowed and may affect airflow | This page — Types section · Revision |
| Asymmetric tip | Tip shape or nostril relationship looks uneven | This page — Types section · Crooked nose |
How should you understand your nasal tip anatomy?
Nasal tip plasty works on the lower lateral cartilages, medial crura, lateral crura, domes, soft-tissue envelope, and support tripod of the nasal tip. It must preserve support, because weakening the lower-third framework can affect both shape and external nasal valve function.
The nasal tip is formed mainly by the paired lower lateral cartilages, which create the domes, nostril-side support, projection, and rotation. The tripod concept describes how a central support limb and two lateral limbs balance tip position. Visible tip definition depends not only on cartilage shape, but also on skin thickness. Thick skin can hide fine contour changes and make early swelling look heavier — something that matters especially in many South-Asian noses.
| Term | Meaning |
|---|---|
| Lower lateral cartilages | Main cartilage framework of the nasal tip |
| Medial crura | Central support near the columella |
| Lateral crura | Side support arms of tip cartilage |
| Domes | Tip-defining cartilage curves |
| Tripod concept | Support model for projection and rotation |
| Soft-tissue envelope | Skin and tissue covering the tip |
| External nasal valve | Airway zone affected by alar and tip support |
Sources: NCBI – Nasal Tip Surgery (StatPearls)
https://www.ncbi.nlm.nih.gov/books/NBK567750/
What Are The Limitations Of Nasal Tip Plasty?
Nasal tip plasty may be right when the main problem is limited to the nasal tip — drooping, boxiness, poor projection, pinching, or asymmetry. It is not enough when the bridge, septum, nasal bones, nostril base, or breathing function also need correction.
| Concern | More suitable approach |
|---|---|
| Bridge hump | Full rhinoplasty |
| Crooked nose | Crooked nose correction |
| Deviated septum | Septorhinoplasty |
| Broad nasal bones | Full rhinoplasty |
| Major nostril width | Alar (nostril) correction |
| Breathing obstruction | Functional rhinoplasty · Septorhinoplasty |
| Prior unsatisfactory nose surgery | Revision rhinoplasty |
- Perfect mirror-image symmetry is not a realistic surgical promise.
- Thick skin limits how much definition can show on the surface, however well the cartilage is shaped.
- A tip cannot be made “sharp” safely on every nose — over-resection causes pinching and valve narrowing.
- A tip that looks over-projected because the chin is weak may need chin augmentation, not tip reduction.
Why Is A Consultation Essential Before Nasal Tip Plasty?
Because the single most important decision — tip-only or the whole nose — is made here, and it cannot be made from a selfie. Dr. Doshi examines the bridge, septum, bones and nostril base as well as the tip, watches the tip at rest and during smiling, palpates support and skin thickness, and only then says whether tip plasty alone is honest.
What happens
- Examination of the whole nose — bridge, septum, bones, nostril base, tip support, skin thickness; smile analysis for dynamic droop.
- Standardised photographs (front, profile, three-quarter, basal); AI simulation where useful.
- Discussion of the tip type, the change that is possible, and what should NOT be done.
- Technique and approach chosen (closed vs open; sutures, trim, grafts); cost within the guide range confirmed.
- Medical history, medicines, nicotine; pre-op plan.
How to prepare
- Old photographs of your nose, and any previous surgery or filler records.
- A clear sentence of what bothers you — “the tip drops when I smile”, “it looks square from the front”.
- Questions on scars, thick skin, timelines and cost.
- See the full preparation guide → How to Prepare for Rhinoplasty
Online consultation
Outstation and international patients can start with a video consultation and photo review at Online Consultations; see also Outstation Patients. Consultation fee ₹1,500.
Which Surgical Techniques Are Used In Nasal Tip Plasty?
Nasal tip plasty techniques include transdomal sutures, interdomal sutures, controlled cephalic trim, columellar strut, tip grafts, tongue-in-groove fixation, lateral crural work, and open or closed approaches. The technique should match the patient’s exact deformity, skin thickness, cartilage strength, support needs, and facial balance — not follow one standard formula.
| Technique | Main purpose | Commonly used for | Key caution |
|---|---|---|---|
| Transdomal sutures | Refine domes | Boxy, broad, mild asymmetry | Avoid over-narrowing |
| Interdomal sutures | Adjust distance between domes | Boxy or poorly defined tip | Maintain natural contour |
| Cephalic trim | Reduce excess cartilage width | Boxy or broad tip | Over-resection can cause pinching |
| Columellar strut | Improve support | Under-projected, droopy, weak tip | Requires stable cartilage planning |
| Tip graft | Add definition or projection | Flat, under-projected, weak tip | Can show in thin skin |
| Tongue-in-groove | Stabilise rotation/projection | Droopy or under-projected tip | Needs precise support control |
| Lateral crural work | Correct weak/malpositioned cartilage | Pinched, asymmetric, alar contour issues | Protect external valve |
| Open approach | Better exposure | Complex, asymmetric, revision, graft-heavy cases | Small columellar scar |
| Closed approach | Internal incisions | Selected limited tip refinements | Less exposure |
Is the open approach always better for the tip?
No. Open exposure is valuable when the tip is asymmetric, needs grafts, or has been operated on before; a closed approach is often enough for suture-only refinement of a boxy or mildly broad tip and leaves no external scar. The choice follows the diagnosis, not a preference. See open vs closed rhinoplasty.
Sources:
NCBI – Nasal Tip Surgery (StatPearls)
https://www.ncbi.nlm.nih.gov/books/NBK567750/ ·
https://pmc.ncbi.nlm.nih.gov/articles/PMC3901916/
What Are The Types Of Nasal Tip Correction?
Each tip deformity has its own cause, its own correction strategy and its own recovery pattern. The six below are the ones tip plasty most often addresses; bulbous tip has a dedicated page.
Droopy or ptotic tip correction
Droopy tip correction is nasal tip plasty for a tip that points downward, looks heavy, or descends with smiling or ageing. It usually focuses on restoring support and rotation rather than simply removing cartilage or narrowing the tip. It may happen because of weak cartilage support, age-related descent, previous over-resection, trauma, inadequate tip projection, or a dynamic pull from the depressor septi nasi muscle during smiling — so smile analysis becomes important during consultation. A weak tip may need a columellar strut, tip graft, septal extension support, or tongue-in-groove fixation. If there is also a long nose, septal deviation, or bridge issue, tip-only surgery may not be enough.
Recovery nuance: droopy tip correction often involves support-building manoeuvres, so swelling may persist in the tip longer than patients expect. The bridge may look stable earlier, while the tip slowly refines over weeks to months.
“In droopy tip correction, I always check whether the tip is drooping at rest, during smiling, or both. This distinction is important. Some patients have weak structural support, while others have a dynamic pull from the depressor septi nasi muscle during smiling. In such cases, only lifting or narrowing the tip may not solve the real problem. The plan must address support, rotation, smile dynamics, and facial balance together. The aim is not an over-lifted nose, but a naturally supported tip that looks elegant at rest and stable during expression.”
Full guide: Drooping tip correction →
Boxy tip correction
Boxy tip correction is nasal tip plasty for a square, broad, or angular nasal tip caused by wide lower lateral cartilages, weak dome definition, or broad lateral crura. A boxy tip does not always mean the nose is too large — often the problem is shape: the domes are broad, the cartilage is wide, or the tip-defining points are poorly formed, and thick skin can make a refined framework look less defined on the surface. Correction may involve transdomal sutures, interdomal sutures, controlled cephalic trim, and selective grafting. The key word is controlled — over-resection can weaken the cartilage and create a pinched tip or external valve narrowing.
Recovery nuance: boxy tip patients often want quick definition, but the lower third of the nose settles slowly. Thick skin can mask early changes, so early swelling should not be mistaken for surgical failure.
Full guide: Bulbous & boxy tip correction →
Over-projected or “Pinocchio” tip correction
Over-projected tip correction is nasal tip plasty for a tip that extends too far forward from the face. It should rebalance support and projection rather than simply remove cartilage, because aggressive reduction can destabilise the tip or affect breathing. Causes may include strong septal support, long medial crura, excess tip support, prior graft over-projection, or disproportion between the tip and the rest of the nose. Correction may involve adjusting medial crura support, modifying tip cartilage, reducing excessive projection, repositioning support structures, or revising previous grafting. The surgeon must also check the bridge and chin relationship, because sometimes the tip looks over-projected simply because the rest of the face is under-projected.
Recovery nuance: projection changes can look dramatic early because swelling distorts the tip and columella. Final judgement should wait until swelling settles and the tip soft-tissue envelope adapts.
Under-projected or flat tip correction
Under-projected tip correction is nasal tip plasty for a flat, weak, or poorly supported tip that lacks forward projection. It usually requires structural support, such as a columellar strut, tip graft, septal extension graft, or tongue-in-groove stabilisation. In South-Asian noses, under-projection may coexist with thicker skin and weaker visible definition; in revision cases, it may result from previous over-resection or loss of tip support. Simply narrowing the tip will not solve a flat tip and may make the nose look weaker. The surgeon may need septal cartilage, ear cartilage, or other grafting depending on available support and case complexity.
Recovery nuance: support grafts can make the tip look firm or swollen early. Patients should expect the tip to soften and settle over months. Results vary by individual anatomy and healing.
Pinched tip correction
Pinched tip correction is nasal tip plasty or revision rhinoplasty for an overly narrow tip, often caused by excessive cartilage removal, scarring, or weak lower lateral cartilage support. It must protect breathing, because external nasal valve narrowing can worsen airflow. A pinched tip can look sharp, collapsed, unnatural, or operated; patients may notice difficulty breathing during exercise, nostril collapse, or a feeling that the lower nose is too tight. Correction usually requires structural widening or support, not more narrowing — lateral crural strut grafts, alar support grafts, cartilage repositioning, or revision structural rhinoplasty. If the nose has already been operated on, this may be better classified as revision rhinoplasty rather than isolated tip plasty.
Recovery nuance: pinched tip correction is often reconstructive. Swelling, firmness, and gradual softening may take longer than cosmetic narrowing procedures. Breathing improvement should be monitored separately from appearance.
Asymmetric tip correction
Asymmetric tip correction is nasal tip plasty for uneven tip shape, unequal domes, nostril imbalance, trauma-related change, congenital difference, or previous surgery. It can improve symmetry, but perfect mirror-image equality is not a realistic surgical promise. Tip asymmetry may come from different cartilage shapes on each side, unequal soft-tissue thickness, septal deviation, trauma, nostril base difference, or scar tissue after previous rhinoplasty; a crooked-looking tip may also be linked to a crooked bridge or septum, so examination must include the full nose. Correction may involve differential suturing, cartilage reshaping, selective grafting, septal support, or revision rhinoplasty if prior surgery caused the asymmetry.
Recovery nuance: swelling itself can create temporary asymmetry. Early postoperative unevenness does not always equal a bad result, and clinical follow-up is more reliable than daily mirror-checking.
The ageing tip
Nasal tip plasty may help selected ageing-related tip changes when cartilage and soft-tissue support weaken, causing the tip to descend, look longer, or lose definition. With ageing, lower lateral cartilage support may weaken and soft tissue may become less firm; the tip may rotate downward, projection may reduce, and the nose may appear longer even when the bridge has not changed. For ageing, the plan should focus on support restoration rather than aggressive cartilage removal, while preserving airway stability. If the ageing nose also has bridge changes, septal deviation, or valve narrowing, full rhinoplasty or septorhinoplasty may be needed.
Sources: NCBI – Nasal Tip Surgery (StatPearls)
https://www.ncbi.nlm.nih.gov/books/NBK567750/ ·
https://pmc.ncbi.nlm.nih.gov/articles/PMC3901916/ ·
https://pmc.ncbi.nlm.nih.gov/articles/PMC3199839/
How is male vs female nasal tip planning different?
Nasal tip plasty planning differs between male and female faces because rotation, projection, nasolabial angle, strength, and nostril show influence whether the nose appears straighter, softer, shorter, longer, masculine, or feminine. Targets should remain individualised, especially in Indian and ethnic noses.
| Feature | Common male planning | Common female planning |
|---|---|---|
| Nasolabial angle | Often cited around 90–95° | Often cited around 95–105° |
| Tip rotation | Usually less rotated | Often slightly more rotated |
| Projection | Stronger projection may suit | Balanced projection preferred |
| Tip definition | Defined but not pinched | Refined but not sharp |
| Nostril show | Conservative | Balanced |
| Ethnic identity | Preserve | Preserve |
These angle ranges should not be treated as rigid goals. Rotation and projection should be adjusted to facial proportions, age, ethnicity, chin projection, lip relationship, and patient preference.
Is surgery better than non-surgical filler tip refinement?
Nasal tip plasty changes cartilage support and tip structure, while filler only camouflages selected minor contour concerns temporarily. Surgery may suit structural deformity, while filler may suit minor temporary camouflage only when patients understand its limits and vascular risk. See more on non-surgical rhinoplasty.
| Feature | Surgical nasal tip plasty | Non-surgical filler |
|---|---|---|
| Cartilage reshaping | Yes | No |
| Structural support | Yes | No |
| Tip projection | Can correct structurally | Can camouflage mildly |
| Droopy tip correction | Possible in selected cases | Limited |
| Flat tip correction | Structural support possible | Temporary camouflage |
| Breathing improvement | Only if structural airway issue is addressed | Not reliable |
| Duration | Longer-lasting structural correction | Temporary, often months |
| Main risk | Surgical risks | Vascular occlusion risk |
Nasal filler is not a harmless shortcut. Published medical literature describes rare but serious vascular complications after nasal filler, including skin injury and vision-related emergencies. Severe pain, blanching, dusky discolouration, or any visual symptom after nasal filler needs urgent emergency evaluation.
Sources:
https://pmc.ncbi.nlm.nih.gov/articles/PMC6624005/ ·
https://pmc.ncbi.nlm.nih.gov/articles/PMC4859242/
How Is Nasal Tip Plasty Performed? (Step By Step)
Nasal tip plasty is performed by reshaping and supporting the cartilage in the lower third of the nose without routinely altering the nasal bones. Through either a closed or open approach, the surgeon may use precise sutures, conservative cartilage trimming and supportive grafts to improve tip definition, projection, rotation, symmetry and stability. The procedure is then completed with fine sutures, tapes and, when required, a light splint.
| Step | What happens | Why it matters |
|---|---|---|
| 1 | Final marking and photographs; tip-defining points, columella and alar rims marked with the patient sitting up | Symmetry is planned upright, not lying down |
| 2 | Anaesthesia — general, or local with sedation for selected closed refinements — with continuous monitoring | Comfort and safety |
| 3 | Local infiltration with a vasoconstrictor | A clear, low-bleeding surgical field |
| 4 | Approach: closed (internal marginal / intercartilaginous incisions) or open (trans-columellar incision joined to marginal incisions) | Open for exposure in graft-heavy or asymmetric cases; closed for limited refinement |
| 5 | Skin envelope elevated over the tip cartilages | The lower lateral cartilages are seen and assessed directly |
| 6 | Diagnosis confirmed under direct vision: dome width, crural strength, support, asymmetry | The plan is adjusted to what the cartilage actually shows |
| 7 | Support first — columellar strut, septal extension or tongue-in-groove fixation if the tip is weak, droopy or flat | Projection and rotation are set on a stable base |
| 8 | Shaping — transdomal / interdomal sutures; conservative cephalic trim only where excess exists | Definition without over-resection |
| 9 | Grafts as needed — tip graft, lateral crural strut or alar grafts (septal or ear cartilage) | Definition in thick skin; valve support in pinched or weak tips |
| 10 | Check from front, profile and basal view; smile test under sedation is not possible, so dynamic droop is addressed by design (e.g. depressor septi release if planned) | Confirms symmetry, projection and rotation |
| 11 | Closure with fine sutures; internal incisions absorbable; columellar incision fine non-absorbable | Minimal scarring |
| 12 | Tip tapes and, where indicated, a light splint; no packing in most tip-only cases | Controls tip swelling; comfortable recovery |
Elements used in nasal tip plasty
| Element | Purpose |
|---|---|
| Transdomal / interdomal sutures (fine permanent or long-absorbing) | Refine and narrow the domes; set the distance between them |
| Columellar strut (septal cartilage) | Central support for projection and rotation |
| Septal extension graft / tongue-in-groove | Fixes tip position to the septum in droopy or flat tips |
| Tip (cap / shield) graft | Adds definition and projection, especially under thick skin |
| Lateral crural strut / alar batten grafts | Strengthens weak or collapsed side arms; protects the external valve |
| Ear (conchal) cartilage | Graft source when septal cartilage is insufficient or previously used |
| Surgical loupes / magnification | Millimetre-level precision on cartilage |
| Tip tapes and light splint | Early swelling control |
When Will I See The Results Of Nasal Tip Plasty?
You will notice a change in the nasal tip within the first 1–2 weeks, but the final result develops gradually as swelling settles. Tip definition usually becomes clearer over 3–6 months, while the final shape is typically seen around 12 months. In patients with thicker skin, refinement may continue for up to 12–18 months.
| Time | What you see |
|---|---|
| Week 1 | Tapes / splint on; tip swollen and firm; shape not yet readable |
| Week 2 | Tapes off; the tip is clearly changed but rounder and firmer than the final result; back to work |
| 6 weeks | Most non-tip swelling gone; tip still full; support grafts feel firm |
| 3 months | Tip definition emerging; projection and rotation visible; thin skin near final |
| 6 months | Refinement continues; supratip fullness settling; medium skin near final |
| 12 months | Final result in most patients; thick skin may continue to refine to 12–18 months |
Factors that affect the timeline: skin thickness (thick, oily skin holds tip swelling longest), whether support grafts were used, open vs closed approach, sun and heat exposure, and adherence to taping and follow-up.
What Aftercare Does Nasal Tip Plasty Require?
After nasal tip plasty, aftercare focuses on protecting the newly shaped tip, controlling swelling and allowing the cartilage and grafts to heal in a stable position. Patients are usually advised to keep tapes or the splint dry, sleep with the head elevated, avoid pressure on the nose, take prescribed medicines and attend scheduled follow-ups. Strenuous activity, smoking, sun exposure and anything that puts pressure on the tip should be avoided during the early healing period.
- Keep the tip tapes / splint dry and untouched until the review visit.
- Sleep with the head raised for the first week.
- Cold compresses beside the nose (not on the tip) for the first 48 hours.
- Take medicines as prescribed; saline sprays for comfort once cleared.
- Return for tape removal, and for reviews at 1 week, 6 weeks, 3, 6 and 12 months.
- Tip taping at night may be advised for a few weeks in thick-skinned patients.
- Report increasing pain, redness, fever or bleeding immediately.
| Avoid | For how long |
|---|---|
| Touching, pressing or “checking” the tip | 6 weeks |
| Glasses resting on the nose (use cheek support / tape to forehead) | 4–6 weeks |
| Nose blowing; sniff and dab instead | 2–3 weeks |
| Strenuous exercise, bending, lifting | 3–4 weeks; contact sports 3 months |
| Sun exposure on the nose | 3 months (SPF thereafter) |
| Smoking / nicotine in any form | 4 weeks before and after — ideally permanently |
| Facials, steam, saunas | 6 weeks |
| Judging the result in the mirror | 6 months — the tip is the last part of the nose to settle |
Full week-by-week aftercare: Rhinoplasty recovery & aftercare guide →
What Are The Risks Of Nasal Tip Plasty — And When Should You Seek Urgent Care?
Nasal tip plasty has risks including asymmetry, over-correction, under-correction, pinching, visible irregularity, supratip fullness, prolonged swelling, breathing change, and revision need. Both tip plasty and filler treatments require urgent review when pain, colour change, bleeding, fever, obstruction, or vision symptoms occur.
Expected and temporary
- Tip swelling and firmness for weeks to months (longer in thick skin).
- Numbness of the tip for a few weeks to months.
- Temporary asymmetry from uneven swelling.
Uncommon
| Risk | Meaning |
|---|---|
| Asymmetry | Tip may heal unevenly |
| Under-correction | Tip remains insufficiently refined |
| Over-correction | Tip looks too narrow or unnatural |
| Pinched tip | External valve may narrow |
| Supratip / pollybeak fullness | Fullness above the tip |
| Visible irregularity | More noticeable in thin skin |
| Prolonged swelling | More common in thick skin |
| Breathing change | Support or valve issue may be involved |
| Revision need | May be required in selected cases |
Rare
- Infection, bleeding needing review, graft displacement or visibility, skin compromise.
| Risk | How Dr. Doshi minimises it |
|---|---|
| Pinched tip / valve narrowing | Conservative cephalic trim; lateral crural support preserved or added |
| Over- or under-correction | Diagnosis first; support-based planning; no “make it sharp” on thick skin |
| Visible graft edges | Grafts avoided or camouflaged under thin skin |
| Prolonged swelling | Thick-skin protocol: taping, follow-up, realistic timeline |
| Asymmetry | Upright marking; basal-view checks; differential suturing |
| Infection / bleeding | NABH facility, sterilisation, controlled anaesthesia, nicotine rule |
Seek immediate care
| Red flag | Why it matters |
|---|---|
| Bleeding that does not stop | Needs urgent review |
| Fever with worsening pain | Possible infection |
| Worsening redness | Infection or inflammation concern |
| Rapidly worsening obstruction | Airway or swelling concern |
| Increasing pain with skin colour change | Vascular or infection concern |
| Severe pain after filler | Possible vascular compromise |
| Blanching after filler | Possible vascular occlusion |
| Dusky skin after filler | Skin blood-flow concern |
| Eye pain after filler | Emergency warning sign |
| Any vision change after filler | Emergency — vision risk |
| Chest pain or breathlessness | Emergency medical care |
Sources: PMC3901916 · PMC3199839 ·
Full risk guide → Rhinoplasty Risks & Safety
What Is The Recovery Timeline After Nasal Tip Plasty?
Nasal tip plasty recovery is usually less extensive than full rhinoplasty when only the tip is treated, but tip swelling can still last weeks to months. Patients often resume daily activity in about 7–10 days, while final definition takes longer in thick skin.
| Recovery point | Summary |
|---|---|
| Splint / dressing | Early support or dressing depends on technique |
| Day 1–3 | Tip swollen and firm; mild discomfort; head elevated; usually no black eyes because bones are untouched |
| Day 7–10 | Tapes / splint removed; daily activity and desk work resume |
| Swelling | Tip swelling settles gradually over weeks to months |
| Week 3–4 | Light exercise; glasses with support |
| Month 3 | Shape readable; contact sports allowed |
| Final tip definition | May take months; longer in thick skin |
Key points: recovery is shorter than full rhinoplasty because there is no bone work; the tip is the last part of the nose to settle; support-graft cases feel firm longer; outstation patients stay until tape removal (about a week); flying after written clearance.
Medical Codes Related To Nasal Tip Plasty
Codes below are for administrative and documentation reference. All codes must be verified against the current CPT and ICD-10 code sets before publication and before any use in documentation.
| Code system | Code | Description |
|---|---|---|
| CPT | 30400 | Rhinoplasty, primary; lateral and alar cartilages and/or elevation of nasal tip |
| CPT | 30410 | Rhinoplasty, primary; complete, external parts including bony pyramid, lateral and alar cartilages, and/or elevation of nasal tip (when tip work is part of full rhinoplasty) |
| CPT | 30430 / 30435 / 30450 | Rhinoplasty, secondary; minor / intermediate / major revision (pinched-tip repair after previous surgery) |
| CPT | 21235 | Graft; ear cartilage, autogenous, to nose or ear |
| CPT | 20912 | Cartilage graft; nasal septum |
| ICD-10-CM | Z41.1 | Encounter for cosmetic surgery |
| ICD-10-CM | M95.0 | Acquired deformity of nose |
| ICD-10-CM | Q30.8 | Other congenital malformations of nose (congenital tip asymmetry) |
| ICD-10-CM | J34.89 | Other specified disorders of nose and nasal sinuses (external valve collapse) |
| ICD-10-CM | T85.89XA / T81.89XA | Complication of prior graft / prior procedure (revision context) |
Frequently Asked Questions About Nasal Tip Plasty
Q1. Can nasal tip plasty correct a droopy tip?
Ans. Yes — it can improve a droopy or ptotic tip when the issue comes from weak support, age-related descent, or poor rotation. Correction usually restores support and rotation rather than simply narrowing or removing cartilage.
Q2. Can nasal tip plasty correct a boxy tip?
Ans. Yes. Boxy tip correction may use sutures, controlled cartilage reshaping, conservative cephalic trim, or grafting. The aim is better definition without over-narrowing the tip or weakening the external nasal valve.
Q3. What is an over-projected tip?
Ans. An over-projected tip sticks too far forward from the face and may make the nose look long or dominant. Correction rebalances projection and support; it should not be treated by simple cartilage removal without structural planning.
Q4. What is an under-projected or flat tip?
Ans. An under-projected or flat tip lacks forward support and may look weak, broad, or poorly defined. Correction usually requires structural support such as a columellar strut, tip graft, septal extension graft, or tongue-in-groove stabilisation.
Q5. Can a pinched tip affect breathing?
Ans. Yes. A pinched tip can narrow the external nasal valve because the lower lateral cartilages help support airflow. Correction often requires structural support or grafting, not more narrowing.
Q6. Can nasal tip plasty fix asymmetry?
Ans. It can improve selected tip asymmetry caused by cartilage shape, trauma, congenital difference, or previous surgery. Perfect symmetry is not realistic, because healing and anatomy are naturally variable.
Q7. Is filler a safe alternative to tip plasty?
Ans. Filler can temporarily camouflage minor tip concerns but cannot remodel cartilage or reliably improve breathing. Nasal filler has rare but serious vascular risks, including skin and vision complications, so it should not be treated as a casual shortcut.
Q8. What are filler emergency signs?
Ans. Severe pain, blanching, dusky skin colour, skin discolouration, eye pain, or any vision change after nasal filler should be treated as urgent. Contact the injector immediately and seek emergency medical care.
Q9. Can tip plasty be done under local anaesthesia?
Ans. Selected closed, suture-only refinements can be done under local anaesthesia with sedation. Cases needing grafts, an open approach or septal cartilage harvest are usually done under general anaesthesia for comfort and precision. The anaesthetist decides with you at the pre-op review.
Q10. Will my tip look pinched or “done”?
Ans. Not if support is preserved. Pinching comes from over-resection of the lower lateral cartilages; Dr. Doshi’s approach is conservative trimming plus support, so the tip is refined but keeps its natural width at the nostrils and its strength when you smile.
Q11. I have thick skin — will tip plasty even show?
Ans. Yes, but more slowly and more modestly than on thin skin. Thick skin hides fine cartilage changes and holds swelling longer, so definition is planned with support and grafts rather than narrowing alone, and the result is judged at 12 months, not 6 weeks. For thick, oily, bulbous tips, read the bulbous tip correction page.
Related Links
- Rhinoplasty Surgery (hub)
- Bulbous & Boxy Tip Correction
- Drooping Tip Correction
- Revision Rhinoplasty (pinched tip after surgery)
- Crooked Nose Correction
- Septorhinoplasty
- Functional Rhinoplasty
- Augmentation Rhinoplasty
- Wide Nostril Correction
- Open vs Closed Rhinoplasty
- Non-Surgical Rhinoplasty
- Chin Augmentation (tip–chin balance)
- Rhinoplasty Cost
- Rhinoplasty Recovery Timeline
- How to Prepare for Rhinoplasty
- Rhinoplasty Risks & Safety
- Rhinoplasty Before & After Gallery

