
Septorhinoplasty in Mumbai: Breathe Better & Reshape Your Nose in One Surgery

Indian Board Certified Plastic Surgeon
M.CH, MS, ISAPS Mentor
16000+ Cosmetic Surgeries
1500+ Rhinoplasty Surgeries
Septorhinoplasty corrects a deviated septum and reshapes the external nose in one operation — for patients whose blocked breathing and crooked, humped or unsupported nose come from the same structural problem. At Allure Medspa Mumbai, Dr. Milan Doshi plans airflow, septal support and facial harmony together, because the septum is not just an internal wall: it is the beam the whole nose rests on.
Septorhinoplasty Before And After Images
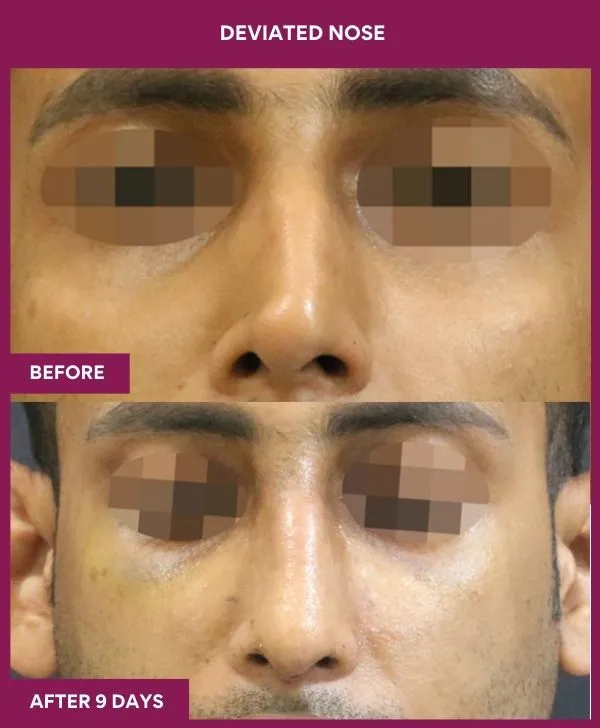
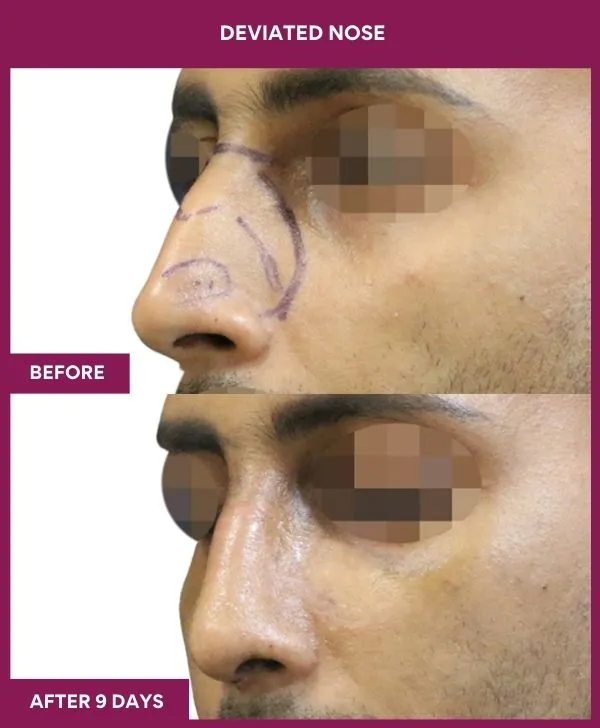
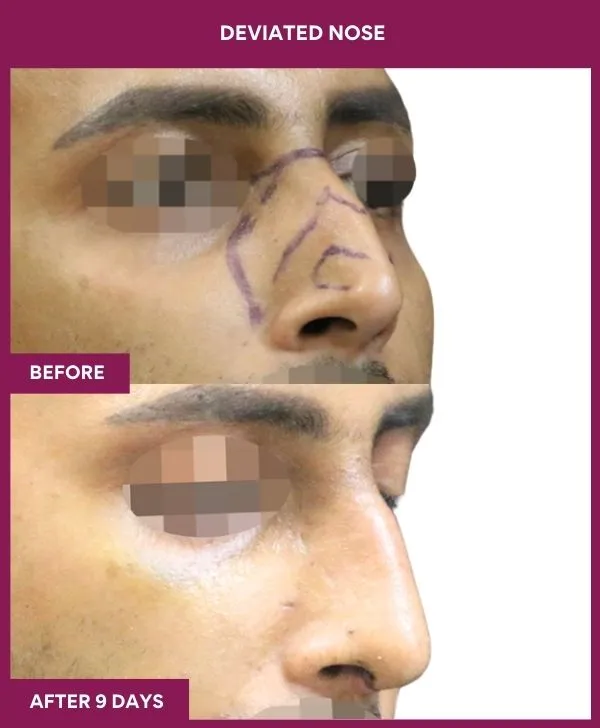
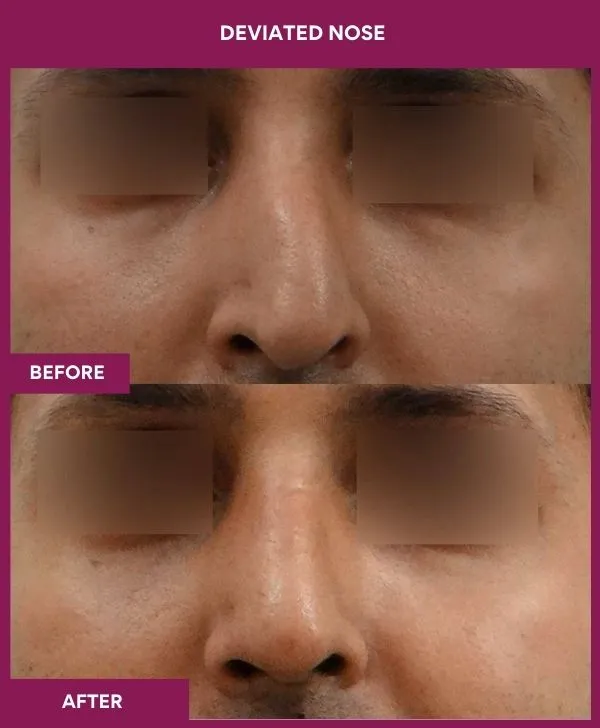
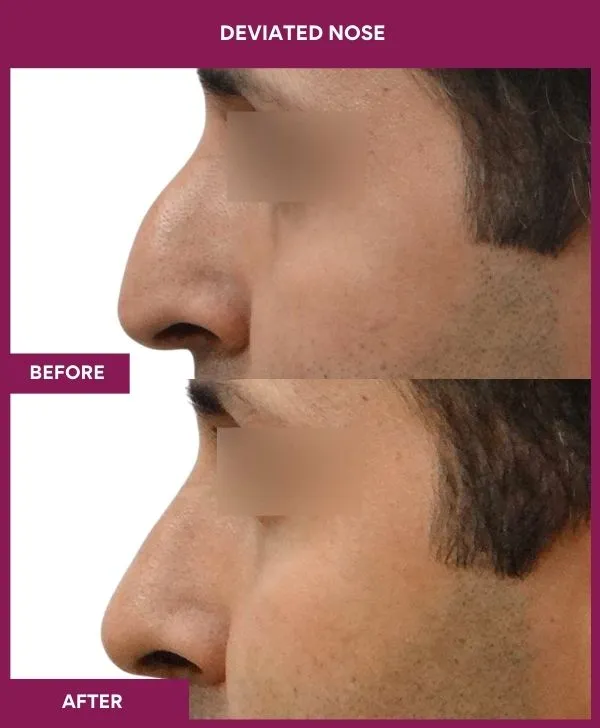
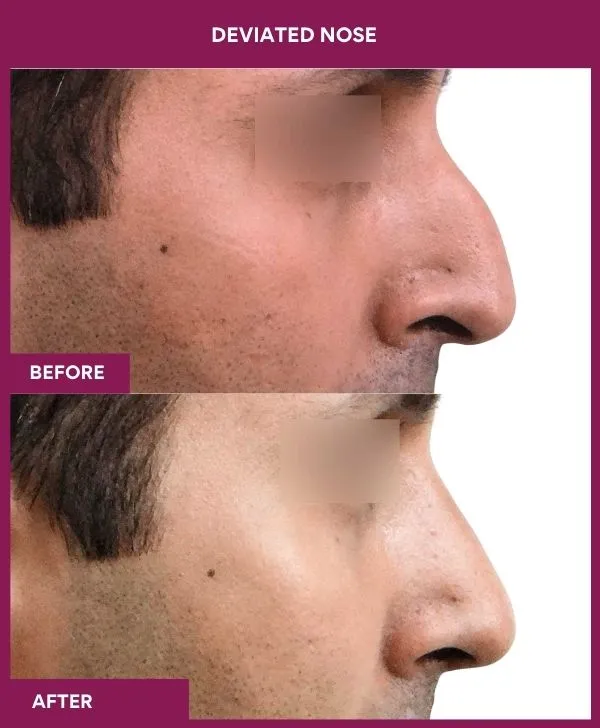
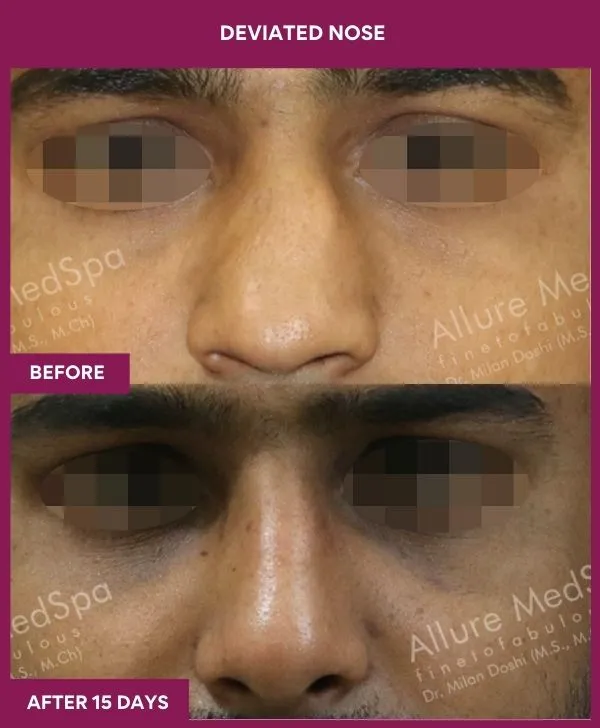
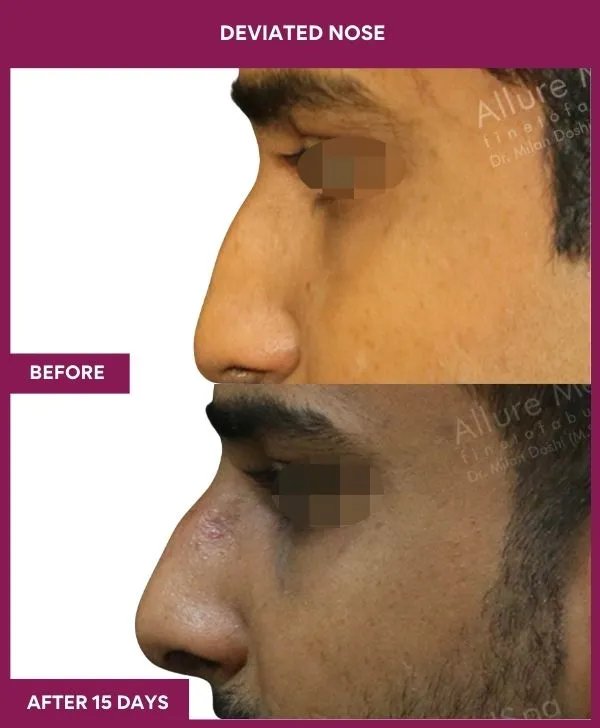
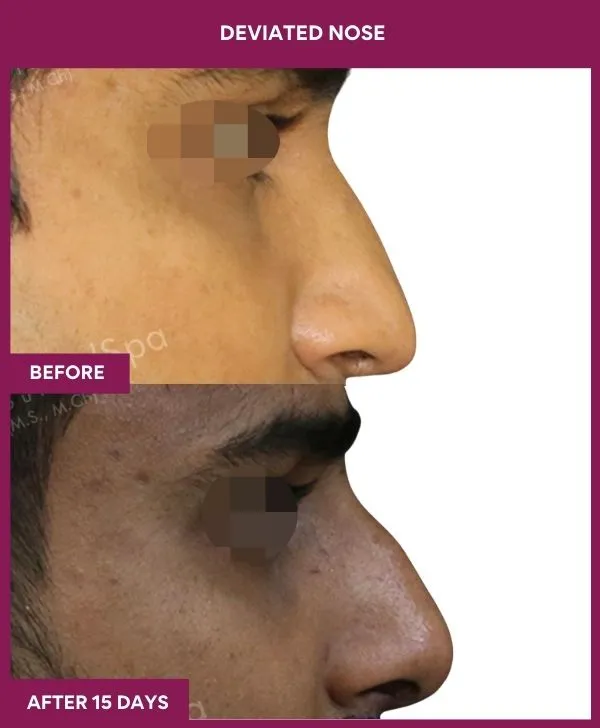
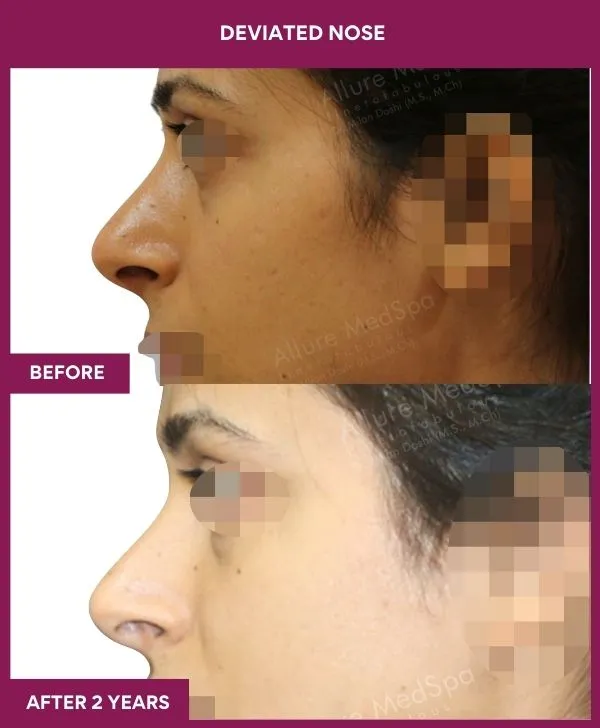
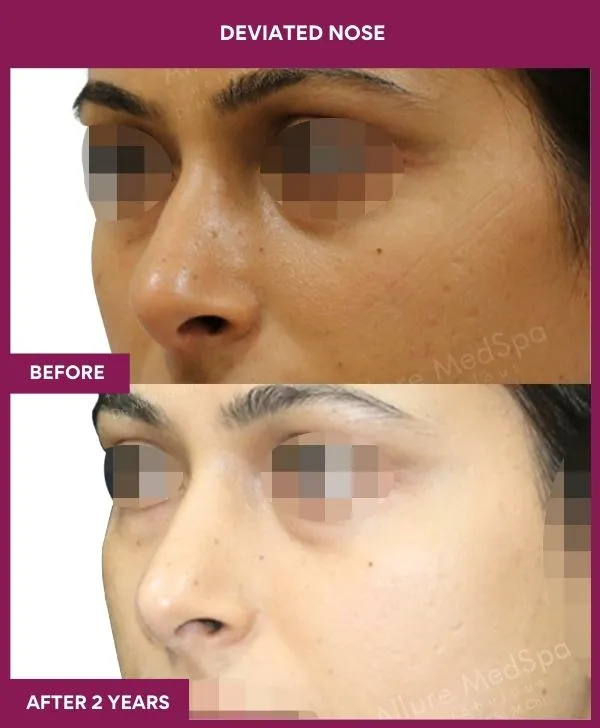
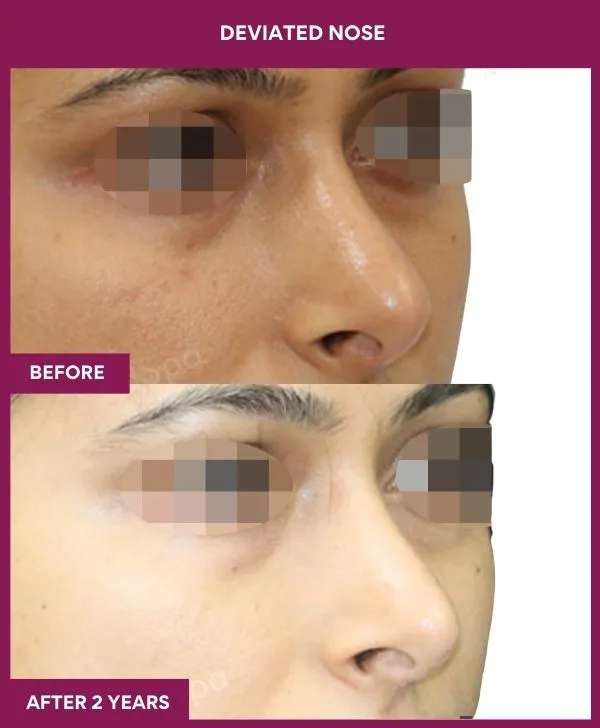
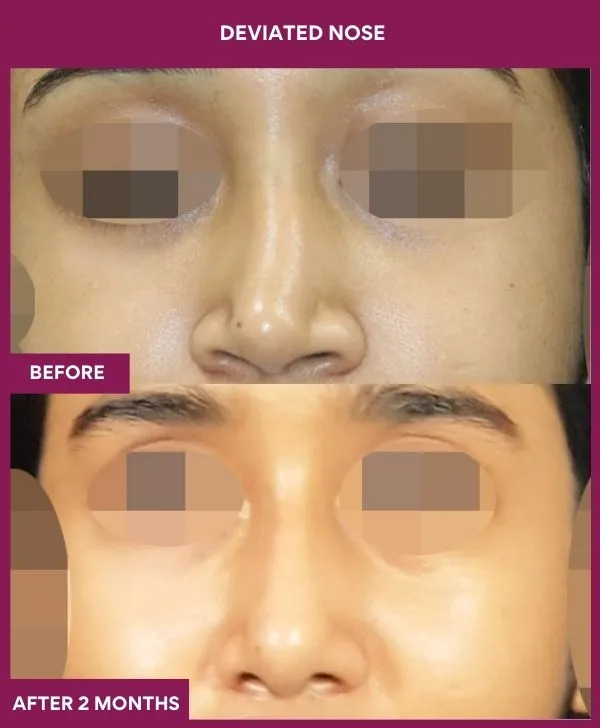
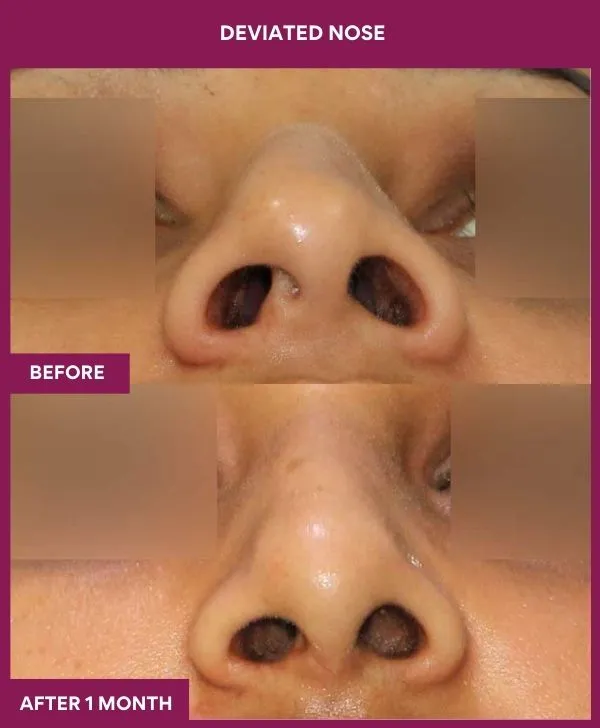
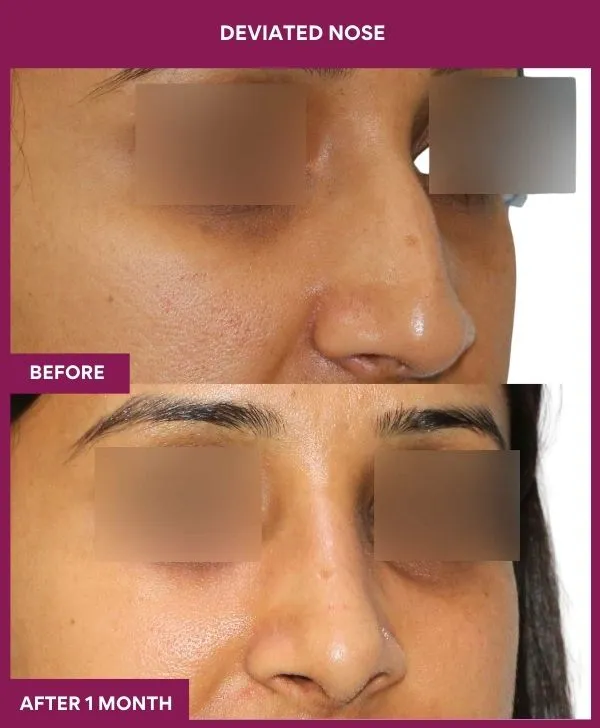
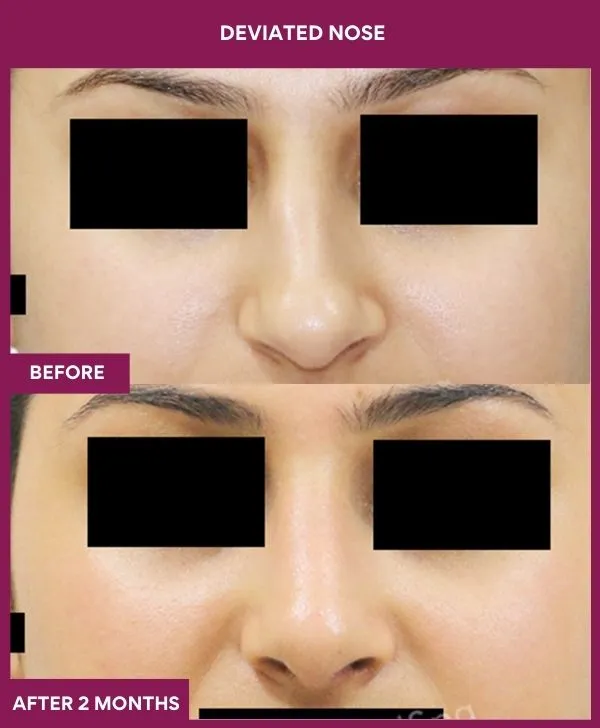
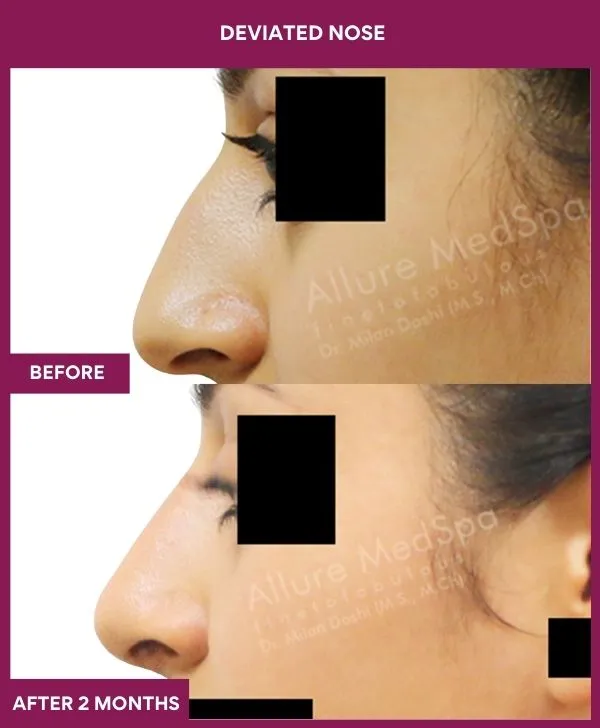
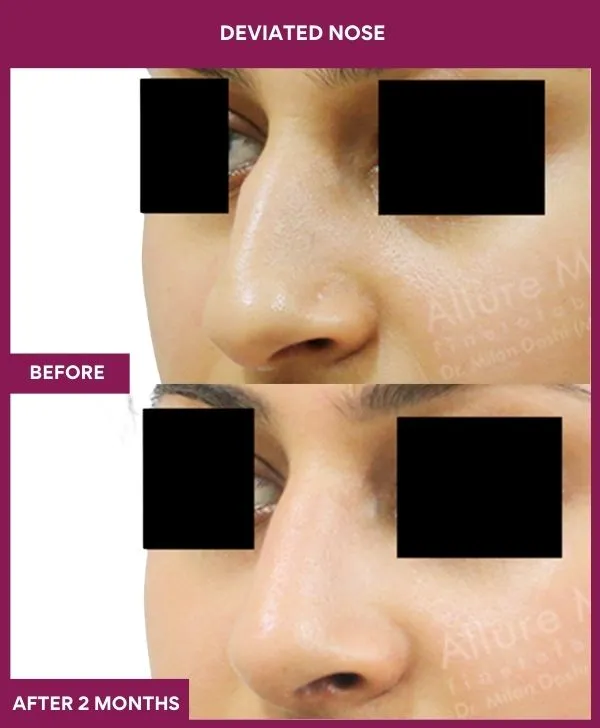
Rhinoplasty Surgery Testimonials: Celebrities Patient

Awarded by Google.com
Rating: 4.7
Reviews: 485+

Awarded by WhatClinic.com
Rating: 4.8
Reviews: 119+

Awarded by Realself
Rating: 4.9
Reviews:453+

Awarded by Facebook
Rating: 4.6
Reviews:105+
Dr Milan Doshi and his staff are very professional and committed as the centre is highly equipped with advanced technology. I had closed rhinoplasty 4 months back and I’m seeing the results as to how it becomes successful.
Deepika Shetty
The doctor explained everything clearly and the surgery was smooth. Recovery was faster than I expected and the team was very supportive.
Rahul Mehta
Very natural results and excellent staff. From consultation to follow-up, the experience was outstanding and boosted my confidence.
Sneha Kapoor
Video: Best Rhinoplasty Surgeon explain nose reshape procedure
Dr Milan Doshi is describing the Rhinoplasty Surgery in detail with benefits, techniques, recovery, result, risk and complecations
Am I a Candidate?
(4 quick questions)
Breathing plus appearance? You’re the textbook case.
Get My AssessmentSurgery only when truly needed
Quick Facts About Septorhinoplasty
TIME REQUIRED
2–3 hours
ANESTHESIA
General
HOSPITAL STAY
Day-care or 1 night
PAIN LEVEL
Mild–moderate
BACK TO WORK
7–10 days
RESULTS LAST
Permanent
SUCCESS RATE
97–98%
COMPLICATIONS
Under 2-3%
Get your exact quote & surgery plan
Share your details — our team responds within working hours with cost, EMI options and next steps.
How Much Does Septorhinoplasty Cost in Mumbai?
Septorhinoplasty in Mumbai starts from ₹1,20,000 to ₹3,50,000 and varies with septal deviation severity, how much cosmetic reshaping is combined (straightening only, or hump, tip and base work as well), whether spreader, strut or extension grafts are needed and from where, the open or closed approach, anaesthesia and hospital facility, whether functional documentation for insurance is required, and whether the case is primary, post-traumatic or revision. A final quotation follows examination, endoscopy and a written surgical plan — it cannot be given accurately by phone or from photographs.
| Septorhinoplasty scope | Indicative price range |
|---|---|
| Septoplasty + limited external straightening (osteotomies) | ₹1,20,000 – ₹1,70,000 |
| Septoplasty + valve support (spreader grafts) — functional septorhinoplasty | ₹1,50,000 – ₹2,10,000 |
| Septum + crooked nose correction (bones, midvault, tip) | ₹1,70,000 – ₹2,40,000 |
| Septum + hump reduction + tip refinement (full cosmetic reshaping) | ₹1,90,000 – ₹2,70,000 |
| Post-traumatic septorhinoplasty with grafting | ₹2,00,000 – ₹2,90,000 |
| Severe C / S-shaped septum — extracorporeal septoplasty + reshaping | ₹2,30,000 – ₹3,20,000 |
| Revision septorhinoplasty (ear / rib cartilage) | ₹2,50,000 – ₹3,50,000 |
Most Common Question People Ask
Q1. Is septorhinoplasty different from septoplasty?
Ans. Yes. Septoplasty mainly corrects the internal septum to improve airflow. Septorhinoplasty also reshapes the external nose, corrects support, and may improve nasal alignment, tip shape, bridge contour or valve support in the same operation.
Q2. How much does septorhinoplasty cost in Mumbai?
Ans. At Allure Medspa, septorhinoplasty guide pricing is ₹1,20,000–₹3,50,000, with 5% GST extra. Final cost depends on septal deviation, cosmetic reshaping, grafts, anaesthesia, hospital facility and whether additional airway correction is required.
Q3. Is septorhinoplasty covered by insurance?
Ans. Insurance may consider the functional septum or airway portion if medical necessity is documented. Cosmetic reshaping is usually self-paid. In India, coverage depends on policy wording, insurer approval, documentation and pre-authorisation. Do not assume automatic coverage — our team helps prepare the paperwork.
Q4. Can septorhinoplasty improve breathing?
Ans. Septorhinoplasty may improve breathing when obstruction is caused by septal deviation, nasal valve narrowing, trauma-related deformity or structural collapse. Breathing improvement depends on the exact cause of blockage and is assessed clinically — with endoscopy and a NOSE score — before surgery.
Q5. Will septorhinoplasty change how my nose looks?
Ans. Yes, if rhinoplasty correction is part of the plan. Changes may include straighter alignment, better bridge shape, improved tip support or better nostril balance. If you want breathing fixed and the appearance left alone, that is planned just as carefully — and may point to the functional rhinoplasty page instead.
Q6. How long does septorhinoplasty recovery take?
Ans. Early recovery takes about a week to 10 days; breathing improves over 1–3 months as internal swelling settles; cosmetic refinement takes 6–12 months or longer. Thick skin, revision surgery or structural grafting can extend the visible timeline.
Q7. Will it look natural?
Ans. A natural result depends on straightening the actual structure — septum, bones, cartilage — rather than camouflaging it, protecting the airway while reshaping, and keeping the nose in proportion to a face that is itself slightly asymmetric. The aim is a nose that works better without looking operated. Results vary between individuals and cannot be guaranteed.

Why Choose Dr. Milan Doshi?
Dr. Milan Doshi, MCh, MS — Indian board-certified plastic surgeon with 27+ years in aesthetic surgery and 1,500+ rhinoplasties, where airflow, septal support, alignment, tip stability and facial balance are planned as one problem. ISAPS mentor, trusted by patients from 70+ countries. Consults at Andheri West; surgeries at the NABH-accredited surgical centre, Goregaon West.
The Complete Guide About Septorhinoplasty
What Is Septorhinoplasty?
Septorhinoplasty is a combined nose surgery that corrects a deviated septum and reshapes the external nose in one operation. It may improve breathing, nasal alignment, tip support, bridge shape or facial balance when both the internal airway and external nasal structure need correction.
A septoplasty alone works mainly on the internal septum. Rhinoplasty works on external nasal shape. Septorhinoplasty connects both, because the septum is not only an airway structure; it also helps support the nasal tip, dorsal alignment, midline stability and airflow.
This distinction matters. If the septum is corrected without respecting external balance, the nose may still look deviated or unsupported. If the outer nose is reshaped without protecting the airway, breathing can suffer. Planning the two together is the whole point of the operation.
Septorhinoplasty is also called
- Septoplasty with rhinoplasty — when septal correction and reshaping are combined.
- Functional septorhinoplasty — when nasal obstruction and external deformity are treated together.
- Deviated nose correction — when the visible bend follows the septum.
Where breathing is the only goal and the blockage is at the valve or turbinates rather than the septum, the more relevant page is functional rhinoplasty; where the septum is straight and the concern is purely cosmetic, see cosmetic rhinoplasty.
Is septorhinoplasty cosmetic or reconstructive?
| Type | Main purpose | Common example |
|---|---|---|
| Functional / reconstructive | Restore breathing and structural support | Septoplasty with spreader grafts for a deviated septum and collapsed valve |
| Cosmetic (aesthetic) | Improve alignment, bridge, tip or proportion | Hump reduction and tip refinement done in the same operation |
| Mixed — the usual septorhinoplasty | Both, planned and consented separately | Deviated septum + crooked bridge + hump corrected together |
Most septorhinoplasties are mixed. The functional portion may be considered by insurers where obstruction is documented; cosmetic reshaping is usually self-paid. In India, coverage is policy-specific and needs pre-authorisation (see the insurance table in the Consult section).
Synonyms for septorhinoplasty
Patient terms: deviated septum surgery with nose job, breathing and nose shape surgery, septum and nose correction, bent nose breathing surgery, nose surgery for blocked nose and crooked nose
Medical terms: septorhinoplasty, functional septorhinoplasty, septoplasty + rhinoplasty, extracorporeal septoplasty, caudal septal reconstruction, septal extension graft rhinoplasty
Sources: NCBI – Rhinoplasty (StatPearls) · Mayo Clinic – Septoplasty
🩺 Dr. Doshi’s Note: “In septorhinoplasty, I do not treat breathing and appearance as two separate problems. The septum is not only an internal partition; it is also an important support structure for the nose. If the septum is corrected without respecting external balance, the nose may still look deviated or unsupported. If the outer nose is reshaped without protecting the airway, breathing can suffer. My aim is to balance three things together: airflow, structure, and natural-looking facial harmony.”
Do You Have a Deviated Septum?
Many people describe the same experience: one nostril has “never worked properly,” they sleep on one side, snore, breathe through the mouth at the gym — and, when they look closely, the nose itself leans the same way. That combination is the signature of a deviated septum with an external bend, and it is worth discussing.
Septorhinoplasty may be considered when a deviated septum causes nasal blockage, mouth breathing, snoring, recurrent sinus symptoms, sleep disturbance or exertional breathing discomfort, especially when external nasal shape is also affected. Septal deviation is common, but its exact prevalence varies by study method and diagnostic criteria.
Three questions patients actually ask at consultation:
- “If you fix the septum, will my nose look straight too?”
- “Can I get the hump removed at the same time, and will insurance still cover the breathing part?”
- “I had septoplasty years ago — why is my nose still blocked and still crooked?”
These questions do not automatically mean surgery is needed. A mild deviation without symptoms is best left alone; a purely cosmetic wish does not need septal surgery; allergy and sinus disease need medical treatment first. The useful question is not “is my septum deviated?” (most are, slightly) but “is my septum causing both my blockage and my bend — and does it need one operation or two?”
Deviated septum symptom self-check
| Symptom | Why it matters |
|---|---|
| One-sided nasal blockage | Common functional complaint |
| Mouth breathing | May suggest poor nasal airflow |
| Snoring | Can worsen with nasal resistance |
| Recurrent sinus symptoms | May occur in selected obstructive patterns |
| Poor sleep quality | Blockage can disturb sleep |
| Exercise breathing discomfort | Nasal resistance may become noticeable |
| Crooked-looking nose | External deviation may coexist |
What causes septal deformity?
Septorhinoplasty planning depends on the type and cause of septal deformity, because a simple septal bend, spur, C-shaped deviation, S-shaped deviation, caudal deviation or post-traumatic deformity may each need different correction. The visible nose and internal septum must be evaluated together.
| Type / cause | What it means | Why it matters |
|---|---|---|
| Congenital deviation | Present from early development | May affect lifelong airflow |
| Developmental deviation | Grows gradually with facial development | May worsen with maturity |
| Post-traumatic deviation | Follows injury or fracture | Often affects both septum and outer nose |
| Simple deviation | Septum bends to one side | May block one nostril |
| Septal spur | Sharp bony / cartilage projection | Can irritate mucosa or narrow airflow |
| C-shaped deviation | Curved deviation to one side | May create visible crookedness |
| S-shaped deviation | Multi-directional bend | More complex to correct |
| Caudal deviation | Front / lower septum displaced | Can affect tip support and valve area |
Sources: NCBI – Nasal Septal Deviation (StatPearls) · Mayo Clinic – Septoplasty
What Are the Medical and Aesthetic Benefits of Septorhinoplasty?
Septorhinoplasty may improve nasal airflow and external nasal balance in one operation when both problems share a structural cause. It can address septal deviation, valve narrowing, crooked appearance, bridge irregularity, tip support or asymmetry — with one anaesthetic, one recovery and one bill — but functional and cosmetic improvement must be discussed separately, because they heal and succeed on different timelines.
Possible medical benefits
- Airflow: improves obstruction when septal deviation is the cause.
- Valve support: may improve internal valve narrowing.
- Congestion: may reduce blockage related to structural narrowing.
- Sleep: may improve comfort when nasal obstruction contributes (sleep apnoea is a separate diagnosis and is not claimed).
- Exercise: may reduce airflow limitation in selected patients.
- Sinus symptoms: may help selected obstruction-related complaints.
Possible aesthetic benefits
- Alignment: straighter-looking nose.
- Bridge: improved dorsal shape.
- Tip: better support and projection.
- Symmetry: more balanced nostrils or nasal axis.
- Harmony: better fit with facial proportions.
- Preserved identity: the aim is your nose, straighter and stronger; everyone notices better balance, no one knows it was surgery.
Practical benefits of doing both together
- The septal cartilage removed to open the airway becomes the graft material that supports the new shape — nothing is wasted and no second donor site is needed.
- One anaesthetic, one hospital stay, one recovery instead of two.
- Straightening the septum and the outer nose in the same operation avoids the common outcome of a straight septum inside a still-crooked nose.
Functional success and cosmetic satisfaction are not the same endpoint. A patient may breathe better while still waiting for swelling to settle, or like the shape while still needing time for airflow to improve.
Sources: AAO-HNS – Nasal Form & Function Guideline
Which Problems Can Septorhinoplasty Correct?
Septorhinoplasty mainly treats a deviated septum that blocks breathing, a crooked or bent external nose that follows it, a weak or collapsed middle vault, an unsupported tip, and a hump or asymmetry that the patient wants corrected at the same time. It does not reliably correct: allergy or sinus disease, enlarged turbinates alone (though they can be reduced in the same operation), valve collapse with a straight septum, or sleep apnoea.
| Concern | Relevance to this page | Possible approach | Learn more |
|---|---|---|---|
| Deviated septum blocking one side | Core target | Septoplasty preserving the L-strut | This page |
| Septum deviated AND nose visibly bent | Core target | Septal correction + osteotomies + midvault support | This page |
| Caudal septal deviation (tip pushed sideways / nostril asymmetry) | Core target | Caudal septal repositioning / extension graft | This page |
| Severe C / S-shaped septum | Core target | Extracorporeal septoplasty | This page |
| Deviated septum + hump or tip concern | Core target (mixed) | Septoplasty + cosmetic reshaping | This page |
| Post-traumatic blocked, bent nose | Core target | Septum and bone realignment + grafts | Crooked Nose Correction |
| Valve collapse / turbinates with a straight septum | Different diagnosis | Functional rhinoplasty | Functional Rhinoplasty |
| Crooked nose with normal breathing | Overlap | Crooked nose correction (may still need septal work) | Crooked Nose Correction |
| Blocked / bent after previous surgery | Revision case | Revision septorhinoplasty | Revision Rhinoplasty |
| Allergy / sinus disease | Medical pathway first | ENT / allergy management | Consult |
The anatomy of the septum — the structures this surgery works on
Understanding a few terms makes consultation far easier.
- Septum — the central wall dividing the two nasal passages: cartilage in front, bone behind. Deviation narrows one side.
- The septum as a support beam — the front edge of the septal cartilage holds up the middle third of the nose and the tip. When it bends, the outer nose bends with it; when it is over-resected, the nose can collapse (saddle) or the tip can drop.
- L-strut — the L-shaped rim of septal cartilage (at least 1–1.5 cm along the top and the front) that must be preserved in every septoplasty so the nose keeps its support.
- Caudal septum — the front, lower edge just behind the columella. Deviation here pushes the tip sideways, makes one nostril smaller and blocks the external valve.
- Septal spur — a sharp ridge where cartilage meets bone, often after an old injury; it can press on the turbinate and cause blockage or headache.
- Internal nasal valve — the narrow angle between the septum and the upper lateral cartilage; a deviated septum narrows it further, which is why spreader grafts are often added.
- Turbinates — internal shelves opposite the septum; the one on the wider side often enlarges to compensate and may need conservative reduction.
What Are the Limitations of Septorhinoplasty?
Septorhinoplasty works best when blockage and bend share a structural cause. It cannot cure allergy, sinus disease or spray-rebound congestion; it cannot promise perfect symmetry or a face-midline that is itself uneven; it cannot make a straight septum guarantee a straight-looking nose without addressing the bones and cartilage; and it cannot treat sleep apnoea. Being clear about these boundaries before surgery is one of the strongest predictors of satisfaction afterwards.
Two goals, two timelines, two different yardsticks. Breathing is judged at 1–3 months by airflow and a NOSE score; shape is judged at 12 months by photographs. A patient who expects both on the same day will be disappointed with one of them. Functional success and cosmetic satisfaction are separate endpoints and are counselled separately.
A straight septum can improve internal alignment, but the external nose may still look crooked if nasal bones, upper cartilages, tip support or soft-tissue forces are also involved — which is why septorhinoplasty addresses both. Cartilage memory, old fracture lines, thick skin and facial asymmetry can all leave a small residual deviation even after a good correction. Insurance may cover the functional portion but rarely the cosmetic one, and that split should be understood before surgery, not after. Results vary by individual anatomy and healing.
Why “more septum removed” is not better
- Saddle nose: over-resection collapses the bridge.
- Tip drop: losing caudal support de-rotates the tip.
- Septal perforation: thinning both sides of the mucosa risks a hole.
- Valve collapse: an unsupported middle vault narrows on breathing in.
- No graft material: cartilage discarded today is cartilage missing in a revision.
- Relapse: a bent segment left in place will pull the nose back.
Sources: NCBI – Nasal Septal Deviation (StatPearls) · AAO-HNS – Nasal Form & Function Guideline
Why Consult Before Septorhinoplasty?
A septorhinoplasty consultation is a diagnostic appointment, not a sales appointment. Its purpose is to confirm that the septum is causing the blockage, map how much of the visible bend follows it, decide what else (valve, turbinates, bones, hump, tip) needs to be corrected in the same operation, and separate the functional plan from the cosmetic plan — for surgery and for insurance.
What happens during a septorhinoplasty consultation?
Assessment typically covers your breathing history — which side, when, sprays, sleep, exercise, injury, previous surgery; an internal examination of the septum, turbinates and both nasal valves, usually with endoscopy; the Cottle test for valve involvement; a NOSE score; the external nose from the front, profile and base against the facial midline; palpation of the bones for old fracture lines and of the caudal septum for tip support; skin thickness; documented asymmetry; full medical history including medicines, supplements and nicotine use; your cosmetic goals, if any, in your own words; and your insurance situation. You should leave understanding whether the septum is the cause of your blockage, what the combined plan is, which parts are functional and which cosmetic, the alternatives including septoplasty alone or no surgery, the realistic extent of both improvements, the risks and the recovery required.
What should I prepare before consultation?
- Your breathing pattern — which side, since when, whether it moves, what makes it worse.
- Your appearance concern — bend, hump, tip, nostrils, or “just the breathing.”
- Injury history — when, how, whether it was ever set; old X-rays or reports if you have them.
- Previous nose surgery reports — operation notes, discharge summary.
- Every nasal spray and medicine you use, including how often.
- Insurance policy documents — so the functional documentation can be planned from the first visit.
- Front-view photographs in even light without makeup, and an old photo from before any injury.
- Reference photographs if you have cosmetic goals — for discussion, not as a target to replicate.
Will insurance cover septorhinoplasty?
Septorhinoplasty insurance coverage depends on whether the procedure is medically necessary, cosmetic or mixed. The septoplasty or functional airway portion may be considered when obstruction is documented, while cosmetic nose reshaping is usually self-paid. In India, coverage is policy-specific and needs pre-authorisation.
| Component | Insurance possibility |
|---|---|
| Septoplasty for documented obstruction | May be considered |
| Nasal valve repair | May be considered if medically necessary |
| Cosmetic bridge / tip reshaping | Usually self-paid |
| Combined septorhinoplasty | Functional part may be considered; cosmetic part usually excluded |
| Non-surgical cosmetic correction | Usually self-paid |
Indian insurance practice is not uniform across all insurers. Patients should check policy wording and obtain written pre-authorisation before surgery. Our team helps prepare the documentation insurers typically ask for — ICD-10 diagnosis, endoscopy findings, NOSE score and a surgeon’s note separating the functional from the cosmetic component.
Is an online septorhinoplasty consultation possible?
If you are outside Mumbai, you can request a preliminary WhatsApp pre-check with front, profile and basal photographs — plus a short video breathing in deeply — in even, natural lighting, without makeup or filters. This is preliminary guidance only. Photographs cannot replace endoscopy of the septum and valves, and no definitive diagnosis, technique recommendation, insurance opinion or final quotation can be given from them.
Consultation fee: ₹1,500
How to prepare: How to Prepare for Rhinoplasty
Sources: ASPS – Rhinoplasty · IRDAI (India) · PubMed 39808086
Which Techniques Are Used in Septorhinoplasty?
“Technique” in septorhinoplasty refers to how the septum is straightened while its support is preserved, how the middle vault and tip are then re-supported on it, and how the external nose is reshaped — plus whether the surgery is done open or closed. Technique selection depends on the source of obstruction, septal deformity, nasal valve status, external deviation, tip support, skin thickness and overall complexity. These are surgical decisions made from your anatomy, not a menu.
| Technique | Purpose | When it may be used |
|---|---|---|
| Open approach | Better exposure | Complex structural work, severe deviation, tip correction |
| Closed approach | Internal incisions | Selected limited cases |
| Septoplasty (L-strut preserving) | Straightens / corrects septum | Septal deviation causing obstruction |
| Caudal septal repositioning / swinging-door | Re-centres the front of the septum | Caudal deviation affecting tip and nostril |
| Extracorporeal septoplasty | Reconstructs severe septal deformity outside the nose | Severe C / S deviation not correctable in place |
| Spreader graft | Supports internal nasal valve | Valve narrowing or middle-vault support |
| Columellar strut | Supports nasal tip | Weak tip support |
| Septal extension graft | Stronger tip control | Major tip projection / rotation control |
| Osteotomy | Realigns nasal bones | Crooked bony pyramid or bridge correction |
| Hump reduction / tip refinement | Cosmetic reshaping | When part of the combined plan |
| Conservative turbinoplasty | Reduces compensatory turbinate bulk | Enlarged turbinate on the wider side |
Straightening the beam: Deviated segments of septal cartilage and bone are removed or scored while an L-shaped strut is preserved for support. In severe C- or S-shaped deformity the whole cartilage is taken out, straightened on the table (sometimes on an absorbable plate) and replaced — extracorporeal septoplasty.
Re-supporting the nose on the straight beam: Spreader grafts hold the middle vault and valve open on either side of the new septum; a strut or extension graft re-anchors the tip to it. The cartilage removed from the deviation is usually the graft material.
Reshaping the outside: Osteotomies bring the bones to the midline; hump reduction and tip refinement are added where they are part of the plan. Sequence matters — septum first, support second, cosmetic last.
Is open septorhinoplasty always better than closed?
No. Neither approach is universally superior — though septorhinoplasty leans open more often than most rhinoplasty, because it usually involves grafting and precise realignment.
- Anatomy matters most. Extracorporeal septal reconstruction, caudal repositioning and spreader grafting are best done under direct vision; a straightforward septoplasty with limited bony straightening can be closed.
- Surgeon experience matters. A technique performed well within a surgeon’s established expertise generally serves a patient better than an unfamiliar one chosen for its label.
- Revision and trauma favour open. Scar and missing cartilage are easier to assess and rebuild openly.
- Scar is minor either way. The open columellar scar is a few millimetres and usually fades to near-invisible; it should not be the deciding factor.
The right question at consultation is not “do you do closed?” but “which approach does my septum and my nose need, and why?”
Links: Open technique | Closed technique | Functional rhinoplasty (valve / turbinate detail)
Sources: NCBI – Rhinoplasty (StatPearls) · Mayo Clinic – Septoplasty
“In septorhinoplasty, the technique is not chosen because it sounds advanced; it is chosen because the nose demands it. A crooked nose, weak tip, valve narrowing, or severe septal deviation may each need a different structural solution. My planning starts by deciding what must be corrected, what must be supported, and what must be preserved. In many cases, the success of septorhinoplasty depends less on one single technique and more on using the right combination of techniques without weakening the nose or compromising breathing.”
What Are the Types of Septorhinoplasty?
Where technique describes how the septum and nose are handled, type describes the scope — how much of the operation is functional, how much cosmetic, and whether the case is primary, post-traumatic or revision.
- Functional septorhinoplasty — septum straightened and the airway supported, with external work limited to what breathing requires (usually straightening). The appearance is preserved or quietly improved. Closest to insurable.
- Septorhinoplasty for crooked nose — septum and the bent outer nose straightened together; the commonest combination.
- Septorhinoplasty with cosmetic reshaping — septum corrected and a hump, tip or width concern addressed in the same operation. Functional and cosmetic parts planned, consented and priced separately. The most comprehensive standard option.
- Caudal septal reconstruction — for a front-of-septum deviation pushing the tip sideways and blocking one nostril. Repositioning or extension graft.
- Extracorporeal septorhinoplasty — for severe C / S-shaped septa bent in more than one plane. The septum is rebuilt outside the nose and replaced straight; osteotomies and grafts complete the correction.
- Post-traumatic septorhinoplasty — for a nose blocked and bent by a fracture. Bones and septum realigned, support rebuilt. If the injury is under 2–3 weeks old, closed reduction may avoid a later operation.
- Revision septorhinoplasty — for a nose still blocked or still crooked after previous septoplasty or rhinoplasty. Missing cartilage rebuilt from ear or rib; technically the most demanding.
Combined planning: turbinate reduction, alar base work or chin balance are added only when each solves a separate concern; more procedures do not automatically mean a better result, and each addition extends operating time and recovery.
Non-surgical options: there is no non-surgical treatment for a deviated septum. Steroid sprays and antihistamines treat allergic swelling; nasal dilator strips can preview valve support. Filler on the concave side of a bent nose can visually soften the curve for 12–18 months but does nothing for breathing. See non-surgical rhinoplasty.
How is septorhinoplasty different from septoplasty, rhinoplasty and functional rhinoplasty?
| Procedure | Main goal | What it works on | Owned by |
|---|---|---|---|
| Septoplasty | Improve breathing | Internal septum only | ENT / summary here |
| Cosmetic rhinoplasty | Improve appearance | External shape — bridge, tip, width | Rhinoplasty hub |
| Septorhinoplasty | Breathing + appearance | Septum AND external nose together | This page |
| Functional rhinoplasty | Improve breathing | Valves, turbinates, post-surgical airway | Functional page |
| Crooked nose correction | Straighten the nose | Bones, cartilage, septum as needed | Crooked nose page |
How Is Septorhinoplasty Performed Step-by-Step?
Septorhinoplasty is performed in a fixed order — septum first, support second, cosmetic reshaping last — so the outer nose is always rebuilt on a straight, stable beam. Incisions sit inside the nostrils (closed) or inside the nostrils plus a small cut across the columella (open).
| Step | What happens |
|---|---|
| 1. Consultation and planning | Breathing history, endoscopy, Cottle test, NOSE score; septum, valves, turbinates, bones, tip and skin assessed; functional and cosmetic plans written separately; insurance documentation started |
| 2. Preoperative preparation | Medical assessment, investigations, anaesthetic review, medication and supplement adjustment, allergy controlled, decongestant sprays weaned, confirmed nicotine cessation, photographs from standard views |
| 3. Surgical markings | Facial midline, nasal axis, planned osteotomy lines, hump / tip targets and existing asymmetry marked with the patient upright |
| 4. Anaesthesia | General anaesthesia with the airway protected; local anaesthetic with adrenaline to limit bleeding. Monitoring is continuous |
| 5. Incision and exposure | Closed or open approach; mucosal flaps raised off the septum on both sides; external framework exposed as needed |
| 6. Septal correction | Deviated cartilage and bone removed or scored with the L-strut preserved; caudal septum repositioned; severe deformity reconstructed extracorporeally. Removed cartilage kept for grafts |
| 7. Airway support | Spreader grafts placed either side of the straightened septum; turbinate conservatively reduced if enlarged |
| 8. Osteotomies | Nasal bones cut and moved to the midline (and narrowed if part of the plan) |
| 9. Tip support | Columellar strut or septal extension graft anchors the tip to the straight septum; tip refined if cosmetic plan includes it |
| 10. Cosmetic reshaping | Hump reduced, dorsal lines refined, alar base adjusted — only as consented |
| 11. Airway and shape check | Both passages checked for patency; external alignment confirmed from the head end against the plan |
| 12. Closure, splints and observation | Mucosa quilted and incisions closed with fine sutures; internal silicone splints and external splint applied; monitored recovery, usually overnight |
Surgical elements and devices
| Element / device | Possible role | Important consideration |
|---|---|---|
| Nasal endoscope | Diagnosis and intra-operative septal / airway check | Standard for functional documentation |
| Septal cartilage (from the deviation) | Spreader, strut and extension grafts | The main advantage of combining the operations |
| Ear (conchal) or rib (costal) cartilage | Grafts when septal cartilage is insufficient | Revision and severe trauma; rib carries warping risk |
| PDS plate (absorbable) | Scaffold for extracorporeal septal reconstruction | Absorbs over months; selected cases |
| Osteotomes (conventional / piezoelectric) | Controlled bone cuts | Bruising expected |
| Quilting / mattress sutures | Close septal dead space, prevent haematoma | Reduces need for packing |
| Internal silicone splints | Support septum, prevent adhesions | Removed at first follow-up |
| External splint and tapes | Hold realigned bones | Must not be removed or wet by the patient |
| Nasal packing (where used) | Bleeding control in the first hours | Increasingly avoided |
Sources: NCBI – Rhinoplasty (StatPearls) · Mayo Clinic – Septoplasty
When Will I See Final Septorhinoplasty Results?
Septorhinoplasty has two result timelines. Breathing: blocked for the first week, opens when splints come out, then improves over 1–3 months as internal swelling settles — judged by airflow and NOSE score. Shape: the straighter bridge is visible at splint removal, refines over 3–6 months, and is final at 6–12 months, later in thick skin. Do not judge either too early — healing is staged.
| Time | Breathing recovery | Cosmetic recovery |
|---|---|---|
| First 48 hours | Congestion, internal swelling, splints present | Swelling and bruising begin |
| Week 1 | Splint removal often around the first week — airway opens | Nose looks swollen; alignment visible |
| Week 2 | Airflow may fluctuate with crusting | Bruising improves |
| Weeks 3–4 | Internal swelling gradually reduces | Social recovery improves |
| Months 1–3 | Breathing may improve noticeably; NOSE score re-measured | Shape still refining |
| Months 3–6 | Airway more stable in many cases | Swelling continues to reduce |
| Months 6–12 | Functional result clearer | Cosmetic result settles |
| 12+ months | Complex cases may continue refining | Thick skin / revision may take longer |
What can affect the final result?
Severity and type of septal deviation; how much cartilage could be preserved for support; whether valve and turbinate issues were treated; graft strength and take; old fracture lines and scar; skin thickness; facial asymmetry; untreated allergy or spray use after surgery; smoking and nicotine exposure; individual healing; whether glasses, pressure or knocks disturbed the bones early; and adherence to irrigation, taping and follow-up.
Results vary by individual anatomy and healing.
What Is the Aftercare After Septorhinoplasty?
Aftercare after septorhinoplasty combines airway care and bone care: saline irrigation to keep the straightened passages clear, no nose-blowing, splint protection, no pressure or knocks on the realigned bones, head elevation, allergy control and no nicotine. These are general principles — your written personal instructions always take priority.
What care is usually advised?
- Keep your head elevated on two pillows for the first week or as instructed.
- Protect the splint and tapes — keep them dry; do not press, adjust or remove them.
- Do not blow your nose for the period advised; sneeze with the mouth open. Internal splints are protecting the straightened septum.
- Saline spray or irrigation several times a day once cleared — clears crust and keeps the airway open.
- Apply ointment inside the nostrils as shown.
- Continue allergy treatment exactly as prescribed; stay off decongestant sprays unless specifically prescribed.
- Take medicines exactly as prescribed and do not restart blood-thinning medicines or supplements without approval.
- Walk gently — short walks support circulation; bending, straining and exercise wait until cleared.
- Attend all follow-up appointments — splint removal, checking the septum and bones remain midline, crust clearance, and NOSE-score review at 3 months.
What should patients avoid after septorhinoplasty?
| Avoid | Why |
|---|---|
| Smoking, vaping, nicotine in any form | Reduces blood supply to mucosa, skin and grafts; increases septal perforation and healing risk |
| Glasses resting on the bridge (usually 4–6 weeks) | Pressure can shift freshly repositioned bones; tape glasses to the forehead or use contact lenses |
| Contact sports, crowded transport, playing with small children near the face | A knock can displace the bones or septum before they set |
| Nose blowing, sniffing hard, picking crusts | Can cause bleeding, septal haematoma and disturb the straightened septum |
| Decongestant sprays | Rebound swelling; dependence returns |
| Strenuous exercise and heavy lifting (2–4 weeks) | Raises blood pressure and swelling; increases bleeding risk |
| Swimming, steam, sauna (4 weeks) | Wets the splint; heat increases swelling; infection risk to healing mucosa |
| Direct sun on the nose | Worsens swelling and can darken the columellar scar |
| Sleeping on your side or face | Pressure on one side can push the bones asymmetric |
| Judging breathing or shape in the first weeks | Swelling and crust make early results unrepresentative |
Full aftercare detail: Rhinoplasty recovery timeline
What Are the Risks and Complications of Septorhinoplasty?
Septorhinoplasty is generally safe for an appropriately selected patient operated on by a trained plastic surgeon in an equipped facility, but it is bone, septum and airway surgery with recognised risks. It is performed to improve structure and function, but no surgery can remove all risk or fully control healing response. Expected postoperative effects must be separated from true complications.
Common / expected early effects (normal healing, not complications): a fully blocked nose for the first week; swelling of the nose and cheeks, often uneven; bruising under the eyes from the osteotomies; crusting and slight bloody discharge; numbness of the tip; mild aching; temporary asymmetry during the swelling phase.
Uncommon complications: bleeding, early or after strain; infection; septal haematoma (blood collecting inside the septum — needs urgent drainage); synechiae (internal adhesions); persistent obstruction; residual or recurrent external deviation; valve weakness; asymmetry; contour irregularity or a palpable step at an osteotomy; graft shift, warping or resorption; prolonged numbness; dissatisfaction leading to a revision request.
Rare but important: septal perforation (a hole in the septum, which may whistle, crust or bleed); saddle deformity if support is over-resected; loss of tip support; skin compromise, most strongly associated with nicotine; anaesthesia-related complications; very rarely, eye or vision symptoms after nasal surgery, which are an emergency.
How risk is minimised
| Risk area | How we work to minimise it |
|---|---|
| Septal haematoma | Quilting sutures close the septal space; internal splints; early follow-up; patients taught the warning signs |
| Septal perforation / saddle | L-strut of at least 1–1.5 cm preserved; mucosa handled carefully; conservative resection |
| Persistent blockage | Valve and turbinates assessed and treated with the septum — not septum alone |
| Still-crooked nose | Septum straightened structurally, not camouflaged; asymmetric osteotomies and grafts planned against the facial midline |
| Valve collapse after straightening | Spreader grafts placed before closure where the middle vault is weak |
| Undetected medical or airway risk | Preoperative medical evaluation, endoscopy and anaesthetic review before scheduling |
| Nicotine-related healing failure | A clear, enforced nicotine cessation requirement before and after surgery |
| Bleeding | Medication and supplement review, blood-pressure control, meticulous haemostasis, selective packing |
| Infection | Sterile technique, theatre sterilisation protocols, perioperative antibiotics, irrigation instruction |
| Facility and equipment risk | Surgery at an NABH-accredited surgical centre with appropriate equipment |
| Delayed recognition of a problem | Structured postoperative observation, written warning signs, accessible follow-up |
⚠️ When to seek urgent medical attention
Seek urgent advice or immediate emergency care for: heavy or persistent bleeding · fever with worsening pain or redness · sudden worsening blockage (haematoma or swelling concern) · marked septal tenderness · severe facial pain · new foul discharge · rapidly increasing swelling · any vision change or eye pain · chest pain or breathlessness.
In an emergency, go to the nearest emergency department or call emergency services. Do not wait for a WhatsApp or email reply.
Full risk guide: Rhinoplasty Risks & Safety
Sources: NCBI – Rhinoplasty (StatPearls) · AAO-HNS – Rhinoplasty FAQ
What Is the Septorhinoplasty Recovery Timeline?
Recovery after septorhinoplasty is gradual and runs on two clocks. Bruising from the osteotomies clears over 2 weeks; internal and external splints come off at about a week, and breathing opens the same day; most patients return to desk work within 7–10 days. Airway improvement is judged at 1–3 months; shape at 6–12 months. This is a summary — for detailed day-by-day guidance on sleeping position, nasal care, glasses, exercise, travel and sun protection, see the rhinoplasty recovery timeline.
| Timepoint | What typically happens |
|---|---|
| First 24–48 hours | Internal septal splints and external splint in place. Nose fully blocked; mouth-breathing, swelling, bruising under the eyes, slight bloody discharge and mild-to-moderate aching expected. Rest head-elevated; overnight observation usual |
| Days 3–7 | Bruising peaks then fades; swelling begins reducing. Crusting starts. Splints and sutures removed at the first follow-up around day 7 — breathing usually opens noticeably the same day |
| Weeks 2–3 | Most bruising gone; saline irrigation clears crust; both sides begin to feel open. Many patients return to desk work. Nose still swollen and may look slightly uneven |
| Weeks 4–6 | Bones knit. Glasses, gentle exercise and travel usually cleared at review. Dorsal line straightens visibly |
| 3 months | Internal swelling settled; NOSE score re-measured. Airway result essentially final. Upper nose near final |
| 6–12 months | Cosmetic result settles; tip and thick-skin areas final. Scars mature |
| 12+ months | Complex, post-traumatic and revision cases may continue refining. Any revision assessment waits until here |
Key recovery points: expect to breathe WORSE for the first week — this is splints and swelling, not failure · splint removal is the turning point for breathing · bruising is greatest at day 2–3 and settles over 2 weeks · glasses stay off the bridge for 4–6 weeks · saline irrigation is the job for the first month · flying requires written clearance at follow-up — do not book non-refundable travel around an assumed date · outstation patients usually stay in Mumbai until splints are removed.
Do not use another patient’s timeline as permission for glasses, exercise, travel or restarting medication.
Related links: Rhinoplasty Recovery Timeline | Outstation Patients
Medical Codes for Septorhinoplasty
Codes below are for administrative and documentation reference — and for insurance pre-authorisation of the functional component. All codes must be verified against the current CPT and ICD-10 code sets before publication and before any use in documentation.
| CPT Code | CPT Description | ICD-10 |
|---|---|---|
| 30420 | Rhinoplasty, primary; including major septal repair — the core septorhinoplasty code | J34.2 (deviated nasal septum) · M95.0 (acquired deformity of nose) |
| 30520 | Septoplasty or submucous resection, with or without cartilage scoring, contouring or replacement with graft (functional component) | J34.2 |
| 30465 | Repair of nasal vestibular stenosis (spreader grafting, lateral wall reconstruction) — valve repair | J34.89 |
| 30140 | Submucous resection inferior turbinate, partial or complete (when turbinate reduced) | J34.3 |
| 30410 | Rhinoplasty, primary; complete, external parts including bony pyramid, lateral and alar cartilages, and/or elevation of nasal tip (cosmetic component) | Z41.1 (cosmetic) |
| 30435 / 30450 | Rhinoplasty, secondary; intermediate / major revision (revision septorhinoplasty) | J34.2 · Z98.890 |
| 21325 / 21335 | Open treatment of nasal fracture; complicated / with concomitant septal fracture (recent trauma) | S02.2XXA |
| 21235 / 20912 | Ear cartilage graft / nasal septal cartilage graft harvest | — |
(FAQs) Frequently Asked Questions About Septorhinoplasty
Q1. Can septorhinoplasty fail or need revision?
Ans. Yes. Breathing can remain limited if a valve or turbinate problem was missed, adhesions form or the septum re-deviates; the nose can remain or become crooked from cartilage memory or old fracture lines. Revision is assessed only after complete healing — 6 months for the airway, 12 months for shape — and is technically more demanding because scar and missing cartilage constrain the plan.
Q2. Is septorhinoplasty safe in India?
Ans. It is generally safe for an appropriately selected patient when performed by a qualified plastic surgeon in an accredited facility with proper anaesthetic support. Recognised risks remain — septal haematoma, perforation, persistent blockage, residual deviation. Judge the surgeon’s qualification, rhinoplasty volume and the facility’s accreditation, not the country.
Q3. How long does septorhinoplasty surgery take?
Ans. Usually 2–3.5 hours. Extracorporeal septal reconstruction, rib cartilage harvest, extensive cosmetic reshaping or revision may take longer. The planned duration is confirmed only after examination and surgical planning.
Q4. What if breathing is still blocked after surgery?
Ans. Persistent or worsening obstruction should be reviewed by the surgeon. Causes may include swelling, crusting, residual deviation, valve collapse, adhesions, infection or haematoma. Sudden worsening blockage or severe pain needs urgent assessment — a septal haematoma must be excluded.
Q5. Can a straight septum make the nose look straight?
Ans. Not always. A straight septum can improve internal alignment, but the external nose may still look crooked if nasal bones, upper cartilages, tip support or soft-tissue forces are also involved. Septorhinoplasty addresses both when needed — that is the reason for combining them.
Q6. Will there be scars after septorhinoplasty?
Ans. Closed septorhinoplasty uses internal incisions with no external scar. Open septorhinoplasty uses a small columellar incision that usually fades to near-invisible. Technique choice depends on deformity complexity, exposure needs and surgeon planning.
Q7. Is septorhinoplasty a major surgery?
Ans. It can be considered a significant operation because it works on both the airway framework and external nasal shape under general anaesthesia, usually with an overnight stay. Complexity depends on deviation severity, grafting, valve support, cosmetic goals and whether the case is primary or revision.
Q8. Can septorhinoplasty and cosmetic rhinoplasty be done together?
Ans. Yes — septorhinoplasty is specifically planned when functional septal correction and cosmetic reshaping are both needed. Combining them avoids separate surgeries and lets the removed septal cartilage serve as graft material. The cosmetic portion is consented and priced separately and is usually not covered by insurance.
Q9. Does thick skin affect the result?
Ans. Yes. Thick skin does not affect the breathing result, but it slows and softens the visible cosmetic result — swelling lasts longer and fine definition is limited. The straightening itself is unaffected; expectations for the cosmetic timeline are set accordingly.
Q10. When can I fly after septorhinoplasty?
Ans. Only after written clearance at a follow-up review, usually once internal and external splints are off and there is no bleeding concern. Dry cabin air worsens crusting, so travel with saline spray. Outstation patients typically stay in Mumbai for about a week. Do not book non-refundable travel around an assumed date.
Q11. How do I get insurance pre-authorisation for the breathing part?
Ans. Your insurer will typically want the ICD-10 diagnosis (J34.2 deviated septum), endoscopy findings, a NOSE score, evidence that medical treatment (sprays, antihistamines) has failed, and a surgeon’s letter separating the functional from the cosmetic component with its own estimate. Our team prepares this file after consultation; approval is the insurer’s decision and must be in writing before surgery.
Related Links
- Rhinoplasty Surgery
- Rhinoplasty Cost
- Rhinoplasty Before & After Gallery
- Nasal Hump / Dorsum Deformities
- Augmentation Rhinoplasty
- Nasal Tip Plasty
- Broad Nose Correction
- Bulbous & Boxy Tip Correction
- Drooping Tip Correction
- Reduction Rhinoplasty
- Ethnic Rhinoplasty
- Revision Rhinoplasty
- Open Rhinoplasty Technique
- Closed Rhinoplasty Technique
- Non-Surgical Rhinoplasty
- Chin Augmentation Surgery
- Rhinoplasty Recovery Timeline
- How to Prepare for Rhinoplasty
- Rhinoplasty Risks & Safety

